Myxedema coma
- Synonyms
- myxoedema coma, hypothyroid coma, myxedema crisis
- Specialty
- Internal medicine · Endocrinology & diabetes
- Images
- CT 1 · ECG 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
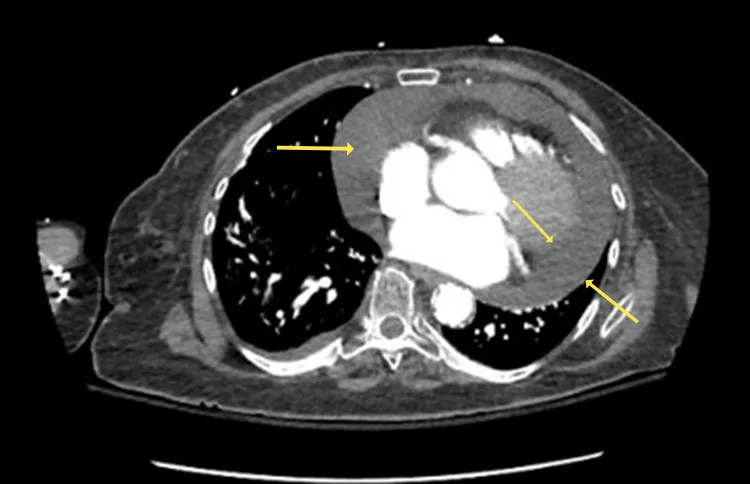 CT
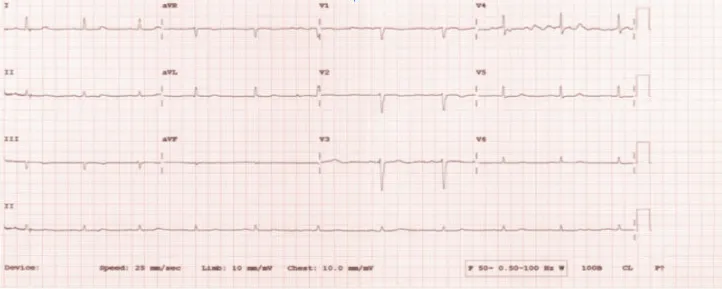 ECG
Definition
Myxedema coma is the life-threatening decompensation of severe, usually long-standing hypothyroidism. It is characterized by impaired consciousness up to coma, marked hypothermia and respiratory depression.
Aetiopathogenesis
Those affected usually have long-standing, often unrecognized or inadequately replaced hypothyroidism. Typical precipitating factors are:
- acute illness, particularly infection
- trauma
- drugs or substances that depress the central nervous system
- exposure to cold
Pathophysiology: hormone deficiency lowers the basal metabolic rate and heat production. Respiratory drive and respiratory muscles are weakened, leading to carbon dioxide retention and hypoxemia. Free water excretion is reduced, which favors hyponatremia. Drugs are metabolized more slowly. In central hypothyroidism, adrenal insufficiency may also be present.
Clinical features
- Consciousness: somnolence up to coma, seizures
- Hypothermia: body temperature of 24 to 32.2 °C; it is easily missed unless a low-reading thermometer is used
- Breathing: respiratory depression with carbon dioxide retention
- Neurology: areflexia
- Cardiovascular: bradycardia, pericardial effusion; pleural effusions
- Signs of hypothyroidism: puffy face with periorbital swelling, doughy, dry skin, macroglossia, coarse hair
- With a central cause: hypoglycemia and hypotension due to accompanying adrenal or growth hormone insufficiency
Diagnosis
The diagnosis is made rapidly on the basis of history and clinical findings; laboratory tests confirm it.
- Thyroid function: low fT4; TSH markedly raised in primary hypothyroidism, low or normal with a central cause
- Blood gas analysis: hypercapnia and hypoxemia
- Laboratory tests: sodium (hyponatremia), glucose (hypoglycemia), CK, cholesterol, blood count; cortisol to detect accompanying adrenal insufficiency
- Core body temperature with a suitable thermometer
- ECG and echocardiography: bradycardia, pericardial effusion
- Search for the trigger: e.g. infection work-up, drug history
Treatment principles
- Treatment takes place in intensive care with intravenous thyroid hormone replacement.
- Glucocorticoids are given at the same time until adrenal insufficiency has been excluded.
- Supportive priorities are ventilation for hypoventilation, slow passive rewarming, correction of hyponatraemia and hypoglycaemia, and treatment of the precipitant, often an infection.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Endocrinology & diabetes
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Type 2 diabetes mellitus · Primary aldosteronism (Conn's syndrome) · Hyperthyroidism
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.