IgA nephropathy
Board exam relevance: in 1 of more than 100 exam reports · rank 181- Synonyms
- Berger disease, IgA glomerulonephritis, IgAN, synpharyngitic hematuria
- Specialty
- Internal medicine · Nephrology
- Images
- Histology 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
IgA nephropathy (Berger disease) is a chronic glomerulonephritis with deposition of IgA-containing immune complexes in the glomerular mesangium. It presents with slowly progressive hematuria and proteinuria and may lead to chronic kidney disease.
Occurrence & epidemiology
IgA nephropathy is the most common form of glomerulonephritis worldwide. It is more common in Asia and some European countries than in Africa and South America. Onset peaks in the third and fourth decades of life (ages 20 to 39); men are generally affected more often than women.
Aetiopathogenesis
The cause is not fully understood. Proposed mechanisms include increased production of IgA1, defective IgA1 glycosylation with increased binding to mesangial cells, reduced clearance of IgA1, a disturbed mucosal immune system and cytokine-mediated proliferation of mesangial cells. Familial clustering suggests genetic factors. Renal IgA deposits are also found in many healthy people; not everyone with such deposits develops clinical disease.
Mesangial IgA deposits also occur secondarily, e.g. in IgA vasculitis, liver cirrhosis, inflammatory bowel disease, celiac disease, psoriasis and HIV infection. IgA vasculitis differs clinically by purpura, joint pain and abdominal pain.
Clinical features
- Episodic gross hematuria, typically 1–2 days after a febrile mucosal infection (respiratory tract, sinuses, gut): "synpharyngitic" hematuria, often with flank pain and low-grade fever. The latency is shorter than in postinfectious glomerulonephritis.
- Asymptomatic microscopic hematuria with mild proteinuria as an incidental finding
- Less common presentations: nephrotic syndrome (about 10%), rapidly progressive glomerulonephritis as initial presentation (about 5%), acute kidney injury, severe hypertension or chronic kidney disease
Histology
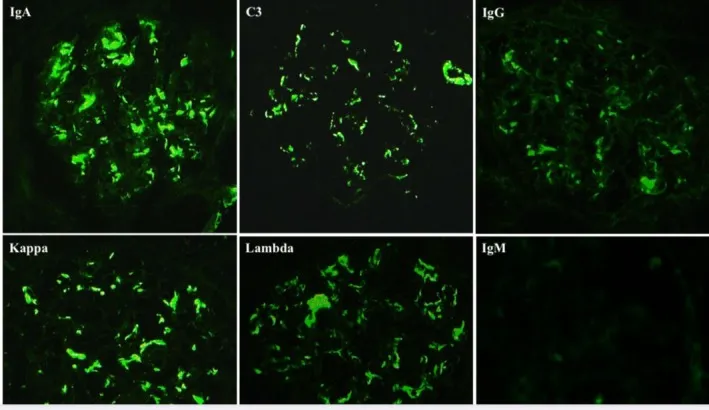
Immunofluorescence shows granular deposits of IgA and complement C3 in an expanded mesangium. Light microscopy shows mesangial expansion and focal segmental proliferative or necrotizing lesions.
Diagnosis
- Urine sediment: microscopic hematuria, usually with dysmorphic red cells, occasionally red blood cell casts
- Proteinuria: typically mild (< 1 g/day); it may also occur without hematuria.
- Blood: creatinine usually normal, complement normal; an elevated serum IgA is not diagnostically helpful.
- Kidney biopsy: confirms the diagnosis when manifestations are moderate or severe
Treatment principles
- The basis is optimised supportive therapy with RAAS inhibition, blood pressure control, SGLT2 inhibitors and lifestyle measures to reduce proteinuria.
- With persistent proteinuria and risk of progression, endothelin receptor antagonists, targeted glucocorticoid therapy or newer targeted therapies may be added.
- Rapidly progressive disease is treated with immunosuppression, as in other rapidly progressive glomerulonephritides.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Nephrology
- Acute kidney injury
- Nephrotic syndrome
- Chronic kidney disease
- Nephritic syndrome and glomerulonephritis
- Lupus nephritis
- Membranous nephropathy
- Minimal change disease
- Kidney stones (nephrolithiasis)
- Renal artery stenosis
- Rapidly progressive glomerulonephritis (RPGN)
- Renal tubular acidosis
- Acute interstitial nephritis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute kidney injury · Nephrotic syndrome · Chronic kidney disease
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.