Acute interstitial nephritis
Board exam relevance: in 3 of more than 100 exam reports · rank 111- Synonyms
- acute tubulointerstitial nephritis, AIN, ATIN, interstitial nephritis, drug-induced interstitial nephritis
- Specialty
- Internal medicine · Nephrology
- Images
- Histology 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
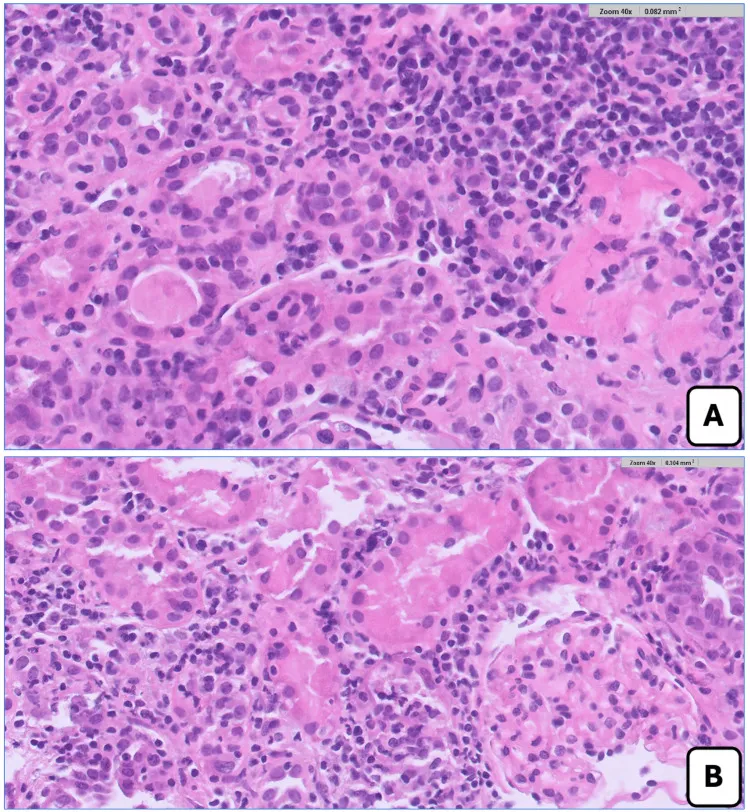 Histology
Definition
Acute interstitial nephritis (acute tubulointerstitial nephritis) is inflammation of the renal interstitium with an inflammatory infiltrate and edema that develops over days to months and also damages the tubules. It causes acute kidney injury; severe or late-recognized cases may progress to chronic kidney disease.
Aetiopathogenesis
More than 95% of cases result from an allergic drug reaction or from infections; more than 120 drugs have been described as triggers.
- Allergic reaction to drugs: most commonly beta-lactams, also other anti-infectives, NSAIDs, acid-suppressing drugs, antiseizure drugs, drugs that increase urine output and others
- Infections: bacteria (e.g. streptococci, staphylococci, Legionella, Leptospira, Mycoplasma, mycobacteria), viruses (cytomegalovirus, Epstein-Barr virus, hantavirus, HIV, polyomavirus), Toxoplasma and fungi
- Immunologic: sarcoidosis, Sjögren syndrome, systemic lupus erythematosus, IgG4-related disease, anti-TBM antibodies, tubulointerstitial nephritis with uveitis (TINU syndrome)
- Other: hyperuricosuria, tumor lysis syndrome, ethylene glycol, infiltration in lymphoma or myeloma
Clinical features
Symptoms are often nonspecific or absent until signs of kidney injury develop. Many patients have polyuria and nocturia due to the concentrating defect. With a drug cause, symptoms begin several weeks after first exposure or as early as 3–5 days after re-exposure; latency ranges from one day to 18 months.
Fever and an urticarial or maculopapular rash are typical early signs of the drug-induced form; however, the classic triad of fever, rash and eosinophilia is present in fewer than 10%. Abdominal or flank pain, weight loss and bilaterally enlarged kidneys (interstitial edema) may occur. Edema and hypertension are uncommon unless renal failure is advanced.
Histology
The glomeruli are usually normal. Early on there is interstitial edema, followed by an infiltrate of lymphocytes, plasma cells, eosinophils and a few neutrophils. In severe cases, inflammatory cells invade the tubular epithelium (tubulitis). Granulomas occur with certain drugs, mycobacteria and fungi; noncaseating granulomas suggest sarcoidosis, and a lymphoplasmacytic infiltrate with storiform fibrosis suggests IgG4-related nephritis.
Diagnosis
- History: temporal relationship with a newly taken drug, infections, systemic diseases
- Urine: active sediment with white cells, white cell casts and red cells with a negative culture (sterile pyuria); marked hematuria and dysmorphic red cells are uncommon. Proteinuria is usually mild (< 1 g/day), but may be nephrotic in NSAID-related forms with glomerular involvement. Urinary eosinophils neither confirm nor exclude the diagnosis.
- Blood: rising creatinine; signs of tubular dysfunction such as hypokalemia and normal anion gap metabolic acidosis; elevated IgG or IgG4 and low complement in IgG4-related or hypocomplementemic interstitial nephritis
- Imaging: ultrasound with enlarged, echogenic kidneys; scintigraphy with gallium-67 or labeled white cells may show uptake, but a negative result does not exclude the disease.
- Kidney biopsy: establishes the diagnosis, especially when the picture is unclear or kidney injury progresses
Treatment principles
- The key measure is immediate withdrawal of the causative drug, such as proton pump inhibitors, non-steroidal anti-inflammatory drugs or certain antibiotics, or treatment of an underlying infection or systemic disease.
- If kidney function does not improve promptly, early glucocorticoid therapy is considered.
- Supportive care includes fluid and electrolyte balance and, in severe kidney failure, temporary dialysis; the causative agent is recorded in an allergy passport.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Nephrology
- Acute kidney injury
- Nephrotic syndrome
- Chronic kidney disease
- Nephritic syndrome and glomerulonephritis
- Acute pyelonephritis
- Autosomal dominant polycystic kidney disease (ADPKD)
- Bartter and Gitelman syndromes
- Diabetic kidney disease
- Focal segmental glomerulosclerosis (FSGS)
- Goodpasture syndrome (anti-GBM disease)
- Hantavirus infection (nephropathia epidemica)
- Urinary tract infection and cystitis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute kidney injury · Nephrotic syndrome · Chronic kidney disease
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.