Diabetic ketoacidosis
Board exam relevance: in 4 of more than 100 exam reports · rank 90- Synonyms
- DKA, ketoacidosis, diabetic coma, ketoacidotic coma, high blood sugar emergency
- Specialty
- Internal medicine · Endocrinology & diabetes
- Images
- CT 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
 CT
Definition
Diabetic ketoacidosis (DKA) is an acute, life-threatening metabolic decompensation caused by insulin deficiency. It is characterized by the triad of hyperglycemia, hyperketonemia and metabolic acidosis with an increased anion gap. Osmotic diuresis leads to substantial losses of water and electrolytes.
In euglycemic DKA, ketoacidosis occurs without markedly elevated glucose, e.g. in pregnancy, in alcohol misuse or liver cirrhosis, and drug-induced.
Occurrence & epidemiology
DKA occurs predominantly in type 1 diabetes and is the first manifestation in about one third of patients. In type 2 diabetes it is less common and develops mainly under unusual physiological stress; a special form is ketosis-prone type 2 diabetes (Flatbush diabetes), which occurs more often in people of African ancestry with obesity.
Aetiopathogenesis
Precipitating factors
Insulin deficiency may be absolute or relative, when requirements rise under physiological stress:
- acute infections (e.g. pneumonia, urinary tract infection, COVID-19)
- myocardial infarction, stroke, pancreatitis, trauma
- pregnancy
- new-onset type 1 diabetes
- drug-induced, e.g. glucocorticoid-induced
Pathophysiology
- Hormonal imbalance: insulin deficiency with a simultaneous rise in counter-regulatory hormones (glucagon, catecholamines, cortisol).
- Lipolysis and ketogenesis: unrestrained lipolysis releases glycerol and free fatty acids. Glucagon promotes their conversion to ketone bodies (acetoacetate, beta-hydroxybutyrate) in hepatic mitochondria; these strong organic acids cause the acidosis. Acetone is partly exhaled.
- Gluconeogenesis: glycerol and alanine from muscle breakdown serve as substrate for the liver; hyperglycemia worsens.
- Osmotic diuresis: glucose and ketone bodies in the urine carry water, sodium and potassium with them.
- Potassium: despite a substantial total-body deficit, serum potassium is often normal or raised initially because acidosis shifts potassium out of the cells.
Clinical features
Leading symptoms are:
- polyuria, polydipsia, weakness
- nausea, vomiting, and abdominal pain, particularly in children (pseudoperitonitis)
- deep, rapid breathing (Kussmaul respiration) as respiratory compensation, fruity acetone odour of the breath
- dehydration, tachycardia, hypotension
- lethargy and somnolence progressing to coma
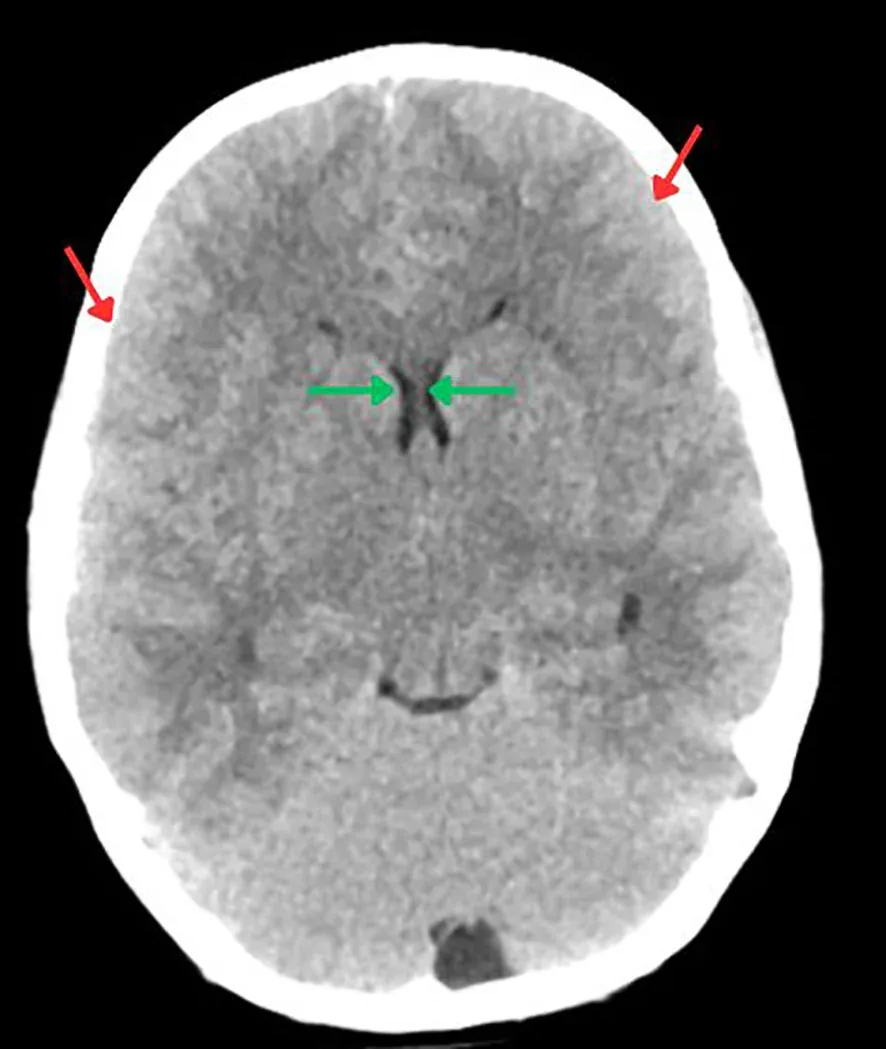
Fever is not a feature of DKA itself and points to a precipitating infection. Cerebral edema occurs in less than 1 %, mainly in children; warning signs are headache and a fluctuating level of consciousness, and sometimes respiratory arrest is the first sign.
Diagnosis
Diagnostic criteria
- arterial or venous pH < 7.30
- anion gap > 10–12 mmol/l
- serum bicarbonate < 15–18 mmol/l
- ketone bodies in serum or urine
- glucose > 200–250 mg/dl (11.1–13.8 mmol/l); some guidelines accept known diabetes instead of a cut-off in order to capture euglycemic cases
DKA and HHS compared
- DKA: glucose > 200–250 mg/dl (11.1–13.8 mmol/l) or known diabetes; pH < 7.30, bicarbonate < 15–18 mmol/l, increased anion gap; ketone bodies in serum or urine.
- HHS: glucose ≥ 600 mg/dl (≥ 33.3 mmol/l); calculated effective serum osmolality > 300 mOsm/kg or total serum osmolality > 320 mOsm/kg; no relevant ketosis (urine ketones < 2+ or beta-hydroxybutyrate < 3.0 mmol/l); pH ≥ 7.3 and bicarbonate ≥ 15 mmol/l.
- Consciousness: in HHS, impaired consciousness is the leading symptom; in DKA, lethargy and somnolence occur with severe decompensation.
- Mixed forms: overlap between DKA and HHS has been described in more than one third of hyperglycemic crises.
Further findings
- Ketone bodies: urine test strips and some serum assays detect only acetoacetate, not the usually predominant beta-hydroxybutyrate, and therefore underestimate ketosis; beta-hydroxybutyrate can be measured directly in blood.
- Electrolytes and kidney: sodium (often dilutionally low because of hyperglycemia), potassium, urea, creatinine, osmolality.
- Other laboratory values: amylase and lipase are often raised even without pancreatitis.
- ECG: in adults to look for myocardial infarction and to assess the effects of potassium.
- Search for the trigger: targeted tests according to the clinical picture, e.g. cultures and imaging.
Treatment principles
- Diabetic ketoacidosis is an emergency: fluid replacement with crystalloids and continuous intravenous insulin therapy come first.
- Potassium is closely monitored and replaced before and during insulin administration, buffering of the acidosis is reserved for exceptional situations, and glucose and osmolality should normalise only gradually.
- Precipitating factors such as infection or interruption of insulin are sought and treated; after stabilisation, transition to subcutaneous insulin therapy and education follow.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Endocrinology & diabetes
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Type 2 diabetes mellitus · Primary aldosteronism (Conn's syndrome) · Hyperthyroidism
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.