Aortic regurgitation
Board exam relevance: in 1 of more than 100 exam reports · rank 181- Synonyms
- aortic insufficiency, AR, leaky aortic valve, aortic incompetence
- Specialty
- Internal medicine · Cardiology
- Images
- Echocardiography 2
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
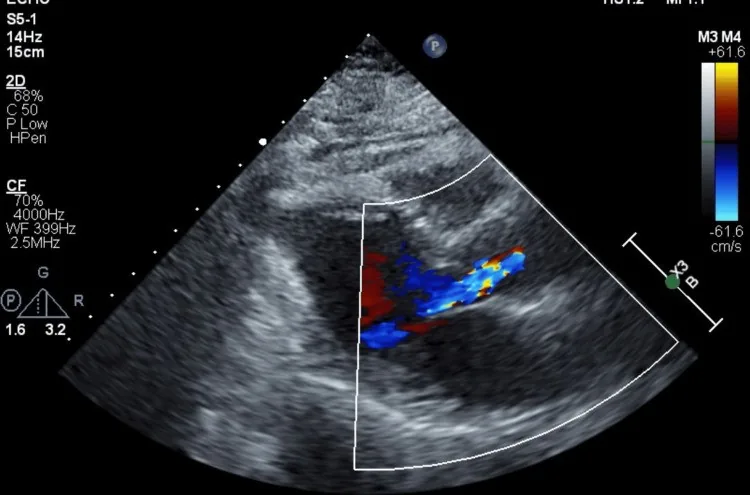 Echocardiography
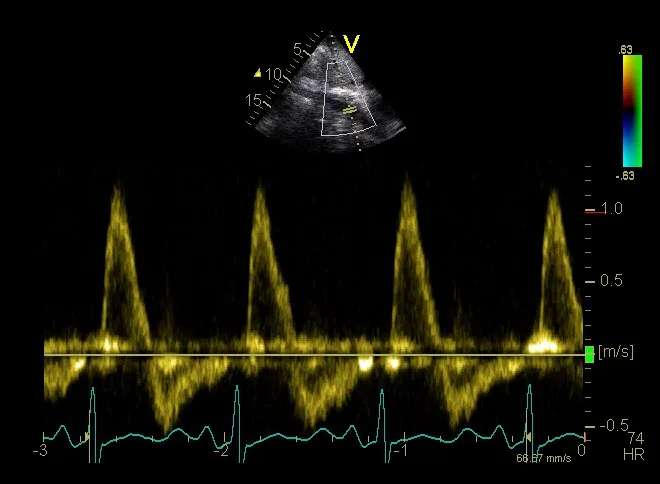 Echocardiography
Definition
Aortic regurgitation (AR), also called aortic insufficiency, is incomplete closure of the aortic valve with diastolic backflow of blood from the aorta into the left ventricle. It is caused by disease of the valve, dilatation of the aortic root, or both.
Classification
- Acute AR (uncommon): the main causes are dissection of the ascending aorta and infective endocarditis.
- Chronic AR: gradual development with adaptation of the ventricle.
- Severe chronic AR (echocardiography), suggested by any of the following: color Doppler jet width at least 65 % of the left ventricular outflow tract, holodiastolic flow reversal in the abdominal aorta, regurgitant volume of at least 60 ml per beat, regurgitant fraction of at least 50 %, vena contracta above 6 mm.
Aetiopathogenesis
- Chronic AR in adults: degeneration of the valve and aortic root (with or without a bicuspid valve), infective endocarditis, myxomatous degeneration (e.g. in Marfan or Ehlers-Danlos syndrome), rheumatic fever, thoracic aortic aneurysm, trauma.
- Rare causes: seronegative spondyloarthropathies (e.g. ankylosing spondylitis, psoriatic arthritis), rheumatoid arthritis, systemic lupus erythematosus, syphilitic aortitis, Takayasu and giant cell arteritis, rupture of a sinus of Valsalva.
- In children: ventricular septal defect with aortic valve prolapse, bicuspid valve.
- Pathophysiology: during diastole the left ventricle additionally receives the regurgitant volume. In chronic AR, hypertrophy and dilatation develop gradually, so pressures and cardiac output stay normal for a long time until decompensation occurs. In acute AR the ventricle cannot dilate; pressure rises rapidly.
Clinical features
- Chronic AR: asymptomatic for years; then insidiously progressive exertional dyspnea, orthopnea, paroxysmal nocturnal dyspnea and palpitations. Chest pain is uncommon without coexisting coronary artery disease and then tends to occur at night.
- Acute AR: signs of heart failure up to cardiogenic shock with tachycardia, cool extremities, lung crackles and low blood pressure.
- Auscultation: high-pitched, blowing diastolic decrescendo murmur beginning soon after the second heart sound, loudest at the 3rd or 4th left parasternal intercostal space or at the apex, best heard with the patient leaning forward with breath held in end-expiration; often soft or absent in acute AR. Austin Flint murmur: mid-to-late diastolic rumble at the apex.
- Apex beat: over time enlarged, increased in amplitude and displaced downwards and laterally.
- Peripheral signs of the wide pulse pressure: water-hammer (collapsing) pulse, visible capillary pulsation of the nail beds (Quincke sign), head bobbing synchronous with the pulse (de Musset sign), pistol-shot sound over the femoral artery (Traube sign), Duroziez sign.
Diagnosis
- Doppler echocardiography: the test for detecting and quantifying regurgitant flow; two-dimensional imaging of aortic root size and anatomy and LV function; two- and three-dimensional assessment of cusp morphology.
- TOE and 3D echocardiography: more detailed delineation of aortic dilatation and valve anatomy.
- ECG-gated CT or MRI: assessment of the entire thoracic aorta when the aorta is enlarged; MRI also to determine LV function and severity when echo images are suboptimal.
- ECG: repolarisation abnormalities with or without voltage criteria of hypertrophy, left atrial enlargement, T-wave inversion with precordial ST depression.
- Chest X-ray: cardiomegaly, prominent aortic root; in severe AR pulmonary edema and signs of heart failure.
- Exercise testing: assessment of functional capacity and symptoms when symptoms are equivocal.
Treatment principles
- Acute severe aortic regurgitation, for example in endocarditis or aortic dissection, requires urgent surgery.
- In chronic severe regurgitation, valve replacement or repair is indicated when symptoms occur or when left ventricular dilatation or dysfunction begins, and an associated dilatation of the aortic root is addressed at the same time.
- Blood pressure control, for example with RAS inhibitors, is useful in hypertension or when surgery is not possible; asymptomatic patients are followed up by echocardiography.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Aortic valve stenosis
- Arrhythmogenic right ventricular cardiomyopathy (ARVC)
- Atrioventricular block
- AV nodal re-entrant tachycardia (AVNRT)
- Brugada syndrome
- Chronic coronary syndrome (stable coronary artery disease)
- Dilated cardiomyopathy
- Dressler syndrome (post-myocardial infarction syndrome)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.