Atrioventricular block
Board exam relevance: in 10 of more than 100 exam reports · rank 27- Synonyms
- heart block, complete heart block, third-degree heart block, Wenckebach block, Mobitz block, Mobitz type I, Mobitz type II, Stokes-Adams attack
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 4
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (4)
 ECG
 ECG
 ECG
 ECG
Definition
Atrioventricular (AV) block is a partial or complete interruption of impulse conduction from the atria to the ventricles. The block may be located in the AV node or below it in the His-Purkinje system (His bundle, bundle branches). First- and second-degree AV blocks are partial; third-degree AV block is complete.
Classification
Degrees of AV block
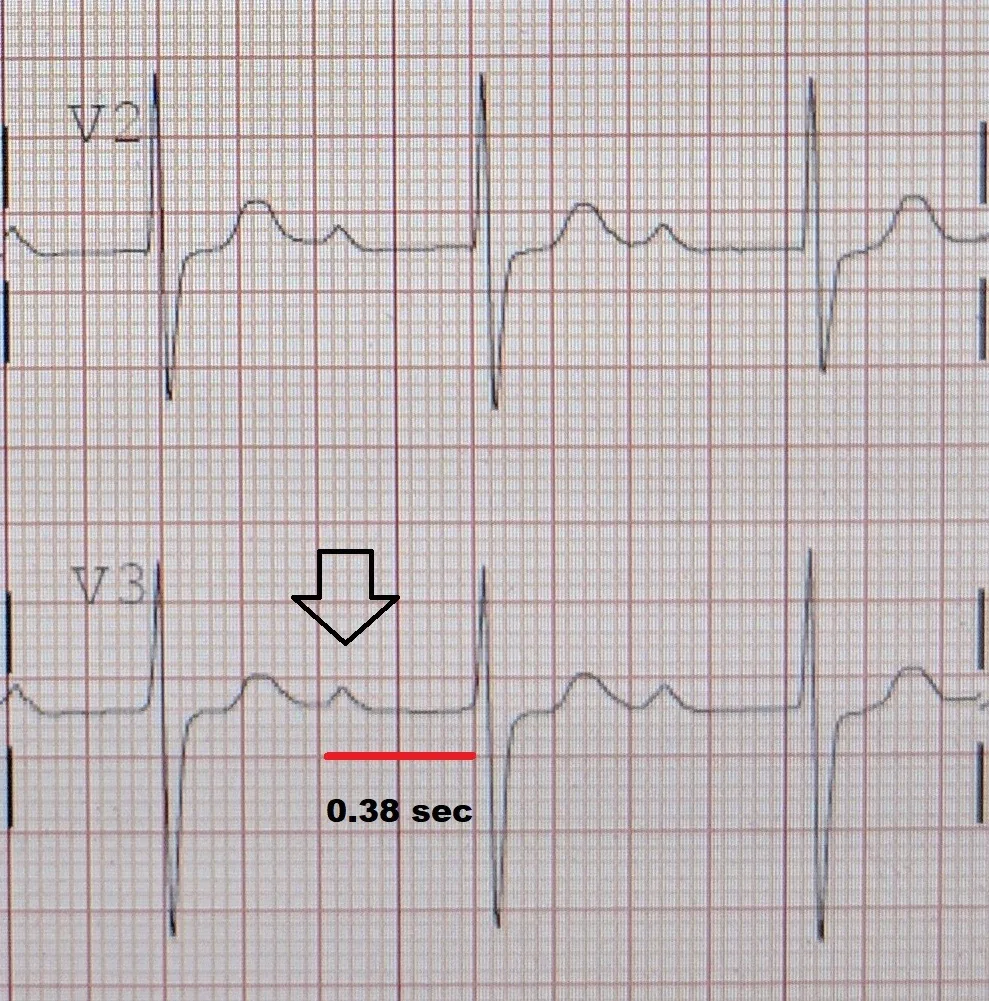
- First-degree AV block: conduction delay without dropped beats; every P wave is conducted, but the PR interval is longer than 0.20 s.
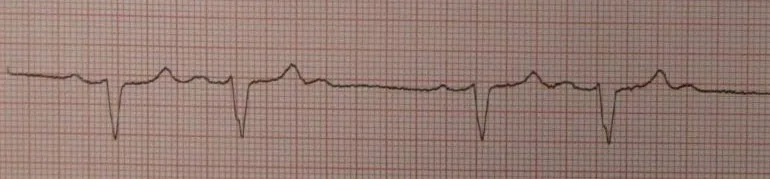
- Second-degree AV block, Mobitz type I (Wenckebach): the PR interval lengthens with each beat until a P wave is not conducted and a QRS complex is dropped; the next conducted beat has the shortest PR interval, and the sequence repeats. With a narrow QRS the block is almost always in the AV node.
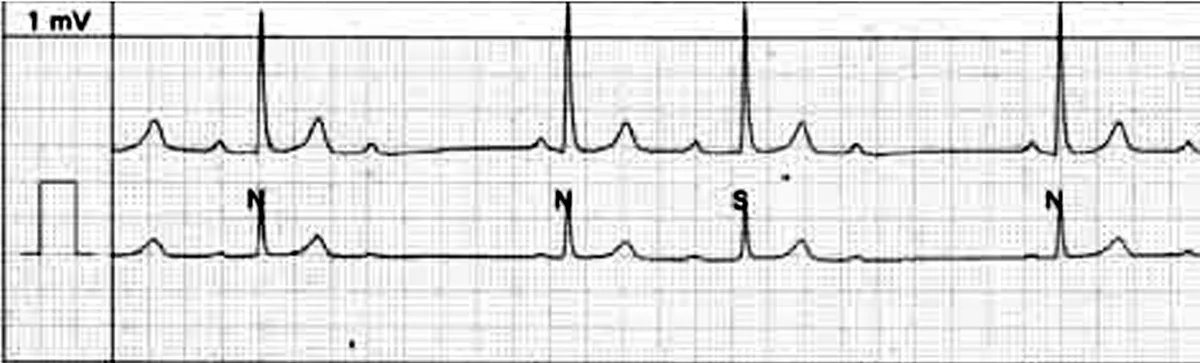
- Second-degree AV block, Mobitz type II: constant PR interval with intermittently nonconducted beats, often in a fixed ratio (e.g. 3:1 or 4:1); the RR interval spanning the pause equals twice the normal RR interval. The block is located in the His bundle in about 25 % and in the bundle branches in the rest; Mobitz II is always pathological.
- High-grade second-degree AV block: every second or more P waves are blocked; because two P waves are never conducted in a row, distinguishing type I from type II is difficult.
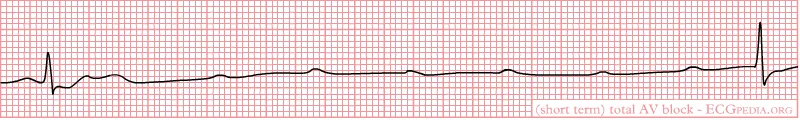
- Third-degree (complete) AV block: no P wave is conducted; atria and ventricles beat independently (AV dissociation), and the atrial rate is higher than the ventricular rate.
Occurrence & epidemiology
First-degree AV block and Mobitz I may be physiological in younger people with high vagal tone and in well-trained athletes. In people aged 18 to 60 years with new-onset Mobitz II or third-degree AV block without evident structural heart disease, up to one third are diagnosed with cardiac sarcoidosis after targeted investigation.
Aetiopathogenesis
- Idiopathic fibrosis and sclerosis of the conduction system: most common cause (about 40 %)
- Ischemic heart disease: about 20 %. In acute inferior infarction the block is usually located in the AV node (increased vagal tone, local adenosine release) and often resolves within a few days; in anterior infarction it indicates extensive necrosis involving the His-Purkinje system.
- Drugs that slow AV conduction, e.g. certain antiarrhythmic and rate-slowing cardiac drugs
- Other causes: increased vagal tone, cardiac sarcoidosis, valvular heart disease, congenital and genetic disorders
- Transient or reversible causes: Lyme carditis and neurally (vagally) mediated block
Clinical features
Symptoms by degree
- First-degree AV block: rarely symptomatic; with a very long PR interval (over 0.30 s), loss of AV synchrony can cause exertional dyspnea and fatigue.
- Mobitz I: often asymptomatic; usually progresses slowly.
- Mobitz II: asymptomatic or with light-headedness, presyncope and syncope, depending on the ratio of conducted to blocked beats; progression to complete block is typical and may be sudden.
- Third-degree AV block: an escape rhythm above the bifurcation of the His bundle (junctional) has narrow QRS complexes, a rate of about 35–50/min and is relatively reliable; symptoms tend to be mild (fatigue, postural light-headedness, effort intolerance). An escape rhythm below the bifurcation (ventricular) has wide QRS complexes, only 20–40/min, is unreliable and causes presyncope, syncope and heart failure.
- Adams-Stokes attack: sudden loss of consciousness due to asystole when no escape rhythm takes over; the risk is greatest with slow escape rhythms.
- Signs of AV dissociation: cannon a waves in the jugular venous pulse, fluctuating blood pressure, varying loudness of the first heart sound.
Diagnosis
ECG
- 12-lead ECG with rhythm strip: the ratio of P waves to QRS complexes, behavior of the PR interval, QRS width and escape rate indicate the degree and likely level of the block.
- Clues to the level of block: a narrow QRS in Mobitz I indicates block in the AV node; with a wide QRS (over 0.12 s) it lies in the His-Purkinje system in about 60–70 %.
- In Wenckebach block the RR interval spanning the pause is shorter than two normal RR intervals; in Mobitz II it equals exactly two RR intervals.
Further tests
- 24-hour ambulatory ECG and exercise testing: detection of intermittent block and assessment of AV nodal and infranodal conduction
- Electrophysiological study: localization of the block (nodal or infranodal), e.g. after spontaneous resolution of a block
- Search for the cause: drug history, signs of acute infarction, Borrelia serology if Lyme carditis is suspected, echocardiography if structural heart disease is suspected; in younger adults with unexplained high-grade block, targeted evaluation for cardiac sarcoidosis
Treatment principles
- Reversible causes are sought and treated first, such as rate-slowing drugs, electrolyte disturbances, ischaemia or Lyme carditis.
- First-degree AV block and Wenckebach block usually need no treatment, whereas high-grade AV block (Mobitz II, third degree) is usually an indication for pacemaker implantation.
- Acute symptomatic bradycardia is treated with parasympatholytics or catecholamines and, if there is no response, with transcutaneous or temporary transvenous pacing.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- AV nodal re-entrant tachycardia (AVNRT)
- Brugada syndrome
- Chronic coronary syndrome (stable coronary artery disease)
- Dilated cardiomyopathy
- Dressler syndrome (post-myocardial infarction syndrome)
- Hypercholesterolemia and familial hypercholesterolemia
- Hypertensive emergency and hypertensive crisis
- Hypertrophic cardiomyopathy
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.