Arterial hypertension (high blood pressure)
Board exam relevance: in 15 of more than 100 exam reports · rank 12- Synonyms
- high blood pressure, HBP, essential hypertension, primary hypertension, white coat hypertension, masked hypertension, isolated systolic hypertension
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 1 · Clinical 1 · Gross specimen 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (3)
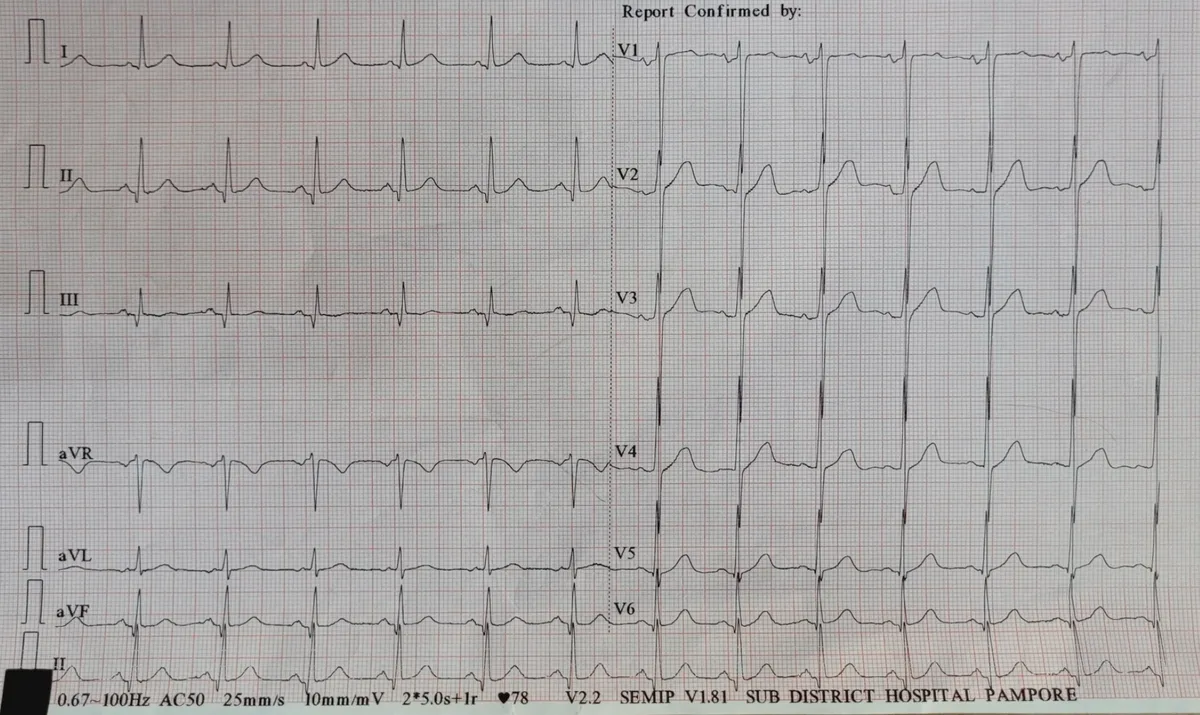 ECG
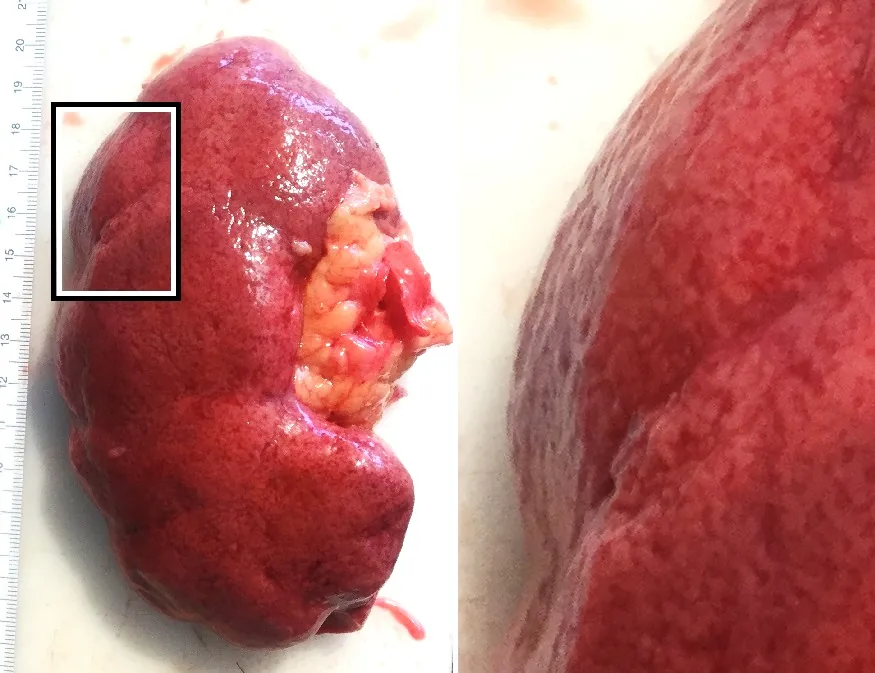 Gross specimen
Definition
Arterial hypertension is a persistent elevation of arterial blood pressure. According to the German National Care Guideline (NVL, based on ESC/ESH 2018), it is present at an office blood pressure measured in the sitting position of 140/90 mmHg or higher. US guidelines set the threshold at 130/80 mmHg.
A distinction is made between primary (essential) hypertension without an identifiable single cause, which accounts for the large majority at about 85 %, and secondary hypertension with an identifiable cause.
Classification
Grades (office measurement)
- Grade 1: systolic 140–159 and/or diastolic 90–99 mmHg
- Grade 2: systolic 160–179 and/or diastolic 100–109 mmHg
- Grade 3: systolic 180 or higher and/or diastolic 110 or higher
- Isolated systolic hypertension: systolic 140 or higher with diastolic below 90 mmHg (also subdivided into grades 1–3)
- White coat hypertension: elevated values only when measured in the office, normal outside
- Masked hypertension: persistently elevated outside the office but normal in the office; clues are reported high home readings, widely fluctuating values or organ damage without known hypertension
Occurrence & epidemiology
In Germany, about one third of adults are affected: in the DEGS1 study with standardized measurement the point prevalence was 31.6 % (men 33.3 %, women 29.9 %). Among people aged 65 and over, almost two thirds reported hypertension in the GEDA study (women 63.8 %, men 65.1 %). Worldwide the age-standardized prevalence in people aged 30 to 79 is about one third; in high-income countries about 27–31 % of those affected are unaware of their hypertension.
Aetiopathogenesis
Primary hypertension has no single cause; plasma volume, activity of the renin-angiotensin-aldosterone system and sympathetic activity are variously altered, and usually several factors act together. Because blood pressure equals cardiac output times peripheral vascular resistance, peripheral resistance is usually increased with normal or slightly increased cardiac output. Abnormal sodium transport, reduced nitric oxide production and increasing arterial stiffness with age (isolated systolic hypertension) contribute.
Risk factors: obesity, smoking, hazardous alcohol use, diabetes mellitus, hyperlipidemia, physical inactivity and stress; high sodium intake raises blood pressure mainly in genetically susceptible people and at older age.
Clinical features
Symptoms and organ damage
Hypertension is usually asymptomatic until complications develop in target organs; even very high values may cause no symptoms. Possible complaints are headache, dizziness, visual disturbances, exertional dyspnea, angina, palpitations and nocturia.
- Heart: left ventricular hypertrophy, heart failure, coronary artery disease, atrial fibrillation
- Brain: stroke, transient ischemic attack, cognitive impairment up to dementia
- Kidney: chronic kidney disease with albuminuria
- Vessels: atherosclerosis, peripheral artery disease, aortic dissection and abdominal aortic aneurysm
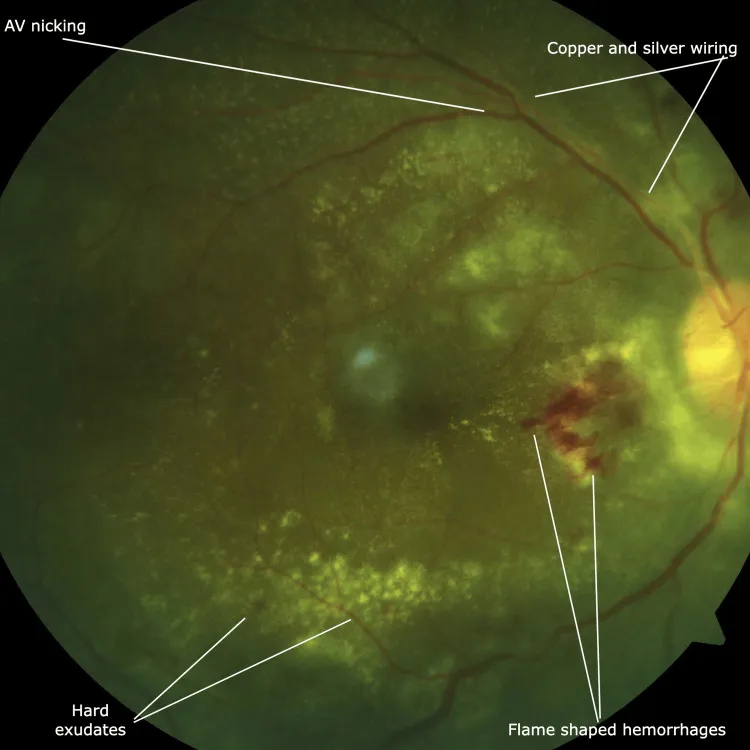
- Eyes: hypertensive retinopathy according to Keith-Wagener-Barker: grade 1 arteriolar narrowing only, grade 2 narrowing and sclerosis, grade 3 additional hemorrhages and exudates, grade 4 papilledema
Diagnosis
Blood pressure measurement
- Office measurement: after at least 5 minutes of rest in the sitting position on the upper arm, e.g. three readings 2 minutes apart using the mean of the 2nd and 3rd reading; threshold 140/90 mmHg
- 24-hour ambulatory blood pressure measurement: thresholds daytime mean 135/85, 24-hour mean 130/80 and nighttime mean 120/70 mmHg; detects white coat and masked hypertension and loss of the nocturnal dip
- Home measurement: two readings morning and evening over seven days; threshold 135/85 mmHg
Basic work-up and organ damage
- History: symptoms, cardiovascular disease, diabetes, kidney disease, sleep apnea, hypertension in pregnancy, blood pressure-raising drugs and substances (e.g. analgesics, oral contraceptives, licorice, caffeine, recreational drugs), snoring
- Examination: height, weight, waist circumference, auscultation of heart, neck and abdomen (bruits), pulse examination, fundoscopy, neurological status
- Laboratory tests: sodium, potassium, eGFR (creatinine), lipid profile, fasting glucose or HbA1c, urinalysis; urine albumin-creatinine ratio at initial diagnosis (in chronic kidney disease and also without known kidney disease)
- 12-lead ECG: signs of left ventricular hypertrophy, ischemia or arrhythmias; echocardiography if hypertrophy is suggested
Treatment principles
- Lifestyle measures such as salt reduction, weight loss, regular exercise, reduced alcohol intake and smoking cessation form the basis.
- Drug therapy usually starts with a dual combination of a RAS inhibitor (ACE inhibitor or angiotensin receptor blocker) and a calcium channel blocker or thiazide diuretic, preferably as a single-pill combination, extended to a triple combination if needed; beta blockers are used for specific indications.
- In resistant hypertension, secondary causes are investigated and mineralocorticoid receptor antagonists are added; targets are set individually and checked regularly.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Atrioventricular block
- AV nodal re-entrant tachycardia (AVNRT)
- Brugada syndrome
- Chronic coronary syndrome (stable coronary artery disease)
- Dilated cardiomyopathy
- Dressler syndrome (post-myocardial infarction syndrome)
- Hypercholesterolemia and familial hypercholesterolemia
- Hypertensive emergency and hypertensive crisis
- Hypertrophic cardiomyopathy
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.