AV nodal re-entrant tachycardia (AVNRT)
Board exam relevance: in 3 of more than 100 exam reports · rank 111- Synonyms
- AVNRT, AV nodal reentry, paroxysmal supraventricular tachycardia, PSVT, SVT, racing heart, palpitations
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
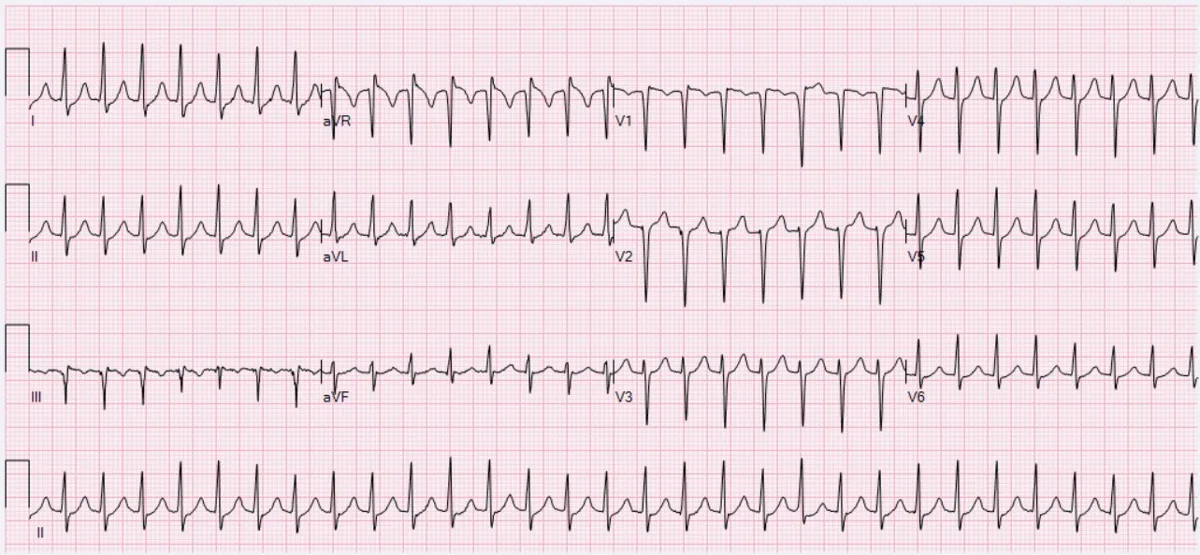 ECG
Definition
AV nodal reentrant tachycardia (AVNRT) is a paroxysmal supraventricular tachycardia in which the reentrant circuit lies within the AV node and its inputs. Paroxysmal supraventricular tachycardias are sudden-onset, sudden-offset, rapid (120–250/min), regular tachycardias, usually with a narrow QRS complex, that are neither sinus tachycardia nor atrial fibrillation or flutter.
Classification
- Typical AVNRT (slow-fast): antegrade conduction via the slow pathway, retrograde via the fast pathway; about 90 % of cases
- Atypical AVNRT (fast-slow): reentry in the opposite direction, more often triggered by a ventricular premature beat; P wave in the second half of the RR interval (long RP tachycardia)
Occurrence & epidemiology
Paroxysmal supraventricular tachycardias have an incidence of about 35 per 100,000 and a prevalence of 2–3 per 1,000 people (US data). In adults AVNRT is the most common form at about 50–60 %; in children it is much less common. It usually occurs in people with otherwise healthy hearts, and symptoms typically begin in young adulthood or middle age.
Aetiopathogenesis
The AV node has several inputs: a fast pathway (superior/anterior extension) with a longer refractory period and a slow pathway (inferior/posterior extension) with a shorter refractory period. An early atrial premature beat is blocked in the still refractory fast pathway and conducted via the slow pathway; on the ECG the PR interval of this beat suddenly lengthens. If conduction is slow enough, the fast pathway can be activated retrogradely, and a reentrant circuit within the AV node develops.
Clinical features
Typical are paroxysmal, sudden-onset, sudden-offset, rapid, regular palpitations, often with dyspnea, chest discomfort or light-headedness. Attacks last seconds to hours, rarely longer than 12 hours. The heart rate is 120–240/min, most commonly 180–210/min; between attacks the examination is usually unremarkable.
Diagnosis
- ECG: rapid, regular narrow-complex tachycardia; wide QRS complexes only with coexisting bundle branch block
- Typical AVNRT: retrograde P waves usually in the terminal portion of the QRS complex, often seen as a pseudo-r′ in V1; about one third lie just after the QRS complex, very few immediately before it; the P wave is negative in II, III and aVF
- Atypical AVNRT: P wave in the second half of the RR interval (RP longer than PR)
- Previous ECGs are reviewed for pre-excitation (WPW) or pre-existing bundle branch block; the resting ECG is usually normal in AVNRT.
- Ambulatory ECG or event recorder for infrequent attacks; electrophysiological study demonstrates dual AV nodal conduction.
Treatment principles
- In haemodynamic instability, immediate electrical cardioversion is performed.
- In stable patients, vagal manoeuvres are tried first and, if unsuccessful, short-acting AV nodal blocking drugs are given under ECG monitoring.
- For prevention of recurrence, catheter ablation of the slow pathway is curative with a high success rate and is usually the treatment of choice; alternatively, beta blockers or non-dihydropyridine calcium channel blockers may be used.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Brugada syndrome
- Chronic coronary syndrome (stable coronary artery disease)
- Dilated cardiomyopathy
- Dressler syndrome (post-myocardial infarction syndrome)
- Hypercholesterolemia and familial hypercholesterolemia
- Hypertensive emergency and hypertensive crisis
- Hypertrophic cardiomyopathy
- Infective endocarditis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.