Arrhythmogenic right ventricular cardiomyopathy (ARVC)
- Synonyms
- ARVC, ARVD, arrhythmogenic cardiomyopathy, arrhythmogenic right ventricular dysplasia
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 1 · MRI 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
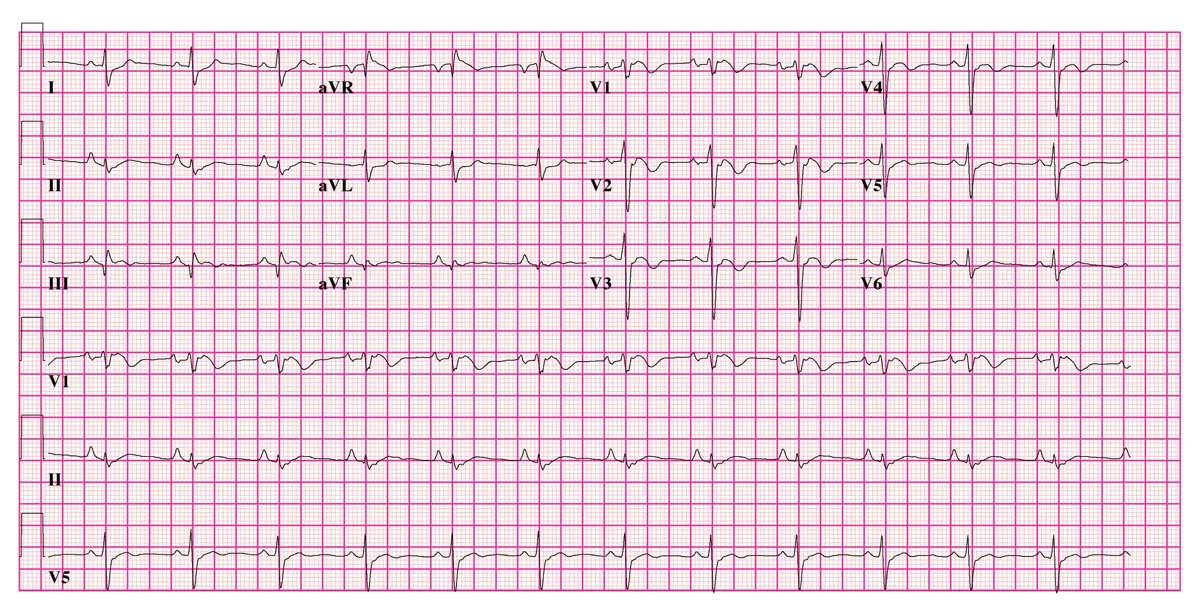 ECG
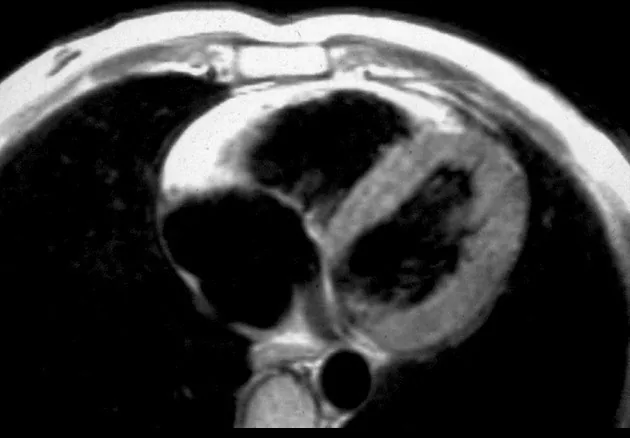 MRI
Definition
Arrhythmogenic right ventricular cardiomyopathy (ARVC), formerly arrhythmogenic right ventricular dysplasia (ARVD), is a genetic heart disease that mainly affects the right ventricle and causes ventricular tachyarrhythmias and an increased risk of sudden death. Variants are arrhythmogenic left ventricular (ALVC) and biventricular cardiomyopathy (ABVC); collectively the term arrhythmogenic cardiomyopathy is used.
Classification
Diagnostic criteria (task force)
An international task force has proposed major and minor criteria; depending on the combination, possible, borderline or definite disease of the right, left or both ventricles is diagnosed. The criteria include:
- imaging evidence of ventricular disease (often fibrous or fatty infiltration or replacement of myocardium)
- biopsy showing replacement of cardiomyocytes by fibrous and/or fatty tissue
- ECG repolarisation abnormalities, e.g. right precordial T-wave inversion
- ECG depolarisation abnormalities, e.g. right precordial epsilon waves
- late potentials on the signal-averaged ECG
- documented ventricular arrhythmias originating from scar (mostly right ventricular)
- family history of arrhythmogenic cardiomyopathy or sudden death
- identification of a disease-associated gene mutation
Occurrence & epidemiology
Frequency varies regionally between 1:2000 and 1:5000. ARVC and its variants account for about 10 % of sudden cardiac deaths not explained by coronary or other structural disease.
Aetiopathogenesis
- Genetics: mutations mostly affect desmosomal proteins of the intercalated discs that mechanically connect cardiomyocytes – e.g. plakophilin, desmoplakin and desmoglein. Inheritance is mostly autosomal dominant with variable penetrance; autosomal recessive forms occur.
- Pathogenesis: the abnormal cell junctions are damaged by mechanical stress; during healing, cardiomyocytes are replaced by fibrous and fatty tissue – predominantly in the triangle between the right ventricular outflow tract, inflow tract and apex, sometimes also in the posterolateral left ventricle.
- Course: initially ventricular ectopic beats and tachyarrhythmias predominate, later structural changes of the right ventricle (dilatation, wall thinning) up to heart failure.
- Sustained heavy exertion, such as endurance sport, is thought to hasten onset and progression.
Clinical features
- Patients may be asymptomatic.
- First manifestation is frequently syncope, sustained ventricular tachycardia, ventricular fibrillation or sudden death; arrhythmias occur particularly during emotional or physical stress.
- Palpitations and syncope.
- Atrial fibrillation and signs of right and/or left ventricular failure usually indicate advanced disease.
Histology
The characteristic finding is replacement of cardiomyocytes by fibrous and fatty tissue. Biopsy findings from the right ventricle are often non-specific because of patchy involvement; biopsy is therefore rarely performed.
Diagnosis
- Suspicion: particularly in young people with palpitations, cardiac syncope, documented ventricular tachyarrhythmias or survived unexplained cardiac arrest without evident structural heart disease.
- ECG: ventricular tachycardia with left bundle branch block morphology (right ventricular origin) and a superior axis – the axis helps to distinguish it from the usually benign idiopathic outflow tract tachycardia with an inferior axis; right precordial T-wave inversion, epsilon waves.
- Imaging: echocardiography, cardiac MRI, possibly cardiac CT or right ventricular angiography.
- Rhythm assessment: exercise testing, ambulatory ECG, electrophysiological study, signal-averaged ECG.
- Genetic testing: yield about 50–70 % when the diagnostic criteria are met; assessment of first-degree relatives.
Treatment principles
- The most important general measure is avoiding competitive and intensive endurance sport, as exertion promotes progression.
- Beta blockers and, if necessary, antiarrhythmic drugs are used for rhythm control, catheter ablation may be considered for recurrent ventricular tachycardia, and an ICD is implanted after survived cardiac arrest or in high-risk patients.
- Heart failure is treated according to guidelines, and heart transplantation is considered at end stage; relatives are offered cardiological and genetic screening.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Atrioventricular block
- AV nodal re-entrant tachycardia (AVNRT)
- Brugada syndrome
- Chronic coronary syndrome (stable coronary artery disease)
- Dilated cardiomyopathy
- Dressler syndrome (post-myocardial infarction syndrome)
- Hypercholesterolemia and familial hypercholesterolemia
- Hypertensive emergency and hypertensive crisis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.