Infectious mononucleosis (glandular fever) – skin and mucosal signs
- Synonyms
- Pfeiffersches Drüsenfieber, Mononukleose, EBV-Infektion, Epstein-Barr-Virus, Mononukleose-Exanthem, Gaumenpetechien, glandular fever, mono, EBV infection, mononucleosis rash
- Specialty
- Dermatology · Viral infections
- Images
- Clinical 1
- In the app
- 2 flashcards
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
Infectious mononucleosis is an infection usually caused by Epstein-Barr virus (EBV, human herpesvirus 4), with fever, pharyngitis, lymphadenopathy and fatigue. Cytomegalovirus can also cause a similar picture.
Occurrence & epidemiology
It typically affects young adults aged 15–25 years, both sexes equally. Over 95% of adults are EBV-seropositive; in young children, primary infection is usually asymptomatic. Transmission is mainly via saliva, for example by kissing.
Clinical features
- Incubation period usually 6–7 weeks; fever, pharyngitis, cervical lymphadenopathy, splenomegaly (in about 50%), periorbital oedema.
- Enanthem: petechiae on the hard and soft palate in about 50% of young adults during the first days of illness.
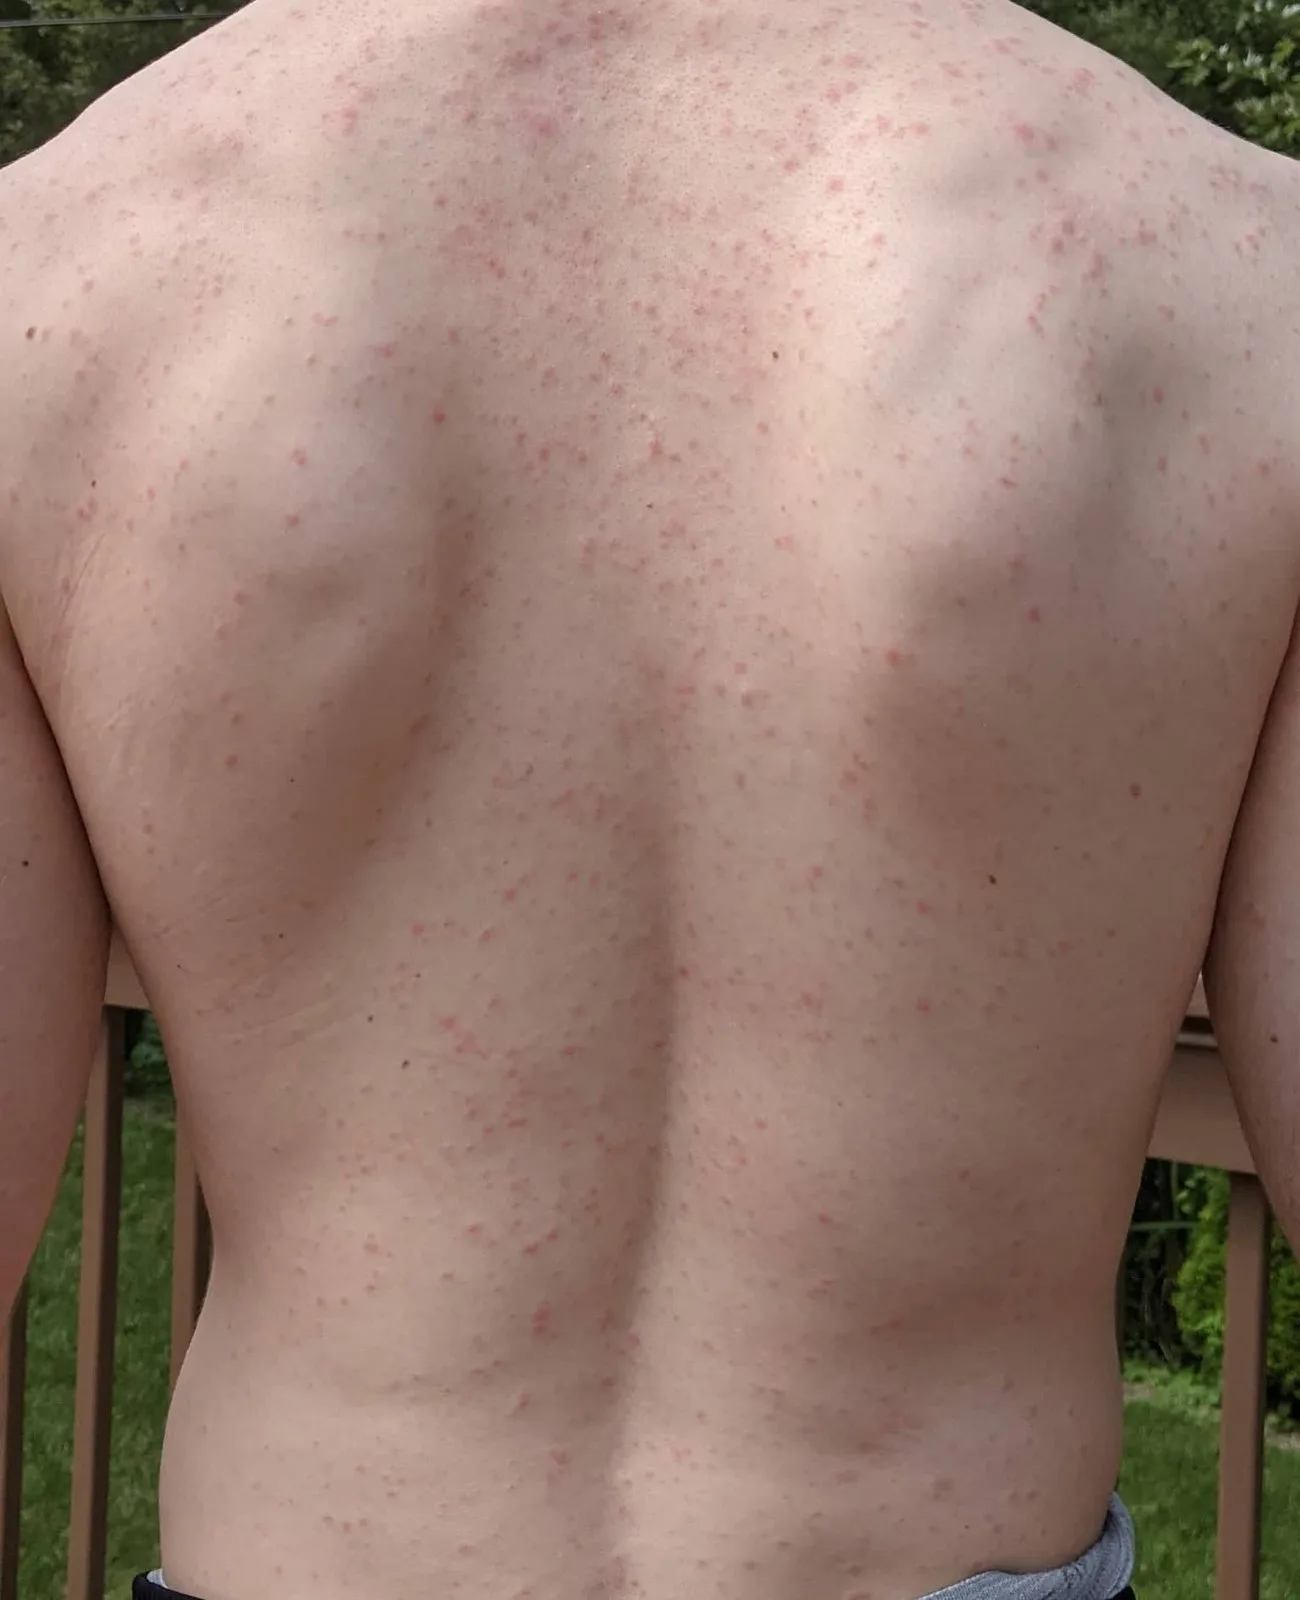
- Exanthem: generalised maculopapular, usually faint and non-itchy, starting on the trunk and upper arms and spreading to the face and forearms; also morbilliform, scarlatiniform, vesicular or purpuric; resolves after about a week. Frequency without antibacterial drugs 4.2–13%, according to more recent data up to about 20%.
- After starting antibacterial drugs, a more intense, itchy maculopapular drug eruption may appear (including extensor surfaces, trunk, palms and soles); the previously reported frequency of up to 90% is now considered far too high.
- Less common: itchy jaundice with excoriations, immune thrombocytopenia, cold urticaria, erythema nodosum.
Diagnosis
- Heterophile antibodies (Monospot): positive in 85–90% of adolescents and adults, but only in about 50% of children aged 2–5 years; often still negative in the first week of illness.
- Blood count: lymphocytosis with atypical lymphocytes (up to 30% of white cells); transaminases often raised.
- EBV-specific serology: VCA IgM indicates primary infection; VCA IgG appears early and persists for life; EBNA IgG appears only after 2–4 months.
Differential diagnoses
Keep learning in the app
References (selection)
Cross-references
Note: This page is intended for medical education and does not replace diagnosis or treatment decisions in individual cases.