Waldenström macroglobulinemia
- Synonyms
- Waldenström disease, macroglobulinemia, lymphoplasmacytic lymphoma, IgM gammopathy
- Specialty
- Internal medicine · Haematology & oncology
- Images
- Clinical 1 · Blood smear & cytology 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
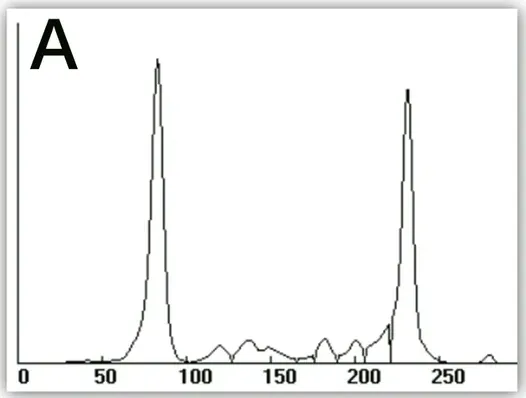
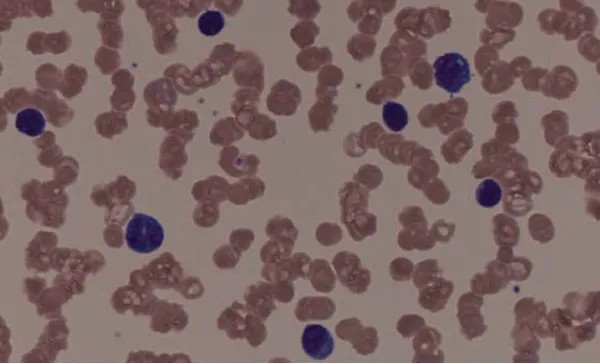 Blood smear & cytology
Definition
Waldenström macroglobulinemia is a lymphoplasmacytic lymphoma with bone marrow infiltration and production of a monoclonal IgM paraprotein. Clinically, the disease resembles an indolent lymphoma more than multiple myeloma; osteolytic lesions are usually absent. After myeloma, it is the second most common malignant disorder associated with a monoclonal gammopathy.
Occurrence & epidemiology
The disease is uncommon. The median age at diagnosis is about 70 years; men are affected more often than women.
Aetiopathogenesis
The cause is unknown. The hallmark mutation is MYD88 L265P in more than 90 % of lymphoplasmacytic lymphomas; CXCR4 mutations are found in up to about 40 %. IgM MGUS frequently precedes the disease. The large IgM pentamer increases plasma viscosity; some IgM paraproteins act as rheumatoid factors or cold agglutinins, and about 10 % are cryoglobulins. Amyloidosis occurs in about 5 %.
Clinical features
- Many patients are asymptomatic; diagnosis is often an incidental finding of IgM gammopathy.
- Anemia with fatigue and weakness.
- Hyperviscosity syndrome: fatigue, skin and mucosal bleeding, visual disturbances, headache, peripheral neuropathy, and changing neurologic deficits; increased plasma volume may precipitate heart failure.
- Fundus: sausage-like engorged, segmentally narrowed retinal veins; later retinal hemorrhages, exudates, microaneurysms, and papilledema.
- Lymphadenopathy, hepatosplenomegaly, purpura.
- Cold sensitivity, Raynaud syndrome, recurrent bacterial infections.
Diagnosis
- Protein studies: serum electrophoresis showing an M-protein, immunofixation (IgM; in urine often monoclonal light chains, mostly kappa), quantitative immunoglobulins (normal immunoglobulins reduced in half of patients), free light chains.
- Blood count: moderate normocytic, normochromic anemia, marked rouleaux formation, very high ESR; occasionally leukopenia, relative lymphocytosis, thrombocytopenia.
- Cryoglobulins, rheumatoid factor, cold agglutinins, direct Coombs test, coagulation studies; cold agglutinins and cryoglobulins may distort routine values.
- Plasma viscosity: with hyperviscosity usually > 4.0 mPa·s (normal 1.4–1.8); additionally retinal fluorescein angiography.
- Bone marrow examination: increase in plasma cells, lymphocytes, plasmacytoid lymphocytes, and mast cells; detection of MYD88 and CXCR4 mutations. Lymph node biopsy if the bone marrow is unremarkable.
Treatment principles
- Asymptomatic disease is monitored without treatment; therapy is indicated for symptoms such as hyperviscosity, cytopenias, B symptoms, neuropathy or organ involvement.
- Hyperviscosity syndrome is treated acutely with plasmapheresis.
- Systemic options include anti-CD20 antibodies combined with chemotherapy, or BTK inhibitors; with high IgM levels, antibody therapy is started cautiously because of a possible IgM flare.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Haematology & oncology
- Anemia (classification and work-up)
- Hemolytic anemias
- Acute myeloid leukemia (AML)
- Iron deficiency anemia
- Multiple myeloma
- Myelodysplastic syndromes (MDS)
- Non-Hodgkin lymphomas
- Superior vena cava syndrome
- Paraneoplastic syndromes
- Paroxysmal nocturnal hemoglobinuria (PNH)
- Polycythemia vera
- Primary myelofibrosis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Anemia (classification and work-up) · Hemolytic anemias · Acute myeloid leukemia (AML)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.