Febrile neutropenia
Board exam relevance: in 5 of more than 100 exam reports · rank 69- Synonyms
- neutropenic fever, neutropenic sepsis, fever in neutropenia, agranulocytosis, FN
- Specialty
- Internal medicine · Haematology & oncology
- Images
- CT 1 · Gross specimen 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
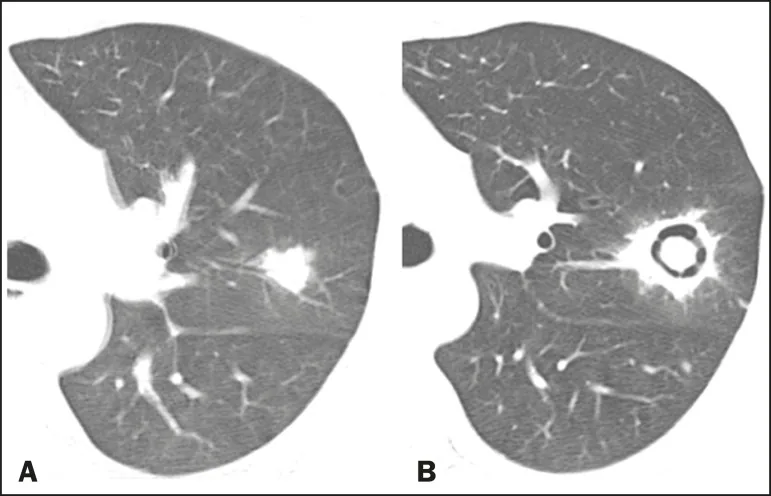 CT
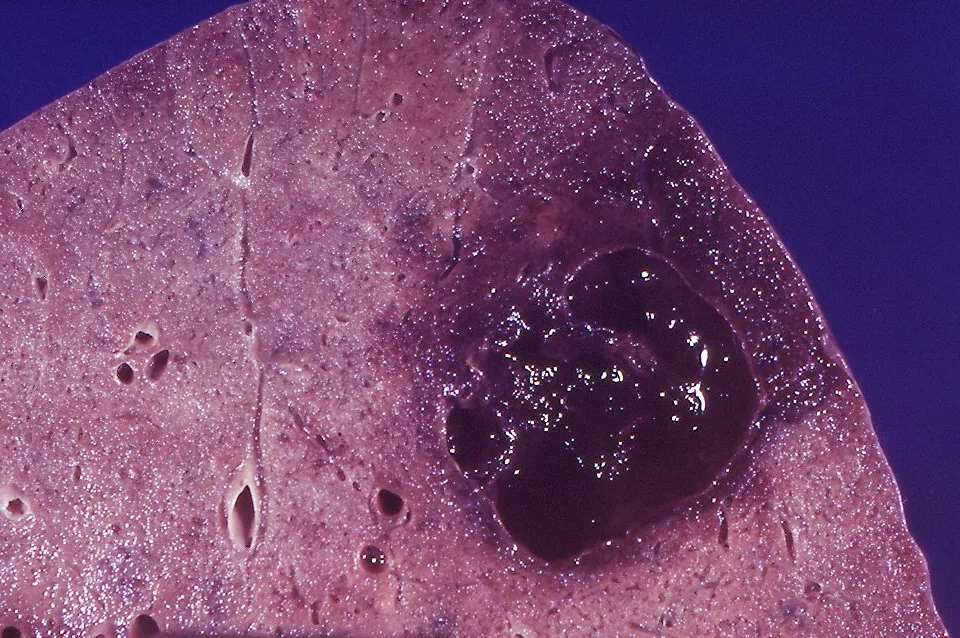 Gross specimen
Definition
Febrile neutropenia is fever with a markedly reduced neutrophil count, usually resulting from myelosuppressive cytotoxic drugs or bone marrow infiltration by hematologic neoplasms. It is regarded as an oncologic emergency.
- Definition according to IDSA, ASCO, and NCCN: oral temperature ≥ 38.3 °C once or sustained ≥ 38.0 °C over 1 hour and absolute neutrophil count < 0.5 × 10⁹/L or an expected decrease to < 0.5 × 10⁹/L within 48 hours.
- ESMO: sustained temperature > 38.0 °C over 2 hours.
- NICE (neutropenic sepsis): neutrophils ≤ 0.5 × 10⁹/L and temperature > 38 °C or other signs of clinically significant sepsis.
Severity of neutropenia: mild 1,000–1,500/µL, moderate 500–1,000/µL, severe < 500/µL; below 200/µL the term agranulocytosis is used.
Clinical features
- Fever is often the only sign of infection.
- In severe neutropenia, typical signs of inflammation (redness, swelling, pain, infiltrates) are absent or only faint; below 200/µL, leukocytosis and pyuria may not occur.
- Local findings such as oral ulcers, stomatitis, or pharyngitis are often subtle.
- Common sites of infection: lung, bloodstream (bacteremia), skin and catheter exit sites, oral cavity, perianal region.
- Blood cultures show gram-positive and gram-negative organizms about equally often; in about half of patients, no pathogen and no focus can be found despite diagnostic work-up (fever of unknown origin).
- Risk of rapid progression to sepsis and septic shock; with prolonged neutropenia, increasingly invasive fungal infections.
Diagnosis
- Complete blood count with differential to determine the absolute neutrophil count.
- Thorough physical examination, repeated: skin and mucosa (including herpetic lesions), catheter exit sites, sinuses, ears, perianal region, fundus.
- Blood cultures: at least two sets from separate venipunctures, with an indwelling central venous catheter additionally from the catheter.
- Further cultures: urine; stool with diarrhea (including Clostridioides difficile); swabs of mucosal ulcers; material from skin lesions.
- Inflammatory markers: procalcitonin predicts bacteremia better than CRP; measured serially, they help detect complications early.
- Imaging: the conventional chest x-ray has low sensitivity in neutropenia; low-exposure chest CT in case of respiratory symptoms or suspected invasive aspergillosis; serum galactomannan and 1,3-beta-D-glucan.
- Risk assessment: the MASCC score estimates the risk of a complicated course (high risk < 21 points); the CISNE score is used in apparently stable patients. An expected duration of neutropenia of more than 7 days is considered high risk.
Treatment principles
- Febrile neutropenia is an emergency: after blood cultures are taken, empirical intravenous broad-spectrum antibiotic therapy is started without delay.
- Risk stratification determines whether oral or outpatient treatment is possible in low-risk patients; therapy is adjusted according to pathogen, focus of infection and course.
- With persistent fever, fungal infections are specifically sought and treated with antifungals, infected catheters are removed, and growth factors are used in selected situations.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Haematology & oncology
- Anemia (classification and work-up)
- Hemolytic anemias
- Acute myeloid leukemia (AML)
- Iron deficiency anemia
- Folate deficiency
- Glucose-6-phosphate dehydrogenase deficiency (favism)
- Hemolytic uremic syndrome (HUS)
- Hemophilia
- Heparin-induced thrombocytopenia (HIT)
- Hereditary spherocytosis
- Hodgkin lymphoma
- Immune thrombocytopenia (ITP)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Anemia (classification and work-up) · Hemolytic anemias · Acute myeloid leukemia (AML)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.