Tumor lysis syndrome
Board exam relevance: in 2 of more than 100 exam reports · rank 142- Synonyms
- TLS, tumour lysis syndrome, tumor lysis
- Specialty
- Internal medicine · Haematology & oncology
- Images
- Blood smear & cytology 1 · ECG 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
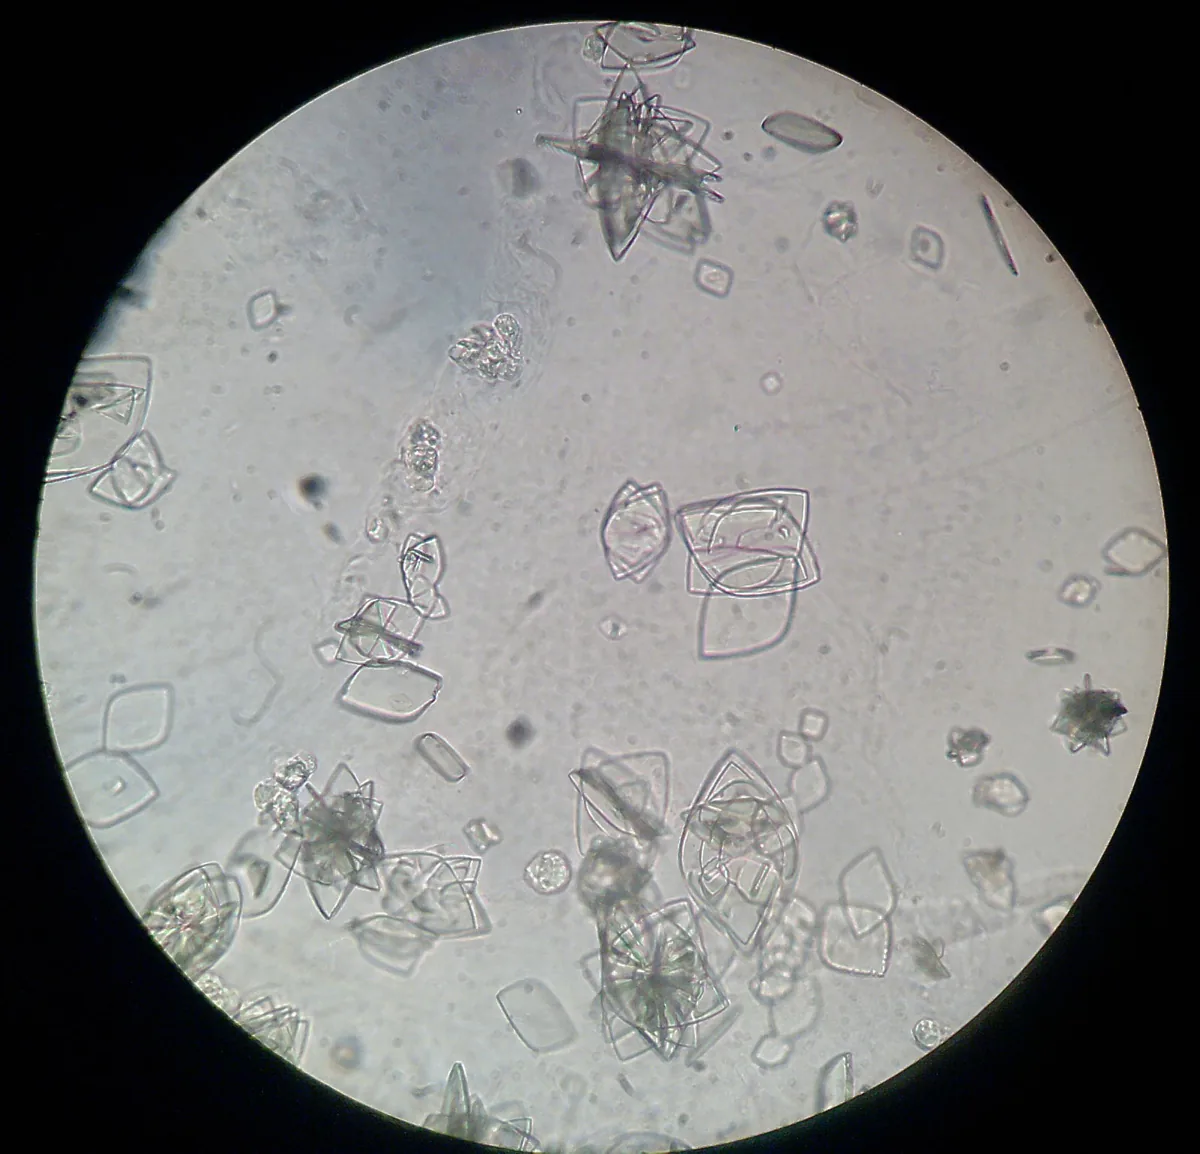 Blood smear & cytology
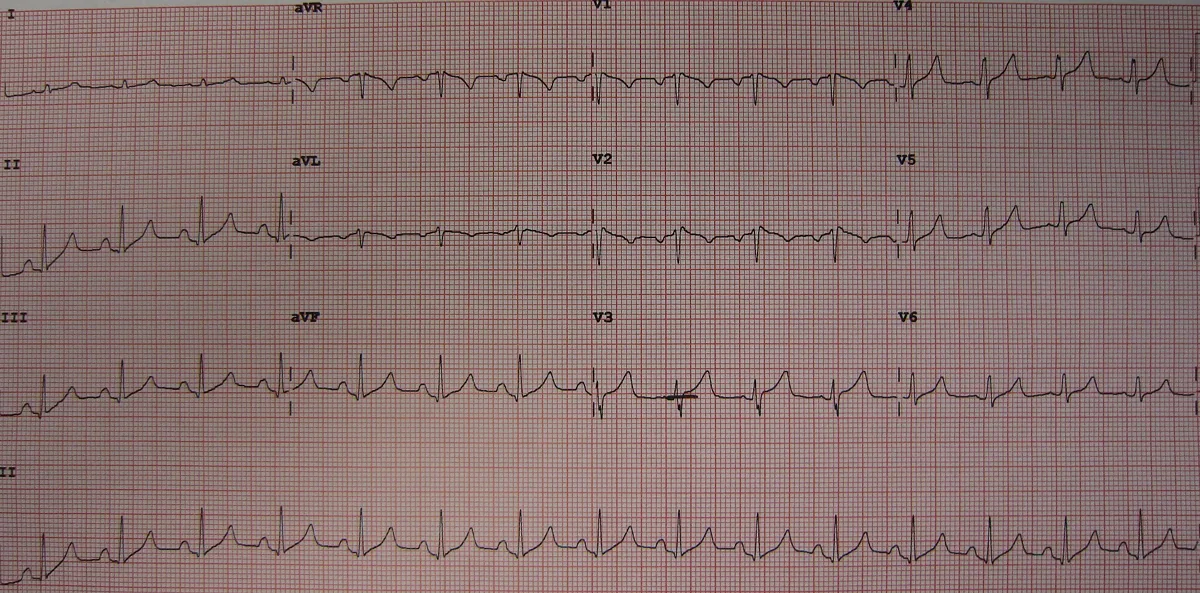 ECG
Definition
Tumor lysis syndrome (TLS) is a metabolic derangement caused by the rapid breakdown of large numbers of tumor cells. The released intracellular components lead to the typical constellation of hyperuricemia, hyperkalemia, hyperphosphatemia, and secondary hypocalcemia. Uric acid arises from the breakdown of released nucleic acids. Uric acid and calcium phosphate can precipitate in the renal tubules and cause acute kidney injury; calcium phosphate can also deposit in the cardiac conduction system.
TLS usually occurs within a few days after cytotoxic drugs are started, less often spontaneously before any anticancer measures. Rapidly growing, bulky hematologic neoplasms such as aggressive non-Hodgkin lymphomas (particularly Burkitt lymphoma and diffuse large B-cell lymphoma), acute lymphoblastic and acute myeloid leukemia are most often affected; in solid tumors it is rare.
Clinical features
Symptoms reflect the metabolic disturbances:
- nausea, vomiting, diarrhea, anorexia, lethargy
- muscle pain and cramps, paresthesias
- Hypocalcemia: neuromuscular hyperexcitability with tetany, seizures, cardiac arrhythmias
- Hyperkalemia: muscle weakness up to paralysis, cardiac arrhythmias
- Acute kidney injury due to urate nephropathy and nephrocalcinosis, with oliguria
- syncope, in severe cases sudden cardiac death
Diagnosis
Diagnostic criteria
The Cairo-Bishop criteria (2004), modified in 2011 by Howard and colleagues, are commonly used:
- Laboratory TLS: at least two of the following abnormalities within 3 days before to 7 days after the start of cytotoxic drugs: uric acid ≥ 476 µmol/L (8 mg/dL), potassium ≥ 6 mmol/L, phosphate ≥ 1.45 mmol/L (adults), calcium ≤ 1.75 mmol/L, or a 25 % change of the respective value from baseline.
- Clinical TLS: laboratory TLS plus at least one organ manifestation: creatinine increase to > 1.5 times normal, cardiac arrhythmia or sudden death, seizure.
- According to Howard, the laboratory abnormalities count only if they occur together within 24 hours; a mere 25 % change from baseline is no longer sufficient, and symptomatic hypocalcemia always counts as a criterion of clinical TLS.
Investigations
- Laboratory tests: potassium, phosphate, calcium, uric acid, creatinine, and urea; LDH as a marker of high cell turnover; complete blood count with white cell count.
- Findings with increased TLS risk: high tumor burden (tumors > 10 cm), leukocytosis (> 25,000/µL), LDH > 2 times normal, preexisting renal insufficiency or elevated uric acid, hypovolemia.
- ECG: hyperkalemia and hypocalcemia can cause ECG changes and cardiac arrhythmias.
- Urine output to detect oliguria; other causes of acute kidney injury are to be distinguished.
Treatment principles
- The key is risk-adapted prophylaxis before tumour therapy begins, with generous hydration, urate-lowering drugs and close laboratory monitoring.
- In established tumour lysis syndrome, electrolyte disturbances, particularly hyperkalaemia and hyperphosphataemia, are corrected specifically and patients are monitored by cardiac telemetry.
- Dialysis is started early for acute kidney injury, refractory electrolyte disturbances or fluid overload.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Haematology & oncology
- Anemia (classification and work-up)
- Hemolytic anemias
- Acute myeloid leukemia (AML)
- Iron deficiency anemia
- Vitamin B12 deficiency and pernicious anemia
- Von Willebrand disease
- Acute lymphoblastic leukemia (ALL)
- Anemia of chronic disease (anemia of inflammation)
- Antiphospholipid syndrome
- Aplastic anemia
- Autoimmune hemolytic anemia (AIHA)
- Chronic lymphocytic leukemia (CLL)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Anemia (classification and work-up) · Hemolytic anemias · Acute myeloid leukemia (AML)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.