Thromboangiitis obliterans (Buerger's disease)
- Synonyms
- Buerger disease, Winiwarter-Buerger disease, TAO, smoker's vasculitis
- Specialty
- Internal medicine · Angiology
- Images
- Clinical 2 · Angiography 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (3)
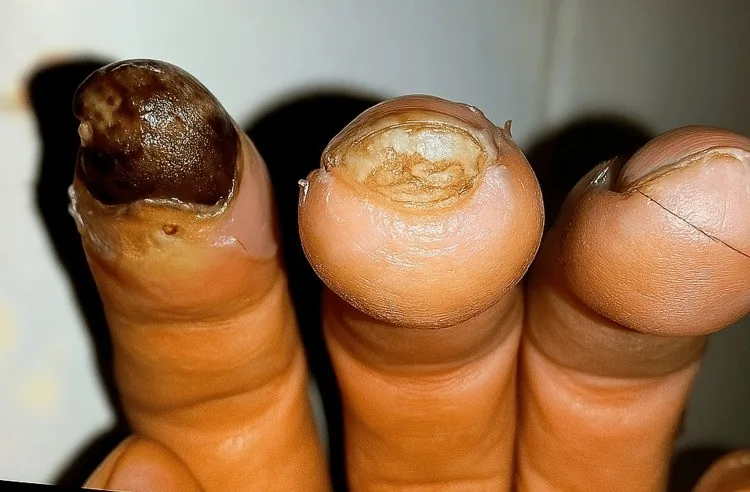
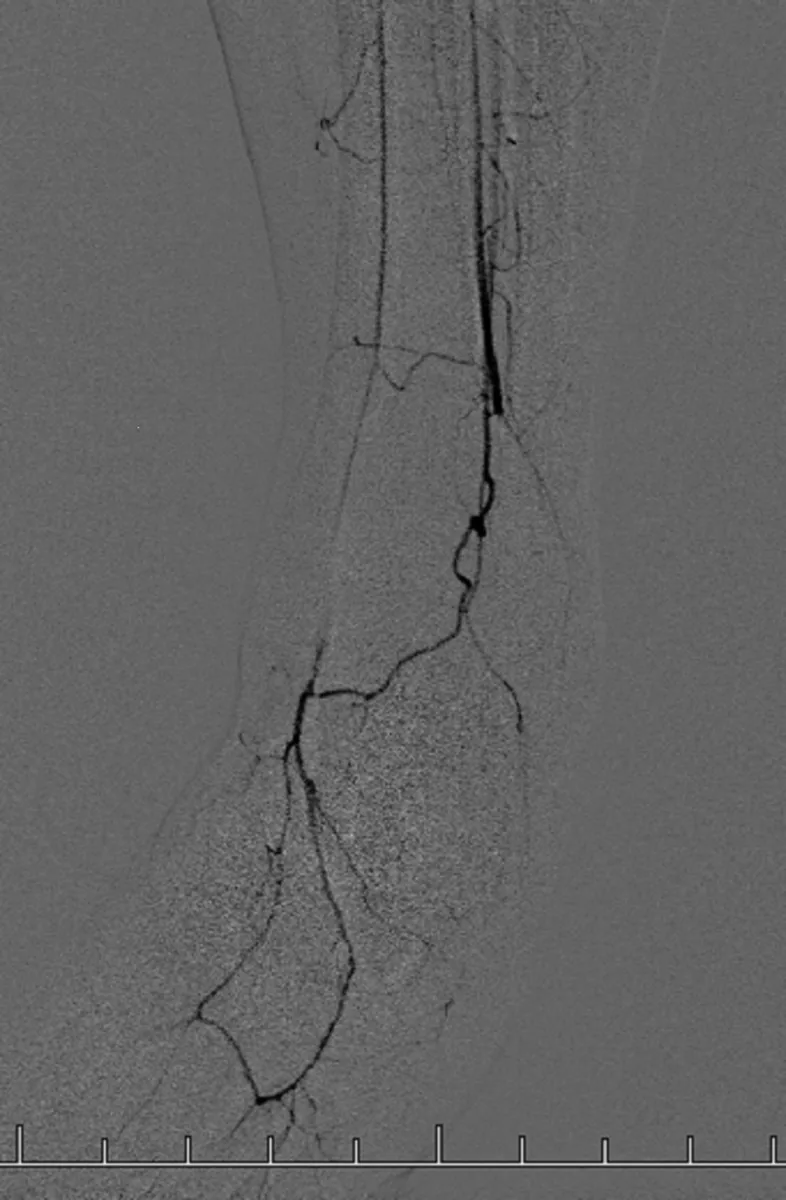 Angiography
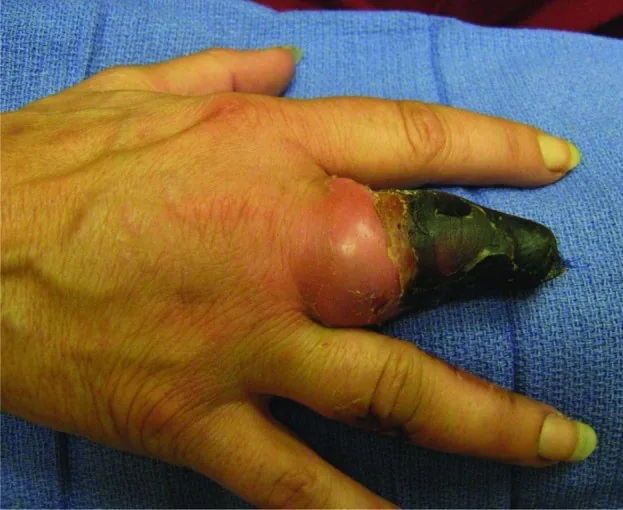
Definition
Thromboangiitis obliterans (Buerger's disease) is an inflammatory thrombosis of small and medium-sized arteries and some superficial veins. It causes arterial ischemia in the distal extremities and superficial thrombophlebitis. The main risk factor is tobacco use.
Occurrence & epidemiology
The disease occurs almost exclusively in people who use tobacco (nearly all of them smoke). It predominantly affects men aged 30 to 45 years and only rarely women. It is most common in Asia and the Middle East, where tobacco use is heavy.
Aetiopathogenesis
The cause is unknown; cigarette smoking is the main risk factor. Oxidative stress is involved in the mechanism, possibly also delayed hypersensitivity or toxic angiitis. According to another theory, it is an autoimmune disease with cell-mediated sensitisation to type I and III collagen of the vessel wall.
The disease causes segmental inflammation of small and medium-sized arteries and frequently of superficial veins of the extremities.
Clinical features
The symptoms are those of arterial ischemia and superficial venous thrombosis. Some patients have migratory phlebitis (thrombophlebitis migrans), usually in superficial veins of the foot or leg.
- gradual onset in the most distal vessels of the arms and legs with coldness, numbness, tingling or burning, sometimes before objective findings
- frequently Raynaud's phenomenon
- claudication, usually in the arch of the foot or the leg, rarely in the hand, arm or thigh; progression to rest pain
- with severe pain, a cold, sweating, cyanotic limb
- later ischemic ulcers progressing to gangrene, usually of one or more fingers or toes
- weak or absent pulses in the foot arteries, often also at the wrist
- pallor on elevation and redness when dependent
Histology
- Acute stage: occlusive thrombi with infiltration of the intima by neutrophils and lymphocytes; endothelial cells proliferate, but the internal elastic lamina remains intact
- Intermediate stage: the thrombi organize and recanalise incompletely; the media is preserved but may be infiltrated by fibroblasts
- Older lesions: periarterial fibrosis, sometimes also involving the adjacent vein and nerve
Diagnosis
History and findings suggest the diagnosis; other causes of ischemia are excluded by testing.
- Allen test: in young men who smoke and have extremity ulcers, a positive test (the hand remains pale after compression and alternating release of the radial and ulnar arteries) suggests the disease
- Ankle-brachial index or segmental pressure measurement: demonstration of distal ischemia; markedly reduced blood flow and pressures in the toes, feet and fingers
- Echocardiography: exclusion of cardiac emboli
- Laboratory tests: ANA, rheumatoid factor, complement, anticentromere and anti-Scl-70 antibodies to exclude vasculitis or connective tissue disease; antiphospholipid antibodies to exclude antiphospholipid syndrome (may be slightly raised in thromboangiitis obliterans)
- Angiography: typical are segmental occlusions of distal arteries in the hands and feet, tortuous corkscrew collaterals around the occlusions and absence of atherosclerosis
Treatment principles
- The most important, and the only disease-modifying, measure is complete and permanent cessation of tobacco in any form.
- In addition, ischaemic lesions are carefully managed, pain is treated and vasoactive agents such as prostanoids are used.
- Revascularisation is rarely possible because of the distal pattern of disease; amputation is avoided as far as possible through tobacco abstinence and early wound care.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Pulmonary embolism · Deep vein thrombosis · Abdominal aortic aneurysm
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.