Mechanical complications of myocardial infarction
Board exam relevance: in 4 of more than 100 exam reports · rank 90- Synonyms
- post-MI complications, ventricular septal rupture, post-infarction VSD, papillary muscle rupture, free wall rupture, cardiac rupture, ventricular aneurysm, pseudoaneurysm
- Specialty
- Internal medicine · Cardiology
- Images
- Gross specimen 1 · ECG 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
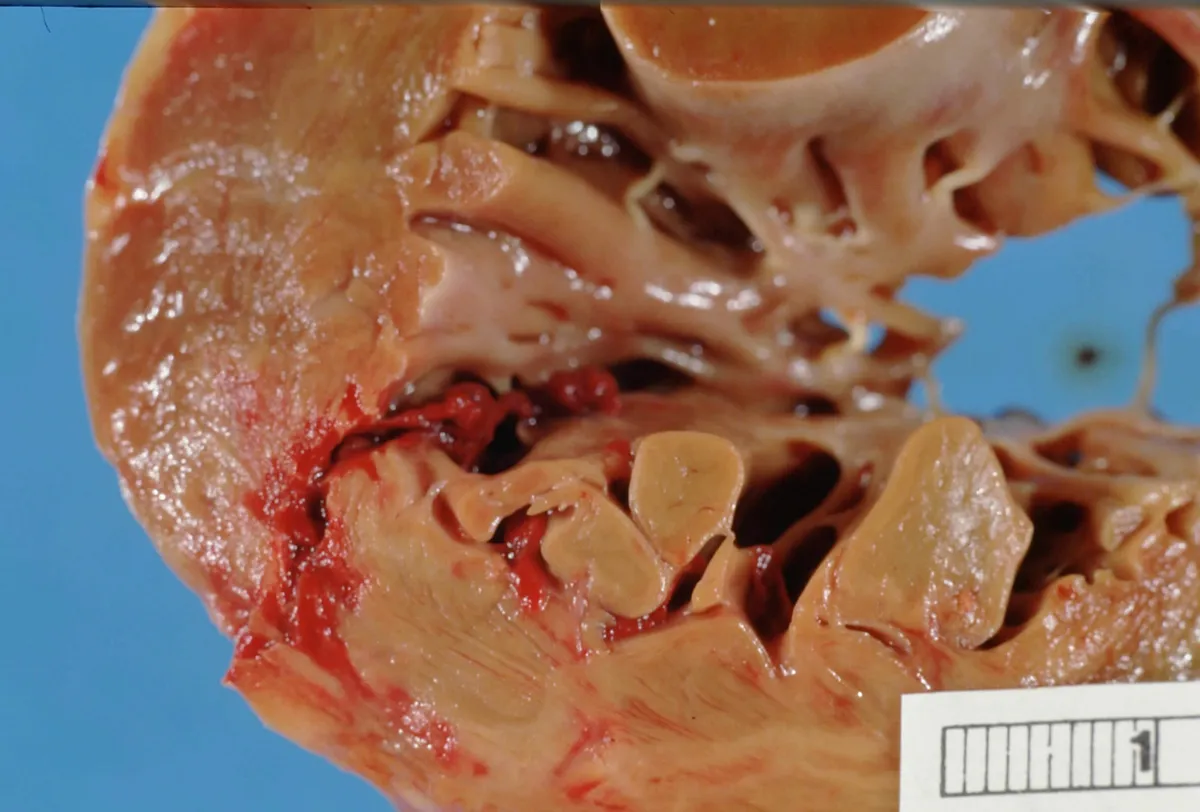 Gross specimen
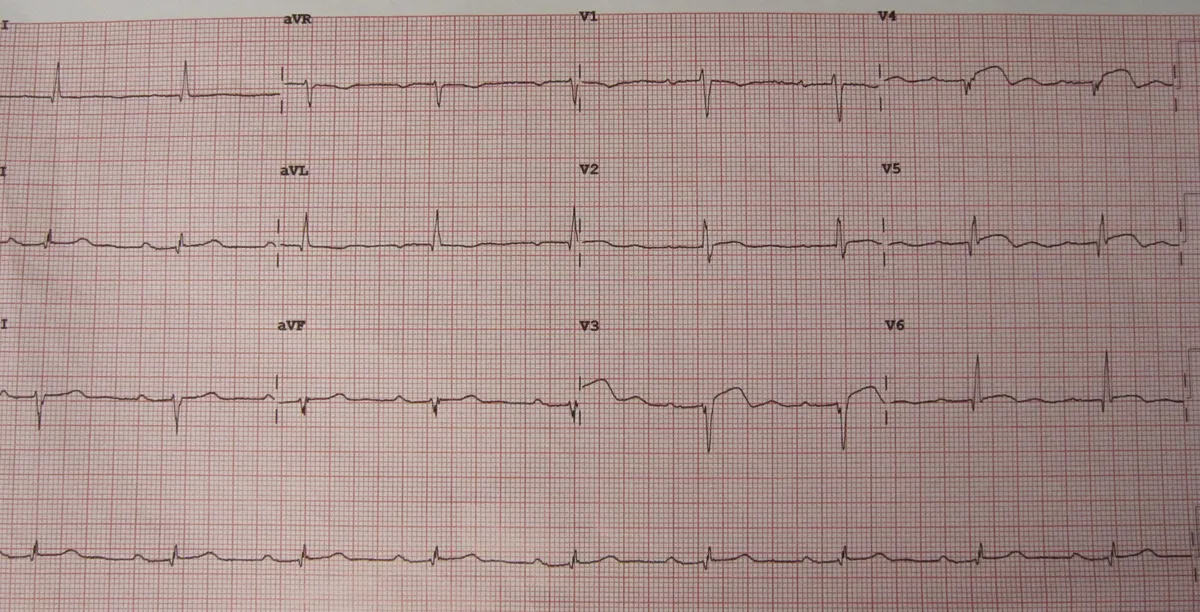 ECG
Definition
Mechanical complications of myocardial infarction are structural defects of the heart resulting from myocardial necrosis. The classic forms are ventricular septal rupture (post-infarction VSD), papillary muscle rupture with acute mitral regurgitation and rupture of the ventricular free wall. In a broader sense, ventricular aneurysm and pseudoaneurysm (contained rupture) are also included.
This is to be distinguished from functional, ischemic papillary muscle dysfunction, which is usually transient.
Occurrence & epidemiology
Rupture of the ventricular septum or free wall occurs in about 1 % of acute myocardial infarctions, septal rupture alone in about 0.3 %. Women have higher overall rates of mechanical complications; septal rupture is also more common in older people and after delayed reopening of the vessel. Free wall rupture is considered an important cause of out-of-hospital sudden cardiac death; its exact frequency is unknown.
Aetiopathogenesis
In the first days after infarction the necrotic tissue is broken down by macrophages before a stable scar forms; the wall is particularly soft in this phase. Large transmural infarctions are particularly at risk.
- Papillary muscle rupture: most often after inferoposterior infarction due to occlusion of the right coronary or circumflex artery; it affects the posteromedial papillary muscle, which has a single blood supply (the anterolateral one has a dual supply)
- Ventricular aneurysm: localized bulge of the wall, usually anterior or apical, especially after a large transmural anterior infarction; it may develop over days, weeks or months
- Pseudoaneurysm: incomplete rupture of the free wall (often inferior or lateral) contained by the pericardium
Clinical features
- Ventricular septal rupture: sudden loud systolic murmur with a thrill at the left sternal border in the third or fourth intercostal space, accompanied by hypotension with or without signs of left ventricular failure
- Papillary muscle rupture: acute severe mitral regurgitation with a sudden loud apical holosystolic murmur and thrill, usually with pulmonary edema; occasionally the severe regurgitation is silent on auscultation
- Free wall rupture: sudden loss of arterial pressure with momentary persistence of sinus rhythm (pulseless electrical activity), often with signs of cardiac tamponade
- Ventricular aneurysm: rarely ruptures but causes recurrent ventricular arrhythmias, low cardiac output and mural thrombi with systemic embolism
- Pseudoaneurysm: may become large and contribute to heart failure
Diagnosis
- Any abrupt hemodynamic deterioration and any new systolic murmur after an infarction raise suspicion of a mechanical complication.
- Echocardiography: key method to demonstrate a septal defect with shunt flow, a ruptured papillary muscle with severe mitral regurgitation, pericardial effusion and a wall defect
- Right heart catheterization: in septal rupture, a significant increase in oxygen content in the right ventricle compared with the right atrium (left-to-right shunt at ventricular level)
- Ventricular aneurysm: paradoxical precordial movements, persistent ST elevation on ECG and a characteristic bulge of the cardiac silhouette on chest radiograph; confirmation by echocardiography
Treatment principles
- Mechanical complications such as papillary muscle rupture, ventricular septal rupture or free wall rupture are emergencies with high mortality.
- Priorities are haemodynamic stabilisation with afterload reduction, as far as blood pressure allows, and inotropes, and if necessary mechanical circulatory support as a bridge.
- Definitive repair is surgical or, in selected cases, interventional, and the heart team decides without delay.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Mitral regurgitation
- Mitral stenosis
- Myocarditis
- Pericardial effusion and cardiac tamponade
- Pulmonary hypertension
- Rheumatic fever
- Bundle branch block (left and right)
- Secondary hypertension
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.