Pulmonary hypertension
Board exam relevance: in 2 of more than 100 exam reports · rank 142- Synonyms
- high blood pressure in the lungs, PH, pulmonary arterial hypertension, PAH, CTEPH
- Specialty
- Internal medicine · Cardiology
- Images
- X-ray 2
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
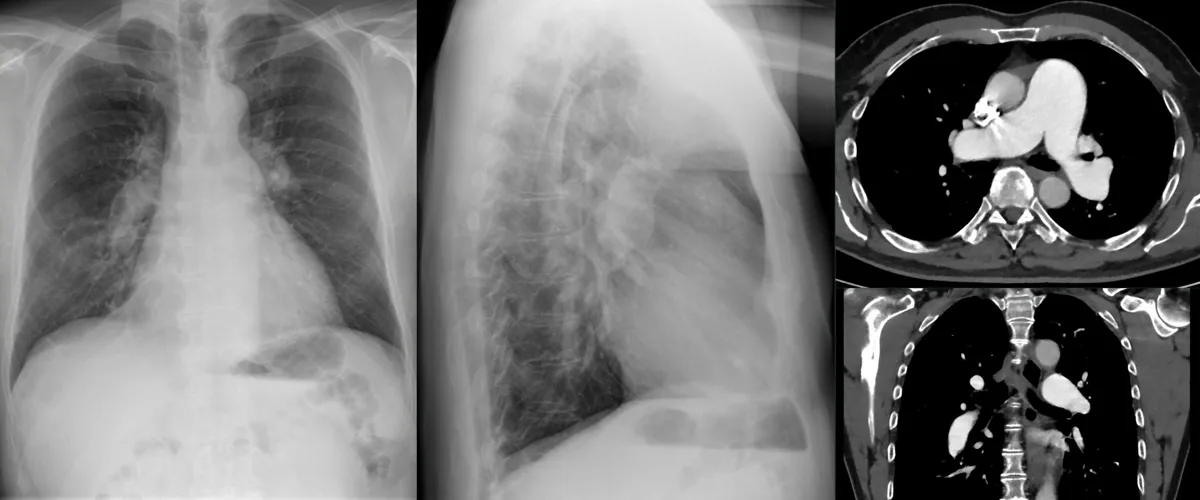 X-ray
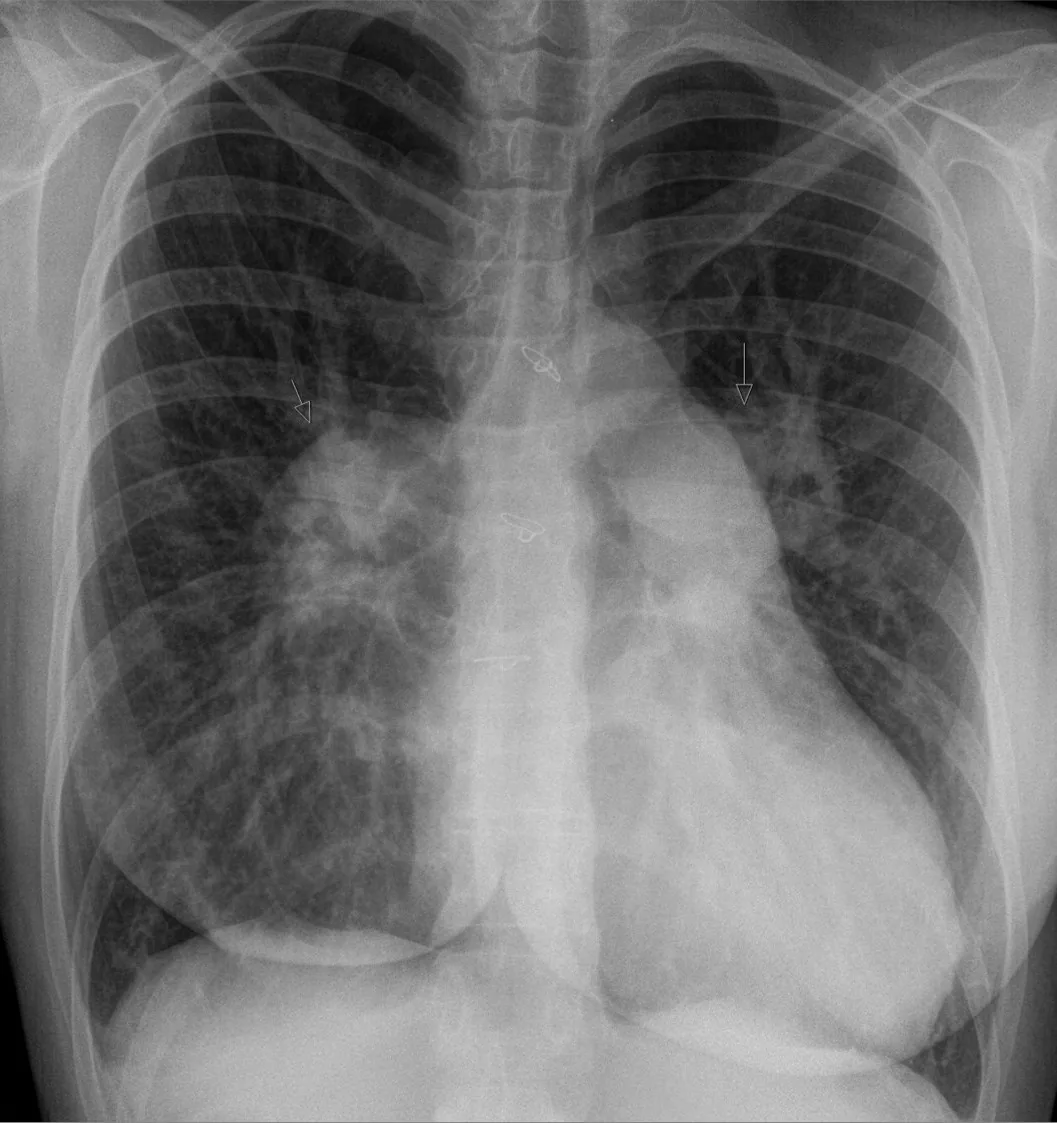 X-ray
Definition
Pulmonary hypertension (PH) is increased pressure in the pulmonary circulation. The pulmonary vessels may be constricted, pruned, lost or obstructed; severe PH leads to right ventricular overload and failure.
Hemodynamic definition
- Pulmonary hypertension: mean pulmonary arterial pressure (mPAP) above 20 mmHg at rest; the previous threshold was 25 mmHg or more.
- Precapillary PH: mPAP above 20 mmHg, pulmonary artery wedge pressure (PAWP) up to 15 mmHg and pulmonary vascular resistance (PVR) above 2 Wood units.
- Isolated postcapillary PH: mPAP above 20 mmHg, PAWP above 15 mmHg, PVR up to 2 Wood units, e.g. in left heart disease.
- Combined pre- and postcapillary PH: mPAP above 20 mmHg, PAWP above 15 mmHg and PVR above 2 Wood units.
Classification
Clinical classification (5 groups)
- Group 1 – pulmonary arterial hypertension (PAH): idiopathic, heritable (e.g. BMPR2), drug- and toxin-induced, associated with congenital heart disease, connective tissue diseases, HIV infection, portal hypertension or schistosomiasis; pulmonary veno-occlusive disease; persistent pulmonary hypertension of the newborn.
- Group 2 – PH due to left heart disease: diastolic dysfunction including heart failure with preserved ejection fraction, systolic dysfunction, valvular heart disease, inflow or outflow tract obstruction.
- Group 3 – PH due to lung disease and/or hypoxia: COPD, interstitial lung disease, sleep-disordered breathing, chronic exposure to high altitude.
- Group 4 – PH due to pulmonary artery obstruction: chronic thromboembolic pulmonary hypertension (CTEPH), non-thrombotic emboli (e.g. tumor, parasites).
- Group 5 – unclear or multifactorial mechanisms: hematological disorders (chronic hemolytic anemia, sickle cell disease, myeloproliferative disorders, splenectomy), sarcoidosis, metabolic disorders, chronic kidney disease, fibrosing mediastinitis.
Aetiopathogenesis
- Most common causes overall: left heart failure including diastolic dysfunction and parenchymal lung disease with hypoxia; others are sleep apnea, systemic rheumatic diseases and recurrent pulmonary embolism.
- Genetics: mutations in the BMPR2 gene cause about 75 % of heritable PAH (autosomal dominant with incomplete penetrance); other genes (e.g. ALK-1, CAV1, ENG, KCNK3, SMAD9, TBX4) are much less common.
- Triggering substances: certain appetite suppressants, amphetamines and methamphetamines and individual protein-kinase-blocking cancer drugs are definitely associated with PAH.
- Increased pulmonary vascular resistance: vasoconstriction (enhanced activity of thromboxane and endothelin-1, reduced activity of prostacyclin and nitric oxide), proliferation of endothelium and smooth muscle, inflammation and remodelling of the vessel wall, local activation of coagulation.
- Increased pulmonary venous pressure: in disorders of the left heart, most commonly heart failure with preserved ejection fraction.
- Increased pulmonary blood flow: in congenital shunt lesions such as atrial and ventricular septal defects or patent ductus arteriosus.
- Consequences: right ventricular hypertrophy, later dilatation and right heart failure with limited cardiac output on exertion.
Clinical features
- Progressive exertional dyspnea and easy fatigability in almost all patients.
- Atypical chest discomfort and light-headedness or presyncope on exertion indicate more severe disease.
- Signs of right heart failure in advanced disease: right ventricular heave, widely split second heart sound with an accentuated pulmonary component, pulmonary ejection click, right ventricular third heart sound, tricuspid regurgitation murmur, jugular venous distension.
- Liver congestion and peripheral edema as common late signs; lung auscultation is usually normal.
Diagnosis
- Chest X-ray: enlarged hilar vessels that rapidly prune into the periphery, right ventricle filling the anterior airspace on the lateral view.
- ECG: right axis deviation, R greater than S in V1, S1Q3T3 pattern (right ventricular hypertrophy), peaked P waves in II (right atrial dilatation).
- Transthoracic Doppler echocardiography: right ventricular function and systolic pulmonary artery pressure; detection of causative left heart disease.
- Search for the cause: pulmonary function tests with diffusing capacity, V/Q scintigraphy or CT angiography (thromboembolic disease), high-resolution CT, autoantibodies, polysomnography, HIV testing, liver tests, blood count.
- Right heart catheterisation: confirms the diagnosis and severity; a mean pulmonary arterial pressure above 20 mmHg, a pulmonary artery wedge pressure up to 15 mmHg and a pulmonary vascular resistance above 2 Wood units characterise PAH; right-sided oxygen saturations to exclude a left-to-right shunt.
- Severity: 6-minute walk distance and NT-proBNP or BNP; signs of right ventricular systolic dysfunction on echocardiography.
- Family history and genetic testing (e.g. BMPR2) in heritable or idiopathic PAH.
Treatment principles
- Treatment depends on the clinical group: in left heart and lung disease, treatment of the underlying condition comes first, and specific vasodilators are used there only exceptionally, for example an inhaled prostanoid in interstitial lung disease.
- In pulmonary arterial hypertension, endothelin receptor antagonists, PDE-5 inhibitors, guanylate cyclase stimulators and prostanoids are used in a risk-adapted way, often in combination.
- In chronic thromboembolic disease, pulmonary endarterectomy is the treatment of choice, otherwise balloon angioplasty or medical therapy; diuretics, oxygen and anticoagulation are added as appropriate.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.