Secondary hypertension
Board exam relevance: in 9 of more than 100 exam reports · rank 32- Synonyms
- secondary high blood pressure, Conn's syndrome, primary aldosteronism, pheochromocytoma, renal artery stenosis, renovascular hypertension, endocrine hypertension, coarctation of the aorta
- Specialty
- Internal medicine · Cardiology
- Images
- Angiography 1 · CT 1 · Gross specimen 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (3)
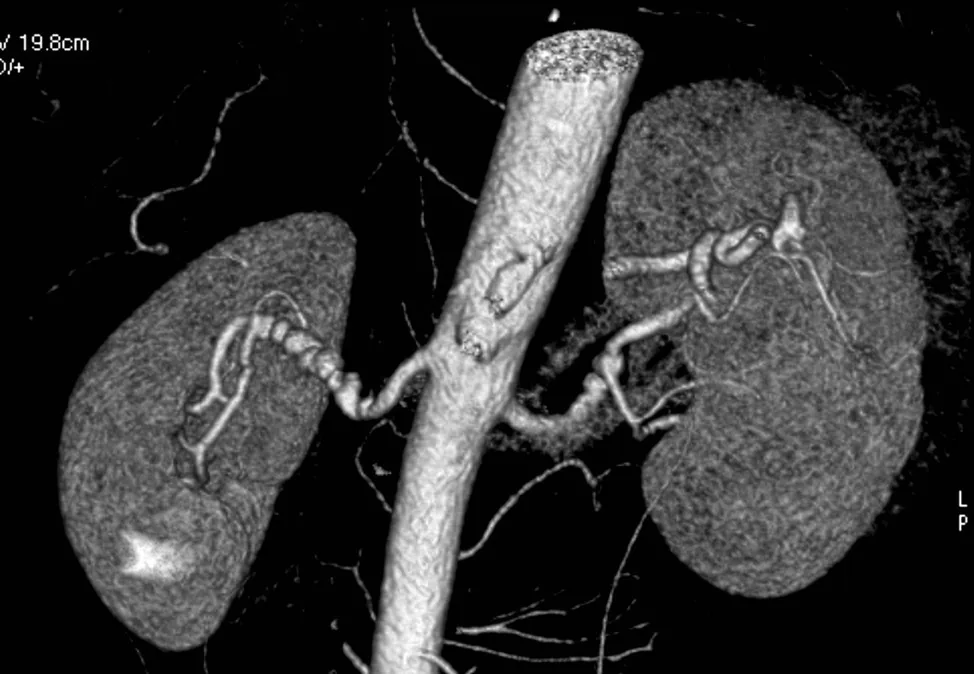 Angiography
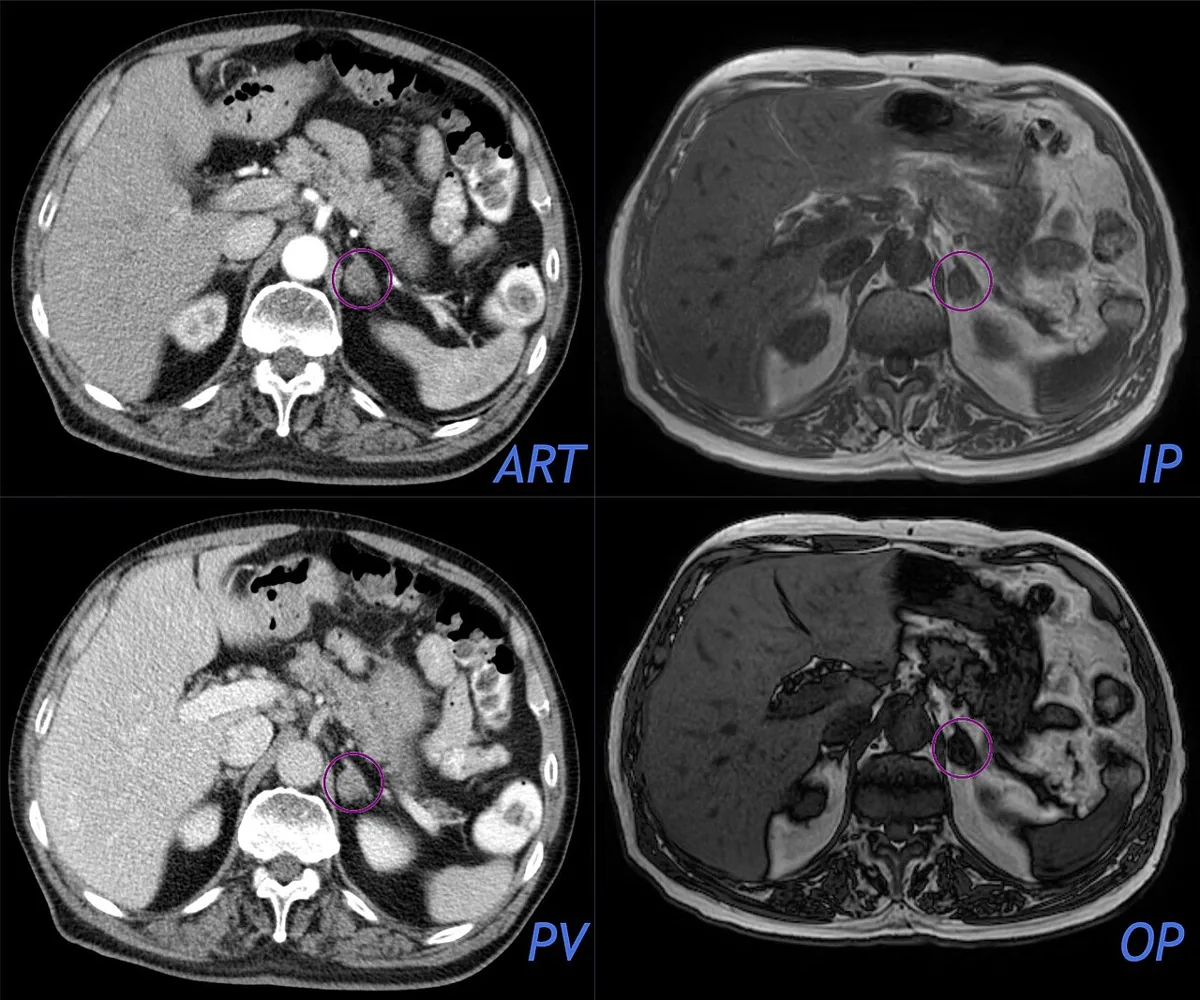 CT
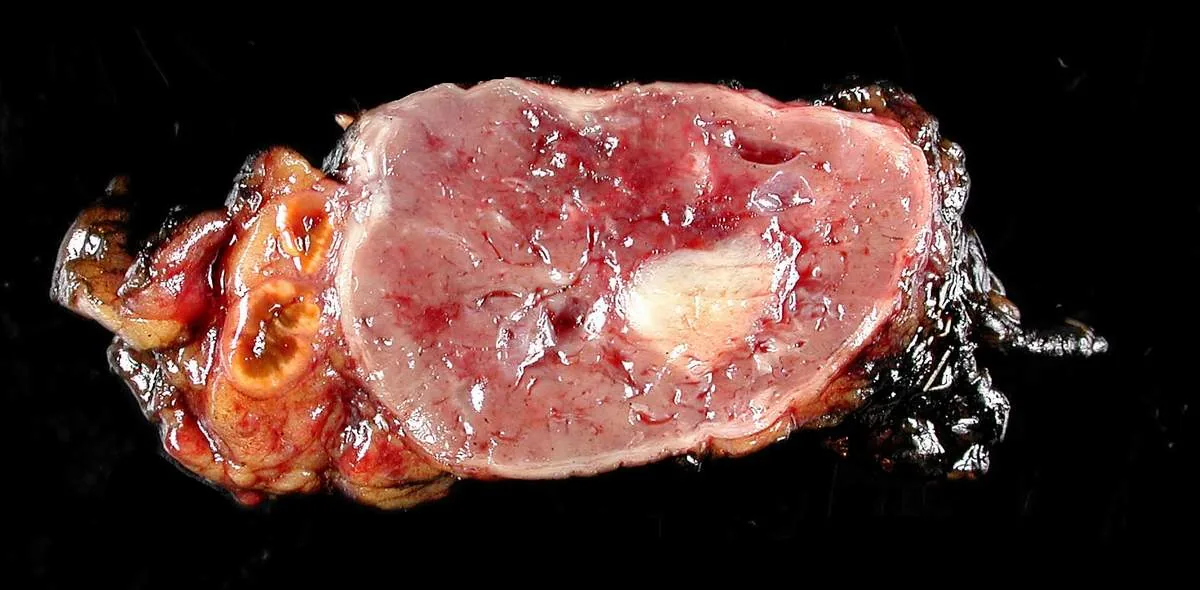 Gross specimen
Definition
In secondary hypertension, elevated blood pressure results from an identifiable underlying disease or external cause. It accounts for only a small proportion of all hypertension but is important because the cause can often be specifically identified. The most common cause is primary aldosteronism; other important causes are sleep apnea, chronic kidney disease and renal artery stenosis.
Classification
Groups of causes
- Sleep apnea: obstructive sleep apnea
- Renal parenchymal: chronic glomerulonephritis or pyelonephritis, polycystic kidney disease, lupus nephritis, obstructive uropathy
- Renovascular: renal artery stenosis
- Endocrine: primary aldosteronism; less commonly pheochromocytoma, Cushing syndrome, congenital adrenal hyperplasia, hyper- and hypothyroidism, primary hyperparathyroidism, acromegaly
- Exogenous causes: sympathomimetics (decongestants), NSAIDs, antipsychotics, certain cancer drugs, stimulants, cocaine; licorice may further raise blood pressure
- Vascular anomaly: coarctation of the aorta
Occurrence & epidemiology
In German claims data from 2018, secondary hypertension was coded in 0.9 % of hypertension diagnoses; the true frequency is likely higher because many causes remain unrecognized. Renal artery stenosis is one of the most common reversible causes but accounts for less than 1 % of all hypertension. A pheochromocytoma is present in about 0.2–0.6 % of people with hypertension.
Aetiopathogenesis
- Primary aldosteronism: autonomous aldosterone production by the adrenal cortex (adenoma, hyperplasia, rarely carcinoma); sodium and water retention increase blood volume and suppress renin release; potassium loss
- Renal artery stenosis: about 80 % atherosclerosis (especially men over 50, proximal segments), about 20 % fibromuscular dysplasia; reduced renal perfusion activates the renin-angiotensin system
- Pheochromocytoma: catecholamine-secreting tumor of chromaffin cells, usually in the adrenal gland
- Cushing syndrome: hyperfunction of the adrenal cortex, ACTH-dependent (e.g. pituitary tumor, Cushing disease) or ACTH-independent
Clinical features
Clinical clues
- Renal disease (clues according to the NVL): severe hypertension (180/110 mmHg or more), marked organ damage, onset before age 30, rapid worsening of known hypertension, loss of the nocturnal blood pressure dip, hematuria or proteinuria
- Aldosteronism: grade 2 hypertension (under 60 years) or grade 3, hypertension uncontrolled despite three antihypertensive drugs, spontaneous hypokalemia with episodic weakness, adrenal tumor, family history; increasingly diagnosed with normal potassium
- Pheochromocytoma: hypertension in most patients, paroxysmal in about 45 %; tachycardia, sweating, severe headache, palpitations, pallor, postural hypotension; in older people marked loss of weight with sustained hypertension
- Cushing syndrome: moon face, truncal obesity, skin atrophy, purple striae, ecchymoses, proximal myopathy
- Renal artery stenosis: abrupt onset or rapid worsening of hypertension within 6 months, unexplained deterioration of renal function, kidney size asymmetry above 1 cm, recurrent unexplained pulmonary edema; epigastric bruit in about half of cases with fibromuscular dysplasia
- Other: sleep apnea (loud snoring, breathing pauses, daytime sleepiness), hyperthyroidism (tachycardia, tremor, loss of weight), acromegaly (coarsened facial features, enlarged hands and feet), coarctation of the aorta (diminished or delayed femoral pulses, lower blood pressure in the legs)
Diagnosis
Targeted testing
- Basic tests: potassium, sodium, creatinine and eGFR, urinalysis (hematuria, proteinuria), TSH
- Primary aldosteronism: plasma aldosterone and renin activity; confirmation by a suppression test with salt loading; adrenal imaging; bilateral adrenal vein sampling to distinguish unilateral (tumor) from bilateral (hyperplasia) disease
- Pheochromocytoma: plasma free metanephrines (sensitivity up to 99 %) or urinary metanephrines; if positive, CT or MRI of chest and abdomen, possibly nuclear imaging
- Cushing syndrome: 24-hour urinary free cortisol, overnight suppression test, midnight serum or salivary cortisol; ACTH to distinguish ACTH-dependent from ACTH-independent disease
- Renal artery stenosis: duplex ultrasound, MR angiography or CT angiography; confirmation by renal angiography
- Other: sleep study if sleep apnea is suspected; echocardiography, CT or MRI if coarctation of the aorta is suspected
Treatment principles
- The priority is targeted treatment of the cause, such as adrenalectomy for unilateral aldosteronoma or phaeochromocytoma, revascularisation of selected renal artery stenoses or positive airway pressure for sleep apnoea.
- Bilateral hyperaldosteronism is treated with mineralocorticoid receptor antagonists; causative medications are withdrawn.
- Alongside, or if the cause cannot be removed, combination antihypertensive therapy with lifestyle measures and follow-up is used.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Sick sinus syndrome
- Syncope
- Takotsubo cardiomyopathy
- Ventricular tachycardia
- Atrial flutter
- Atrial septal defect and patent foramen ovale
- Wolff-Parkinson-White syndrome
- Acute pericarditis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.