Myocarditis
Board exam relevance: in 8 of more than 100 exam reports · rank 39- Synonyms
- inflammation of the heart muscle, perimyocarditis, myopericarditis, viral myocarditis, inflammatory cardiomyopathy
- Specialty
- Internal medicine · Cardiology
- Images
- MRI 1 · Histology 3
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (4)
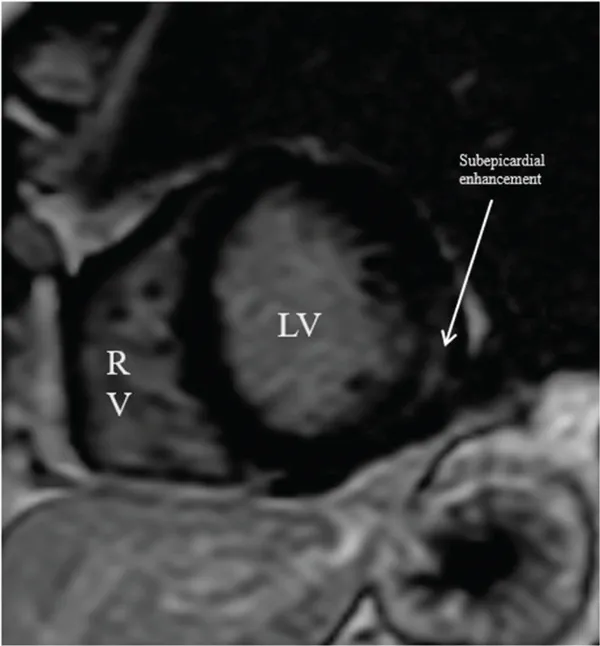 MRI
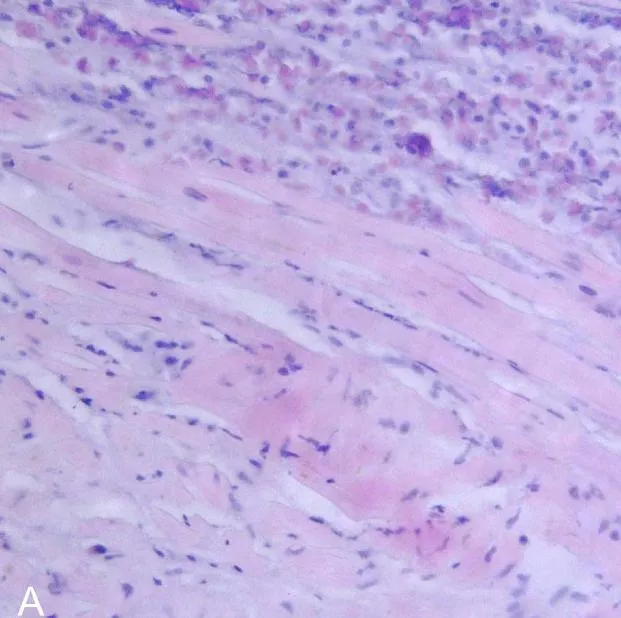 Histology
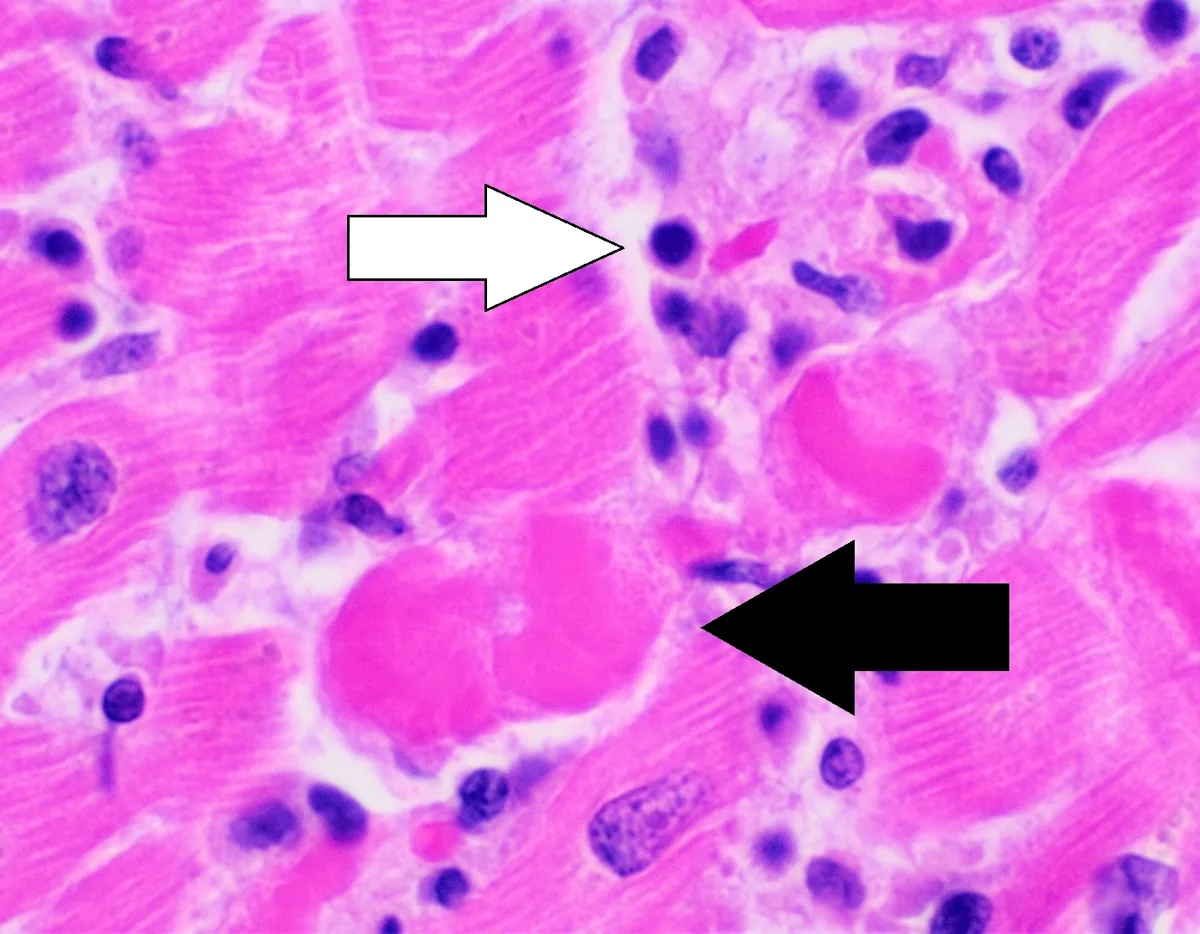 Histology
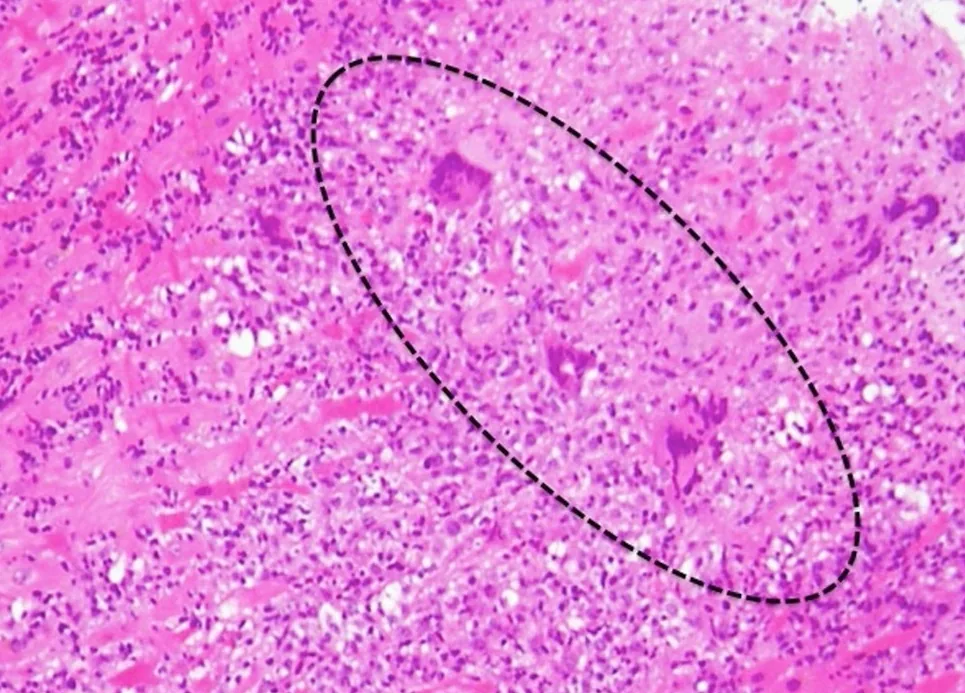 Histology
Definition
Myocarditis is inflammation of the heart muscle. It belongs to the spectrum of inflammatory myopericardial syndromes, which are distinguished by the predominant site of inflammation: pericarditis, myopericarditis (predominantly pericarditis with extension to the myocardium), perimyocarditis (predominantly myocarditis with extension to the pericardium) and myocarditis.
Classification
- By course: acute (typically a few days), subacute (weeks to months) and chronic (not resolved after a few months); there are no fixed time limits.
- Fulminant myocarditis: sudden, severe and life-threatening form with circulatory failure.
- Specific forms: giant cell myocarditis (rare, fulminant, with multinucleated giant cells on biopsy), eosinophilic myocarditis, drug-related hypersensitivity myocarditis, granulomatous myocarditis in sarcoidosis.
Aetiopathogenesis
- Viral (the most common infectious cause in North America and Western Europe): parvovirus B19 and human herpesvirus 6 (most often detected on biopsy), enteroviruses including coxsackie B virus, adenoviruses, Epstein-Barr virus, influenza viruses, coronaviruses including SARS-CoV-2, HIV.
- Other pathogens: bacteria (e.g. Borrelia burgdorferi, group A streptococci, staphylococci, tuberculosis), parasites (e.g. Chagas disease due to Trypanosoma cruzi, toxoplasmosis), fungi.
- Autoimmune and inflammatory: systemic lupus erythematosus, granulomatosis with polyangiitis, giant cell and Takayasu arteritis, idiopathic inflammatory myopathies, inflammatory bowel disease, sarcoidosis.
- Toxic causes: alcohol, cocaine; certain drugs (hypersensitivity myocarditis), including modern cancer drugs that activate the immune system, and anthracyclines; radiogenic.
- Genetic factors: variants in genes for inherited cardiomyopathies or arrhythmias may increase susceptibility.
Clinical features
- Frequently a preceding viral or respiratory infection, often 1–4 weeks before the onset of cardiac symptoms.
- Spectrum from minimal symptoms to fulminant heart failure and fatal arrhythmias; sudden cardiac death may be the first manifestation, possibly after palpitations or syncope.
- Signs of heart failure: fatigue, dyspnea, edema, crackles, raised jugular venous pressure, third or fourth heart sound, murmurs of mitral and tricuspid regurgitation; pulsus alternans in severe systolic dysfunction.
- With pericardial involvement pericarditic chest pain (aggravated by breathing and coughing, relieved by leaning forward) and a pericardial rub.
- Clues to the cause: fever and myalgia in infection, rash in hypersensitivity myocarditis, enlarged lymph nodes in sarcoidosis, fulminant course with arrhythmias in giant cell myocarditis.
- Progression to dilated cardiomyopathy is possible.
Histology
Endomyocardial biopsy is the gold standard: it shows an inflammatory infiltrate with necrosis of adjacent cardiomyocytes. Because of patchy involvement its sensitivity is low – a positive result confirms the diagnosis, a negative one does not exclude it. Characteristic findings are multinucleated giant cells in giant cell myocarditis and eosinophilic infiltrates in eosinophilic myocarditis.
Diagnosis
- Laboratory: cardiac troponin (high-sensitivity assays with a sensitivity of 64–100 % for acute myocarditis), full blood count; additional tests for the cause.
- ECG: normal or abnormal; frequently non-specific ST-T changes, sometimes infarct-like ST elevation; conduction delays, sinus tachycardia, ventricular tachycardia, ventricular fibrillation; AV block in Lyme carditis, giant cell myocarditis or sarcoidosis; low voltage with marked edema or dysfunction.
- Echocardiography: normal in early or mild cases; segmental wall motion abnormalities, dilatation and global systolic dysfunction, abnormal strain, frequently diastolic dysfunction.
- Cardiac MRI: often the decisive examination; typical late gadolinium enhancement subepicardial and mid-myocardial (in ischemia, by contrast, subendocardial), myocardial edema and hyperaemia. The diagnosis rests on the combined detection of edema and non-ischemic myocardial injury with T1- and T2-based techniques; signs of pericarditis or systolic dysfunction are supportive.
- Endomyocardial biopsy: a positive result confirms the diagnosis and can identify special forms such as giant cell or eosinophilic myocarditis; because of possible complications it is not a routine test.
Treatment principles
- General measures are abstinence from sport for at least one month, longer in individual cases, guideline-directed heart failure therapy in reduced ejection fraction and treatment of arrhythmias.
- Immunosuppression is reserved for specific biopsy-proven forms such as giant cell, eosinophilic or virus-negative autoimmune myocarditis, and infectious causes such as Lyme disease are treated specifically.
- In fulminant cases, mechanical circulatory support serves as a bridge, and a wearable cardioverter-defibrillator may be used temporarily in severely reduced ejection fraction.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Pericardial effusion and cardiac tamponade
- Pulmonary hypertension
- Rheumatic fever
- Bundle branch block (left and right)
- Secondary hypertension
- Sick sinus syndrome
- Syncope
- Takotsubo cardiomyopathy
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.