Monoclonal gammopathy of undetermined significance (MGUS)
Board exam relevance: in 2 of more than 100 exam reports · rank 142- Synonyms
- monoclonal gammopathy, paraproteinemia, M-spike, paraprotein
- Specialty
- Internal medicine · Haematology & oncology
- Images
- Clinical 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
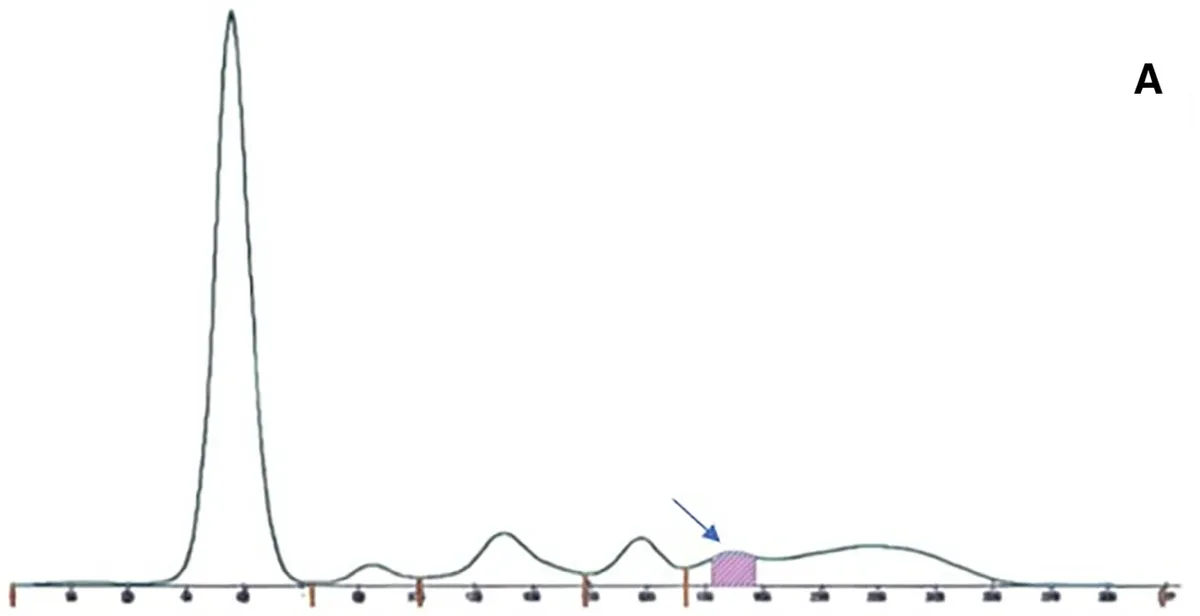
Definition
Monoclonal gammopathy of undetermined significance (MGUS) is an asymptomatic, premalignant clonal plasma cell disorder. An M-protein is detectable in serum or urine without multiple myeloma or a related lymphoplasmacytic neoplasm being present. MGUS is an obligatory precursor of multiple myeloma, Waldenström macroglobulinemia, and AL amyloidosis.
Classification
Diagnostic criteria (IMWG 2014):
- Serum M-protein < 3 g/dL
- clonal bone marrow plasma cells < 10 %
- no end-organ damage attributable to the plasma cell disorder (no CRAB features: hypercalcemia, renal insufficiency, anemia, bone lesions)
Subtypes by isotype:
- Non-IgM MGUS (IgG, IgA, rarely IgD): progression mainly to multiple myeloma
- IgM MGUS: progression mainly to lymphoplasmacytic lymphoma/Waldenström macroglobulinemia
- Light chain MGUS: abnormal free light chain ratio (< 0.26 or > 1.65) without heavy chain
Occurrence & epidemiology
Prevalence increases with age: about 3 % of people aged 50 and older and about 5 % of those aged 70 and older have MGUS; under age 40 it is rare (< 0.3 %). Men are affected more often than women, people of African ancestry two to three times more often. The risk of progression to a malignant disorder is about 1 % per year.
Aetiopathogenesis
A monoclonal plasma cell population emerges from a polyclonal background. About half of MGUS cases show aneuploidy, especially hyperdiploidy; translocations at the immunoglobulin heavy chain locus also occur. Autoimmune disorders and chronic immune stimulation are associated with an increased risk of MGUS. MGUS may also occur together with other diseases.
Clinical features
MGUS usually causes no symptoms and is discovered incidentally on protein electrophoresis. Peripheral neuropathy and increased bone loss with a higher fracture risk may occur. Warning signs of progression include marked fatigue, night sweats, fever, unintentional weight loss, bone pain, organomegaly, lymphadenopathy, bleeding tendency, unexplained anemia, hypercalcemia, or worsening kidney function.
Diagnosis
- Serum protein electrophoresis with immunofixation of serum and urine, quantitative immunoglobulins, and serum free light chains
- Complete blood count, calcium, and creatinine to exclude CRAB features
- Risk factors for progression: abnormal free light chain ratio, non-IgG isotype, and M-protein ≥ 1.5 g/dL; in addition, > 5 % clonal plasma cells and reduction of the uninvolved immunoglobulins
- Bone marrow examination and skeletal imaging at higher risk or with clinical or laboratory abnormalities; dispensable in IgG MGUS with M-protein < 1.5 g/dL and a normal free light chain ratio without warning signs
- With fracture risk, skeletal radiographs and bone densitometry
Treatment principles
- MGUS requires no treatment but risk-adapted monitoring of the paraprotein, free light chains, blood count, kidney function and calcium.
- It is important to distinguish it from multiple myeloma requiring treatment, Waldenström's macroglobulinaemia and AL amyloidosis, and new symptoms prompt reassessment.
- In monoclonal gammopathy of renal or other organ significance, therapy directed against the underlying clone is considered.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
- Monoclonal gammopathy of undetermined significance: evaluation, risk assessment, management, and beyond
- MSD Manual Professional: Monoclonal Gammopathy of Undetermined Significance (MGUS)
- An odyssey of monoclonal gammopathies: focusing on precursors and the progression from MGUS and SMM to multiple Myeloma, with a brief overview of novel therapeutic strategies
Cross-references
More topics: Haematology & oncology
- Anemia (classification and work-up)
- Hemolytic anemias
- Acute myeloid leukemia (AML)
- Iron deficiency anemia
- Waldenström macroglobulinemia
- Multiple myeloma
- Myelodysplastic syndromes (MDS)
- Non-Hodgkin lymphomas
- Superior vena cava syndrome
- Paraneoplastic syndromes
- Paroxysmal nocturnal hemoglobinuria (PNH)
- Polycythemia vera
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Anemia (classification and work-up) · Hemolytic anemias · Acute myeloid leukemia (AML)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.