Hepatitis D and hepatitis E
Board exam relevance: in 2 of more than 100 exam reports · rank 142- Synonyms
- HDV, HEV, delta hepatitis, delta agent, hep D, hep E
- Specialty
- Internal medicine · Liver & biliary tract
- Images
- Histology 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
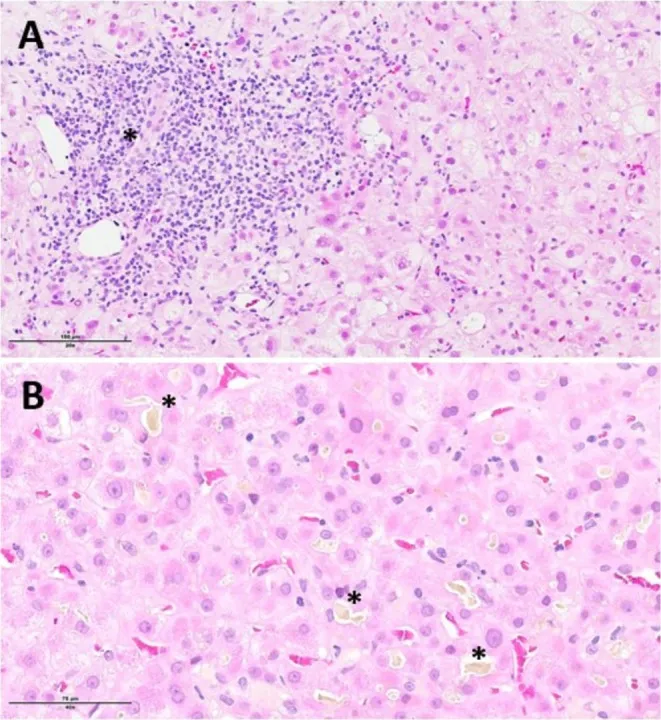 Histology
Definition
Hepatitis D is caused by hepatitis D virus (HDV, delta virus), a defective RNA virus. It can form infectious particles only by using the HBsAg-containing envelope of hepatitis B virus. Hepatitis D therefore always occurs together with hepatitis B.
Hepatitis E is caused by hepatitis E virus (HEV), a single-stranded RNA virus of the family Hepeviridae. Human disease is almost exclusively caused by genotypes 1 to 4.
Classification
- HDV co-infection: simultaneous infection with HBV and HDV in people without prior HBV infection; usually self-limiting
- HDV superinfection: infection with HDV in existing chronic hepatitis B; becomes chronic in more than 90%
- HEV genotypes 1 and 2: humans as the only reservoir, transmission via contaminated water in Asia and Africa
- HEV genotypes 3 and 4: zoonosis with domestic pigs and wild boar as the main reservoir; genotype 3 is endemic in Germany
Occurrence & epidemiology
Worldwide, more than 10 million people are infected with HDV. In the Mediterranean region HDV is endemic among HBV carriers; in Western Europe and North America it mainly affects people with blood exposure, for example through drug use. New infections are rare in Germany.
Antibodies against HEV are found in 15.3% of adults in Germany, ranging from about 5% under 30 years to 25% over 60 years. About three quarters of reported symptomatic cases affect people over 40, and about two thirds are men.
Aetiopathogenesis
HDV is transmitted like HBV via blood and body fluids: through shared needles, sexual intercourse and close personal contact.
In industrialised countries, HEV genotype 3 is mainly transmitted by eating undercooked pork or game and products made from them, less often via shellfish or blood products. Genotypes 1 and 2 are spread via fecally contaminated drinking water and food. The incubation period of hepatitis E is 15–64 days.
Clinical features
Hepatitis D
Co-infection presents as unusually severe acute hepatitis B, superinfection as an acute flare of known chronic hepatitis B. HDV co-infection causes the most severe form of chronic HBV infection: it leads more often and earlier to liver cirrhosis and hepatocellular carcinoma than HBV infection alone.
Hepatitis E
The HEV infection that occurs in Germany is mostly asymptomatic. Symptomatic cases are usually acute and self-limiting, often without jaundice, with mild gastrointestinal and general symptoms; however, jaundice, dark urine, pale stools and fever are also possible.
- Fulminant courses occur mainly with pre-existing liver disease or under immunosuppression; in pregnant women in the third trimester in genotype 1 areas, severe fulminant hepatitis has been described.
- Chronic hepatitis E (virus detectable for longer than 6 months) occurs in immunocompromised people, for example under immunosuppression or with advanced HIV infection, and can rapidly lead to cirrhosis.
- Neurological manifestations: neuralgic amyotrophy (often bilateral), Guillain-Barré syndrome and encephalitis or myelitis, often with only mildly raised liver values.
Diagnosis
- Hepatitis D: in every confirmed HBV infection, testing for anti-HDV; if positive, detection of HDV RNA (RT-PCR) proves active infection. With concurrent HDV infection, the HBV viral load can be very low.
- Hepatitis E: aminotransferases are typically raised more than ALP and GGT. IgM anti-HEV with compatible symptoms is usually diagnostic and detectable for about 3–6 months; otherwise IgG anti-HEV indicates past infection. HEV RNA (PCR) in blood or stool proves recent infection.
- Under immunosuppression, HEV serology is unreliable; here direct viral detection by PCR is decisive.
Treatment principles
- Hepatitis D occurs only together with hepatitis B and is treated in specialised centres with an entry inhibitor and/or immunomodulatory therapy, combined with nucleos(t)ide analogues against hepatitis B virus where indicated; hepatitis B vaccination also protects against hepatitis D.
- Hepatitis E is usually self-limiting in immunocompetent individuals and is treated symptomatically.
- In chronic hepatitis E during immunosuppression, the immunosuppression is reduced where possible, and antiviral therapy follows if the infection persists.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Liver & biliary tract
- Liver cirrhosis
- Primary biliary cholangitis (PBC)
- Autoimmune hepatitis
- Esophageal varices and portal hypertension
- Hepatorenal syndrome
- Hepatocellular carcinoma (HCC)
- Drug-induced liver injury (DILI)
- Gilbert's syndrome
- Wilson's disease
- Primary sclerosing cholangitis (PSC)
- Spontaneous bacterial peritonitis (SBP)
- Steatotic liver disease (fatty liver, MASLD)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Liver cirrhosis · Primary biliary cholangitis (PBC) · Autoimmune hepatitis
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.