Antiphospholipid syndrome
Board exam relevance: in 3 of 105 exam reports · rank 111- Synonyms
- APS, Hughes syndrome, antiphospholipid antibody syndrome, lupus anticoagulant syndrome, sticky blood syndrome
- Specialty
- Internal medicine · Haematology & oncology
- Images
- Clinical 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
Antiphospholipid syndrome (APS) is an acquired autoimmune disorder with venous, arterial or microvascular thrombosis and/or pregnancy complications in the presence of persistently detectable antibodies against phospholipid-bound proteins (mainly β2-glycoprotein I, also prothrombin and annexin A5).
Primary APS without an associated autoimmune disease is distinguished from secondary APS, most often in systemic lupus erythematosus. Lupus anticoagulant is so named because it was first found in patients with lupus – but it also occurs without lupus and in the body does not inhibit clotting but promotes thrombosis.
Classification
Classification criteria
Revised Sapporo criteria (Sydney 2006): at least one clinical and one laboratory criterion.
- Clinical: unexplained vascular thrombosis (arterial, venous or small-vessel) or specific pregnancy morbidity: unexplained death of a morphologically normal fetus from 10 weeks of gestation, three or more consecutive unexplained spontaneous abortions before 10 weeks, or preterm birth of a morphologically normal neonate before 34 weeks due to eclampsia, severe pre-eclampsia or placental insufficiency
- Laboratory: lupus anticoagulant, anticardiolipin antibodies (IgG/IgM) at medium or high titre or anti-β2-glycoprotein I antibodies (IgG/IgM) above the 99th percentile, each on at least two occasions at least 12 weeks apart
ACR/EULAR criteria 2023: weighted points system; APS is classified with at least 3 points from clinical and at least 3 points from laboratory domains. Antibody titres are graded as moderate (40–79 units) or high (80 units or more); isolated IgM positivity carries only a low weight.
Catastrophic APS (CAPS): a rare form with widespread small-vessel thrombosis and failure of at least three organs.
Occurrence & epidemiology
Population-based studies estimate an incidence of about 1–2 per 100,000 inhabitants per year and a prevalence of about 40–50 per 100,000. Women are more often affected; in UK data the incidence peak was between 35 and 39 years in women and between 55 and 59 years in men. Antiphospholipid antibodies are found in about 6–9 % of women with pregnancy complications and in about 9–10 % of people with arterial events or venous thromboembolism.
Aetiopathogenesis
The exact mechanism of thrombosis is not fully understood. β2-glycoprotein I binds to phospholipid-rich surfaces; antibodies against it increase the expression of adhesion molecules (e.g. E-selectin) and tissue factor on endothelial cells and monocytes and reduce TFPI, an endogenous protein that dampens the tissue factor pathway. In addition, neutrophils, monocytes, platelets and the complement system are activated. Together this creates a prothrombotic state.
Clinical features
- Venous thrombosis: deep vein thrombosis, pulmonary embolism, also at unusual sites
- Arterial thrombosis: stroke, transient ischemic attack, myocardial infarction, peripheral arterial occlusion
- Pregnancy complications: recurrent miscarriage, late fetal death, severe pre-eclampsia, placental insufficiency
- Hematological: thrombocytopenia, hemolytic anemia
- Thrombotic microangiopathy with renal or neurological dysfunction
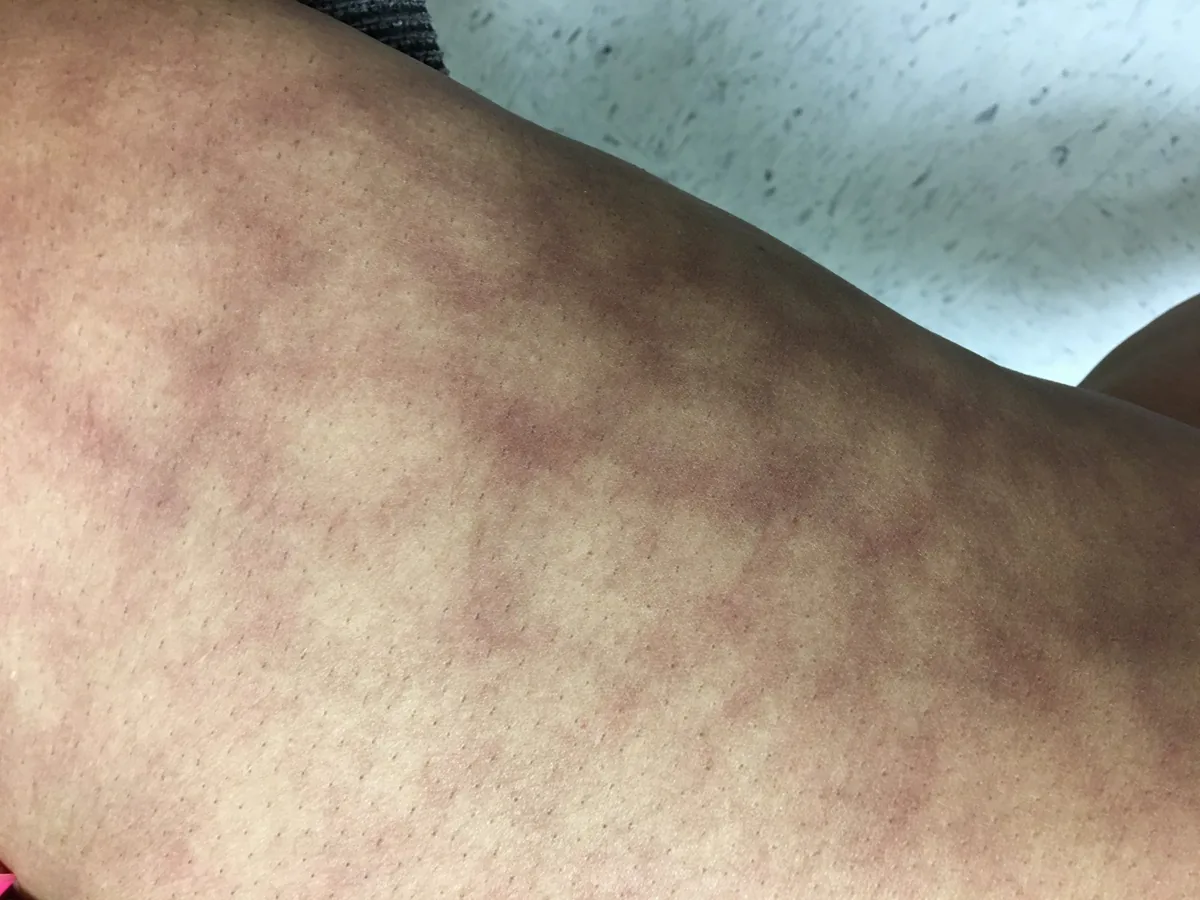
- Other (“non-criteria”) manifestations: livedo reticularis, heart valve disease, APS nephropathy, cognitive impairment
- Catastrophic APS: acute kidney injury, encephalopathy, adrenal hemorrhage due to thrombosis, skin necrosis, diffuse alveolar hemorrhage
Diagnosis
- Antibody testing with compatible clinical events: lupus anticoagulant, anticardiolipin antibodies IgG/IgM and anti-β2-glycoprotein I antibodies IgG/IgM; positive results are confirmed after at least 12 weeks
- Lupus anticoagulant: prolongs phospholipid-dependent clotting tests (aPTT, and more sensitively the dilute Russell viper venom time, dRVVT); the prolongation does not correct in a mixing study with normal plasma but does after adding excess phospholipids
- Blood count: thrombocytopenia; with hemolysis hemolysis markers and Coombs test
- Search for associated diseases, especially systemic lupus erythematosus (ANA, anti-dsDNA, complement)
- Imaging according to the site of thrombosis (compression ultrasound, CT angiography, brain MRI)
- CAPS: distinction from DIC, heparin-induced thrombocytopenia and thrombotic microangiopathy
Keep learning in the app
Further reading (open access)
- MSD Manual Professional: Antiphospholipid Syndrome (APS)
- Curr Rheumatol Rep 2022 (PMC8727975): Epidemiology of Antiphospholipid Syndrome in the General Population
- Rheumatology (Oxford) 2025 (PMC12212896): Insights into the 2023 ACR/EULAR antiphospholipid syndrome classification criteria
- J Clin Med (2025): Antiphospholipid Syndrome – A Comprehensive Clinical Review
Cross-references
More topics: Haematology & oncology
- Anemia (classification and work-up)
- Hemolytic anemias
- Acute myeloid leukemia (AML)
- Iron deficiency anemia
- Non-Hodgkin lymphomas
- Vitamin B12 deficiency and pernicious anemia
- Multiple myeloma
- Paraneoplastic syndromes
- Autoimmune hemolytic anemia (AIHA)
- Febrile neutropenia
- Immune thrombocytopenia (ITP)
- Renal anemia
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.