Takotsubo cardiomyopathy
Board exam relevance: in 2 of more than 100 exam reports · rank 142- Synonyms
- broken heart syndrome, stress cardiomyopathy, takotsubo syndrome, apical ballooning syndrome
- Specialty
- Internal medicine · Cardiology
- Images
- Angiography 2
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
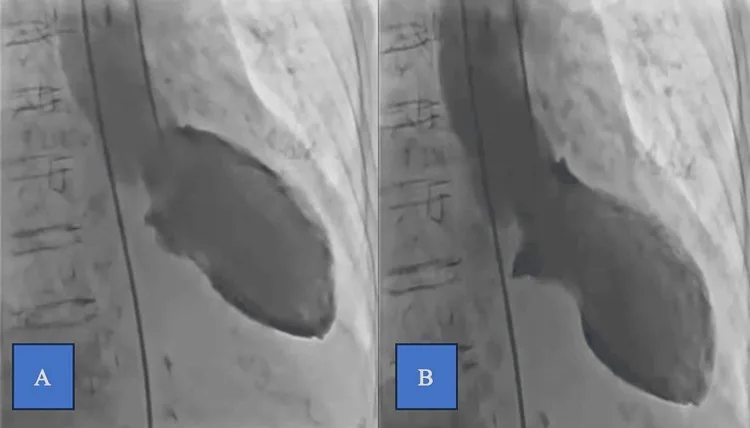 Angiography
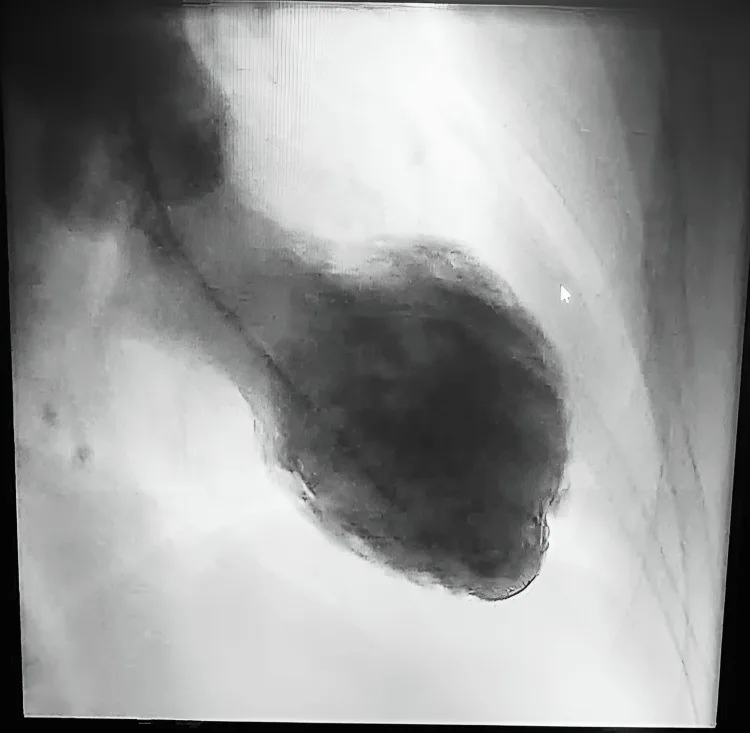 Angiography
Definition
Takotsubo syndrome (takotsubo cardiomyopathy, stress cardiomyopathy, "broken heart syndrome", apical ballooning syndrome) is a transient dysfunction of the left ventricle that clinically resembles acute myocardial infarction. The name comes from the Japanese cardiologists who first described it: the shape of the left ventricle at end-systole – narrow neck, ballooned apex – resembles a Japanese octopus trap.
Classification
Types by wall motion pattern
- Apical type (typical form, apical ballooning): in the majority of cases.
- Atypical types: midventricular, basal and focal.
- Further variants: biventricular, isolated right ventricular, global; right ventricular involvement is present in about one third of patients.
Occurrence & epidemiology
Takotsubo syndrome is estimated to represent about 1–3 % of all and 5–6 % of female patients presenting with suspected ST-elevation myocardial infarction. About 90 % of patients are women with a mean age of 67–70 years; around 80 % are older than 50. Women over 55 have about a five-fold greater risk than younger women and a ten-fold greater risk than men. Men are affected more often after physical triggers.
Aetiopathogenesis
- Sympathetic stimulation: regarded as the central mechanism. Usually an emotional or physical trigger precedes the event; the condition is associated with states of stress hormone excess such as phaeochromocytoma and with disorders of the central nervous system.
- Neurological triggers: subarachnoid hemorrhage, stroke or TIA, seizures.
- Hormonal factors: the marked predominance of postmenopausal women suggests a role for declining estrogen levels, which may increase susceptibility.
Clinical features
The most common symptoms are acute chest pain, dyspnea or syncope – at first glance indistinguishable from acute myocardial infarction. With physical triggers the underlying illness may dominate the picture; after emotional stress chest pain and palpitations are more frequent. Some patients present only with complications such as heart failure, pulmonary edema, stroke, cardiogenic shock or cardiac arrest.
ECG and biomarkers
- Initial ECG: ST elevation mainly in V2–V5 and in II and aVR; in anterior myocardial infarction it is centered on V1–V4, I and aVL instead.
- ECG evolution: T-wave inversion and QT prolongation increase over several days and resolve gradually over days to weeks.
- Troponin: at presentation elevated to a similar degree as in acute coronary syndrome, but peak values remain substantially lower; the extent of wall motion abnormality usually far exceeds the rise in biomarkers.
- BNP and NT-proBNP: frequently markedly elevated.
Complications
- Acute: LV thrombus, cardiogenic shock, dynamic LVOT obstruction, mitral regurgitation, ventricular arrhythmias.
Diagnosis
InterTAK diagnostic criteria
- Transient left ventricular dysfunction (hypokinesia, akinesia or dyskinesia) presenting as apical ballooning or midventricular, basal or focal wall motion abnormality; right ventricular involvement is possible. The abnormality usually extends beyond a single coronary artery territory.
- An emotional, physical or combined trigger can precede the event but is not obligatory.
- Neurological disorders and phaeochromocytoma can serve as triggers.
- New ECG abnormalities (ST elevation, ST depression, T-wave inversion, QTc prolongation); rarely they are absent.
- Cardiac biomarkers (troponin, CK) moderately raised in most cases; marked elevation of BNP is common.
- Significant coronary artery disease does not contradict the diagnosis.
- No evidence of infectious myocarditis.
- Postmenopausal women are predominantly affected.
Imaging
- Coronary angiography with left ventriculography: regarded as the gold standard to confirm or exclude takotsubo syndrome; coexisting coronary artery disease is reported in 10–29 %.
- Cardiac MRI: to exclude infectious myocarditis and to confirm the diagnosis; typical is myocardial edema rather than late gadolinium enhancement, particularly important in focal forms within a single coronary territory.
- Course of wall motion: the dysfunction usually recovers but may persist for longer.
Treatment principles
- Until an acute coronary syndrome has been excluded, management is as for myocardial infarction; thereafter treatment is supportive.
- In heart failure, standard heart failure medication is used; in left ventricular outflow tract obstruction, positive inotropes must be avoided, whereas beta-blockers and cautious fluid administration are appropriate.
- Left ventricular thrombus or severely reduced systolic function warrants anticoagulation until recovery, monitored by echocardiography.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Ventricular tachycardia
- Atrial flutter
- Atrial septal defect and patent foramen ovale
- Wolff-Parkinson-White syndrome
- Acute pericarditis
- Aortic regurgitation
- Aortic valve stenosis
- Arrhythmogenic right ventricular cardiomyopathy (ARVC)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.