Long QT syndrome and torsades de pointes
Board exam relevance: in 8 of more than 100 exam reports · rank 39- Synonyms
- LQTS, long QT, prolonged QT interval, torsades, TdP, Romano-Ward syndrome, channelopathy
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 3
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (3)
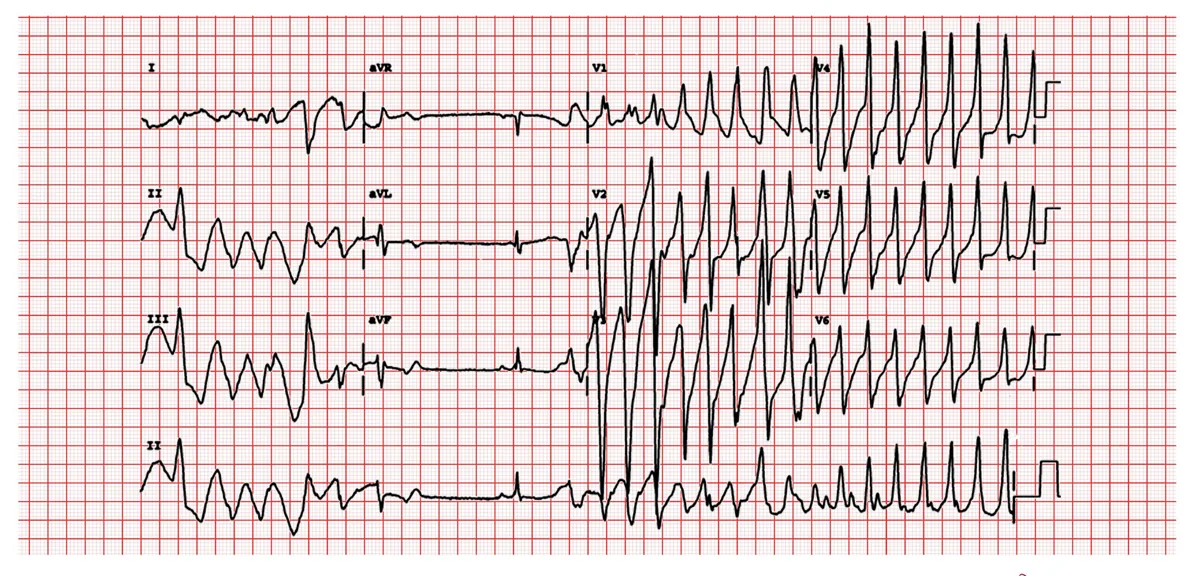 ECG
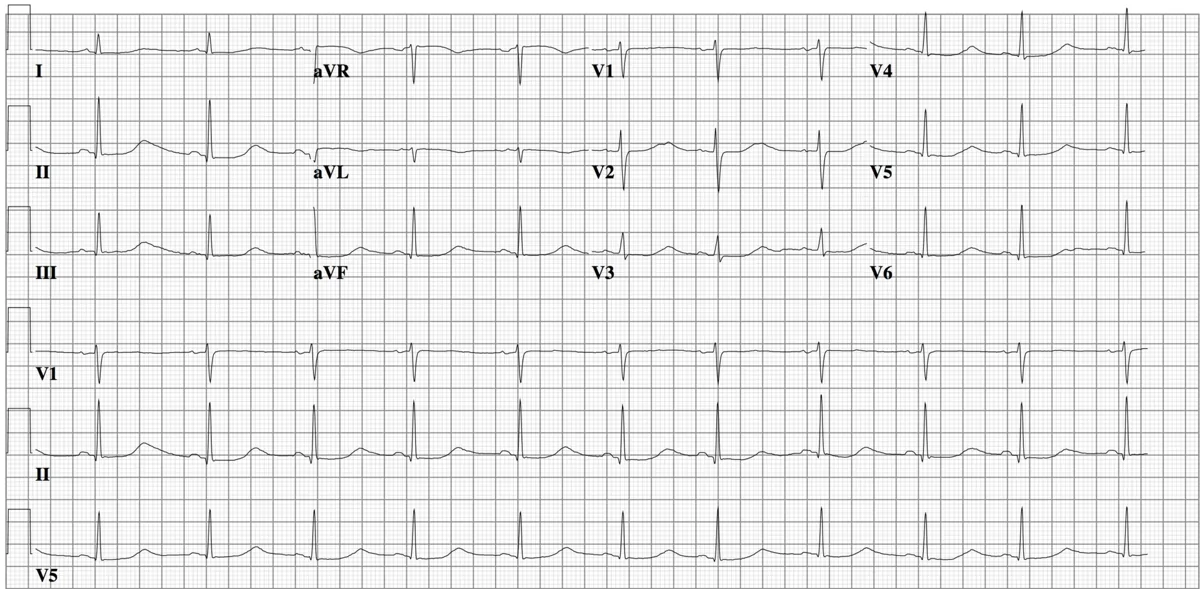 ECG
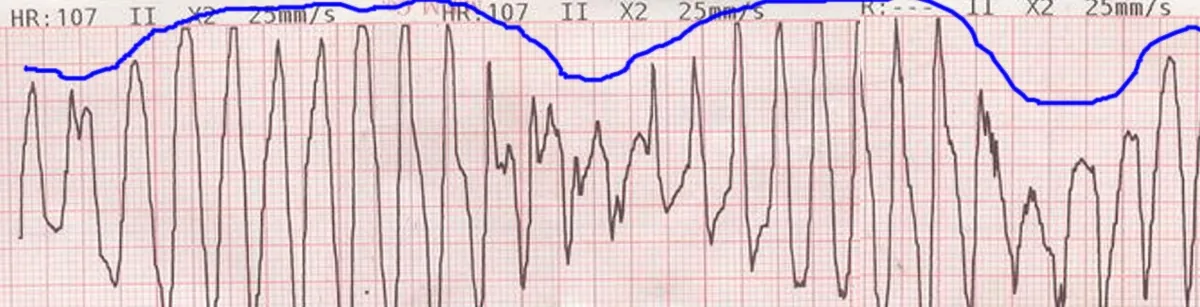 ECG
Definition
The long QT syndromes (LQTS) result from congenital or acquired disorders of cardiac ion channels that prolong the ventricular myocyte action potential, reflected on the ECG as a prolonged rate-corrected QT interval (QTc). Affected people are at risk of torsades de pointes, a polymorphic ventricular tachycardia with rapid, irregular QRS complexes that appear to twist around the baseline. It may stop spontaneously or degenerate into ventricular fibrillation.
Classification
Congenital forms
- LQTS type 1: loss of function of KCNQ1 (slow outward potassium current IKs), about 40–55 % of gene-positive cases; triggers are physical exertion, particularly swimming, or emotional stress
- LQTS type 2: loss of function of KCNH2/hERG (rapid outward potassium current IKr), about 30–45 %; triggers are sudden loud noises such as an alarm clock
- LQTS type 3: gain of function of SCN5A (inward sodium current INa), about 5–10 %; events at rest or during sleep
- Rare syndromic forms: Jervell and Lange-Nielsen syndrome (with congenital sensorineural deafness), Andersen-Tawil syndrome, Timothy syndrome
Occurrence & epidemiology
Congenital LQTS affects at least 1 in 2,000 people and is the most common cardiac channelopathy. It accounts for about 15–20 % of cardiac arrests that remain unexplained after ECG, echocardiography and exclusion of coronary artery disease.
Aetiopathogenesis
The congenital forms are mostly inherited in an autosomal dominant pattern with incomplete penetrance; more than 15 types have been described, but a mutation is found in only 70–85 %. Prolonged repolarization promotes early afterdepolarizations and spatial dispersion of refractoriness, from which torsades de pointes arises. The risk increases with the degree of QT prolongation, particularly above 0.50 s.
Acquired QT prolongation: the most common trigger is a QT-prolonging drug (certain antiarrhythmics, tricyclic antidepressants, phenothiazines, some antiviral agents and agents against fungal infections). Other predisposing factors: female sex, older age, hypokalemia, hypomagnesemia, hypothyroidism, slow or irregular ventricular rate, acute brain injury (hemorrhage, stroke, trauma), eating disorders, organophosphate poisoning and structural heart disease. Usually several factors coincide.
Clinical features
LQTS remains asymptomatic without torsades de pointes. Torsades cause palpitations, near-syncope, syncope or sudden death; the rate is 200–250/min and therefore often causes syncope. Myoclonic jerks during syncope occasionally lead to a misdiagnosis of epilepsy. Because the QT interval shortens with increasing rate, torsades often terminate spontaneously. In fetuses or newborns, bradycardia or 2:1 AV block may be the first sign.
Diagnosis
- Normal QTc values in adults: below 0.43 s in men and below 0.45 s in women; values above 0.44–0.45 s in men and above 0.46–0.47 s in women are considered prolonged. The Bazett formula is widely used but overestimates QTc at faster heart rates.
- Confirming the diagnosis: resting QTc of at least 0.46 s plus documented torsades de pointes or stress-induced syncope or cardiac arrest without another cause of QT prolongation
- Modified Schwartz score: clinical, ECG and exercise criteria; probability low (score of 1 or less), intermediate (1.5–3) or high (3.5 or more)
- T-wave morphology: broad T waves in type 1, low-amplitude notched T waves in type 2, long ST segment with normal-appearing T wave in type 3 (not specific)
- A normal QTc does not exclude LQTS (normal in 25–50 % of mutation carriers); exercise testing and ambulatory ECG reveal repolarization abnormalities that appear only during or after exercise.
- Genetic testing and evaluation of relatives; in acquired forms drug history and potassium, magnesium and thyroid function tests.
Treatment principles
- In torsade de pointes, QT-prolonging drugs are stopped, magnesium is given intravenously and potassium is corrected; if needed, the heart rate is increased by pacing, and defibrillation is performed if the patient is unstable.
- In congenital long QT syndrome, beta blockers are the basic therapy, and QT-prolonging drugs are strictly avoided.
- After survived cardiac arrest or at high risk, an ICD is implanted, and left cardiac sympathetic denervation is an additional option; genetic testing and family screening are part of care.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Mechanical complications of myocardial infarction
- Mitral regurgitation
- Mitral stenosis
- Myocarditis
- Pericardial effusion and cardiac tamponade
- Pulmonary hypertension
- Rheumatic fever
- Bundle branch block (left and right)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.