Ventricular tachycardia
Board exam relevance: in 8 of more than 100 exam reports · rank 39- Synonyms
- VT, V-tach, wide complex tachycardia, nonsustained VT, sustained VT
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 3
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (3)
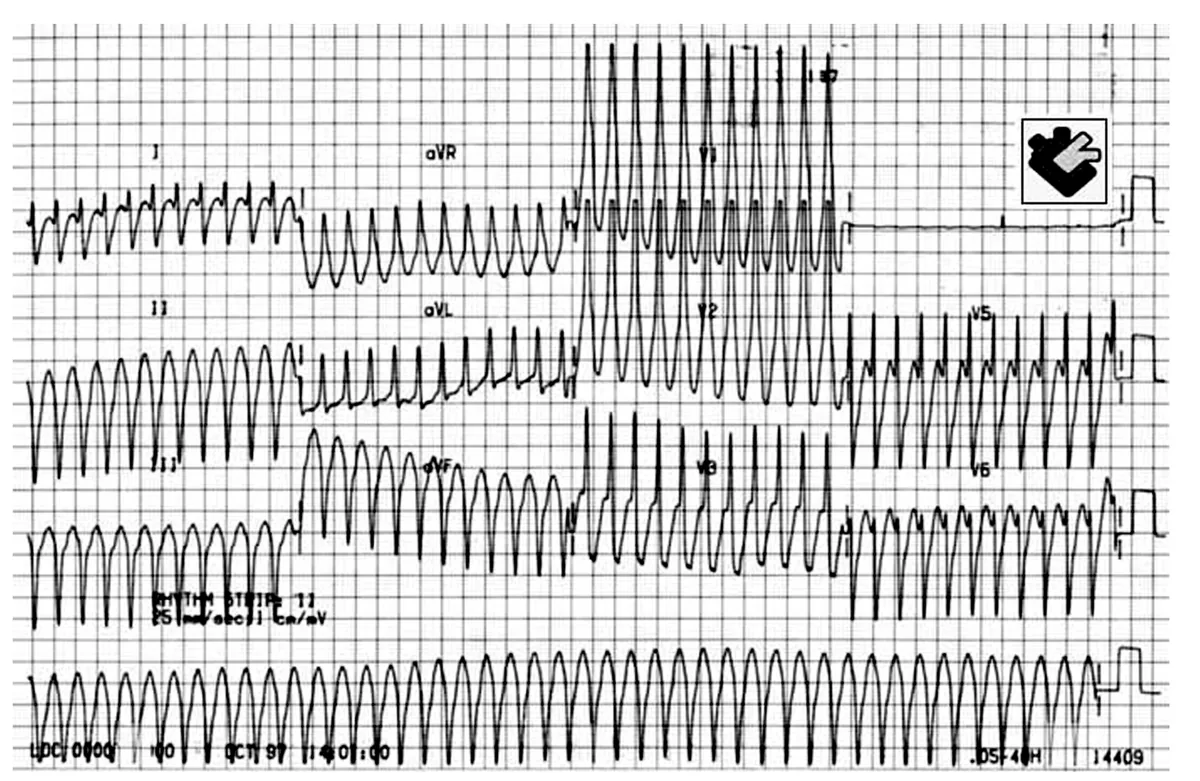 ECG
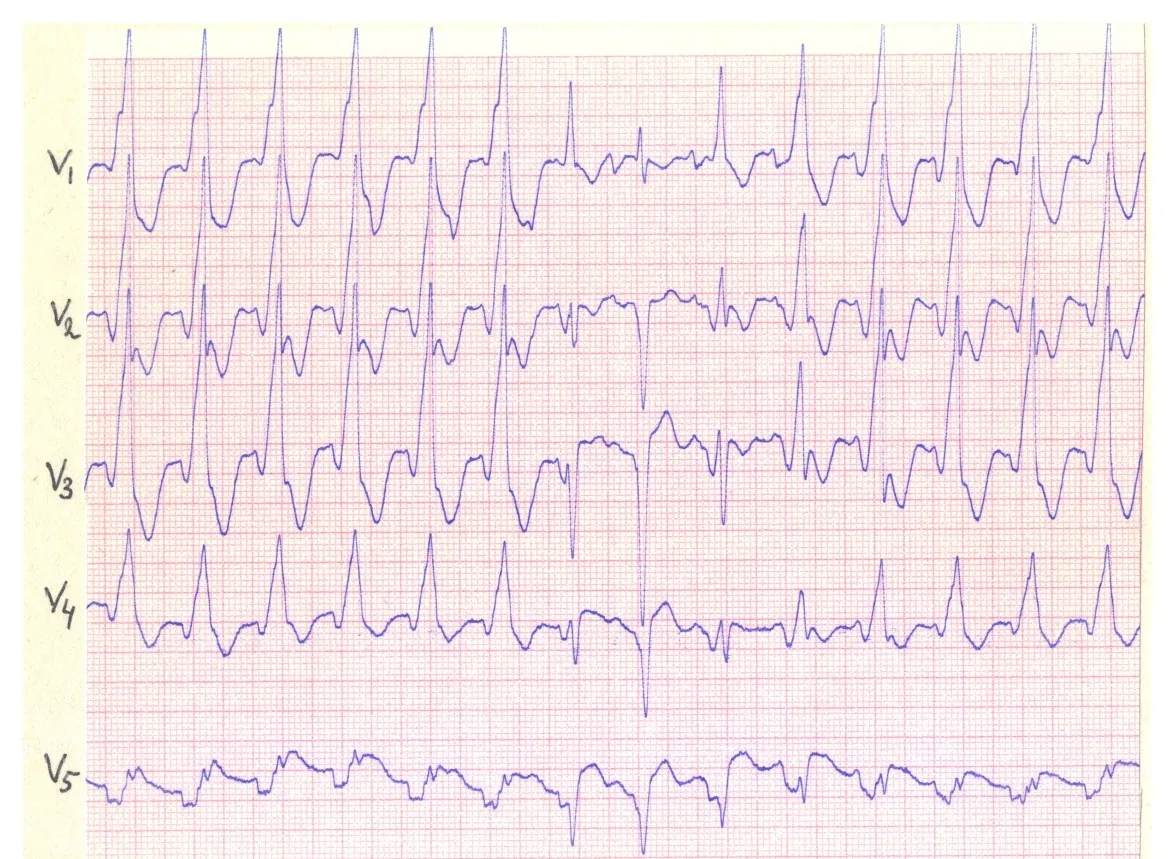 ECG
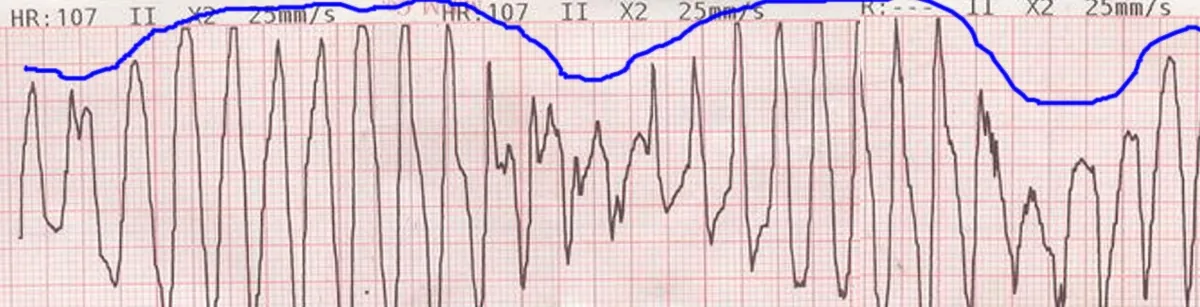 ECG
Definition
Ventricular tachycardia (VT) consists of at least three consecutive ventricular beats at a rate of at least 120/min; some experts use a cut-off of 100/min. Slower repetitive ventricular rhythms are called accelerated idioventricular rhythm and are usually benign. VT may deteriorate into ventricular fibrillation.
Classification
- Monomorphic: a single focus or reentrant pathway, regular, identical-appearing QRS complexes
- Polymorphic: several foci or pathways, irregular, varying QRS complexes; a special form is torsades de pointes with a prolonged QT interval
- Nonsustained: duration under 30 seconds
- Sustained: duration of 30 seconds or more, or terminated earlier because of hemodynamic collapse
- Idiopathic VT without structural heart disease: outflow tract VT from the right or left ventricle (usually with exercise or emotional stress, left bundle branch block-like morphology with an inferior axis) and left fascicular VT (right bundle branch block-like morphology with left axis deviation)
- Bundle branch reentry VT: macro-reentry via the bundle branches in advanced cardiomyopathy or conduction system disease
Aetiopathogenesis
Most affected people have significant heart disease, especially prior myocardial infarction (scar reentry) or a cardiomyopathy. Contributing factors are electrolyte disorders (particularly hypokalemia and hypomagnesemia), acidemia, hypoxemia and adverse drug effects. Congenital or acquired long QT syndrome is associated with torsades de pointes; catecholaminergic polymorphic VT (CPVT) is a genetic disorder of intracellular calcium regulation with arrhythmias particularly during adrenergic activation.
Clinical features
Brief or slow VT may be asymptomatic. Sustained VT is almost always symptomatic: palpitations, light-headedness, chest pain, dyspnea, hypotension and syncope up to circulatory arrest and sudden cardiac death. Some patients tolerate VT surprisingly well; good tolerance therefore does not argue against VT.
Diagnosis
ECG
- Any wide QRS complex tachycardia (QRS at least 0.12 s) is considered VT until proven otherwise.
- Findings supporting VT: dissociated P waves (AV dissociation), fusion beats, capture beats (normally conducted sinus beats interrupting the tachycardia), concordance of QRS complexes in the precordial leads and a frontal axis in the "northwest" quadrant.
- Brugada criteria (modified): additional morphological criteria in V1 and V6 depending on right or left bundle branch block-like QRS morphology.
Search for the cause
- Resting ECG after the episode: infarct scar, QT interval, Brugada pattern, pre-excitation
- Laboratory tests: potassium, magnesium, blood gases (acidemia, hypoxemia), troponin
- Imaging and search for the cause: echocardiography, cardiac MRI (scar, cardiomyopathy), coronary angiography; electrophysiological study to clarify the mechanism
Treatment principles
- Pulseless ventricular tachycardia is defibrillated immediately and managed according to the resuscitation algorithm; haemodynamically unstable tachycardia with a pulse receives synchronised cardioversion.
- Stable tachycardia is terminated with antiarrhythmic drugs or electrically; reversible causes such as ischaemia and electrolyte disturbances are sought and treated.
- Depending on risk, prevention relies on an implantable cardioverter-defibrillator, beta-blockers, antiarrhythmic drugs and catheter ablation, particularly after repeated shocks.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Atrial flutter
- Atrial septal defect and patent foramen ovale
- Wolff-Parkinson-White syndrome
- Acute pericarditis
- Aortic regurgitation
- Aortic valve stenosis
- Arrhythmogenic right ventricular cardiomyopathy (ARVC)
- Atrioventricular block
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.