Syncope
Board exam relevance: in 6 of more than 100 exam reports · rank 59- Synonyms
- fainting, faint, passing out, blackout, vasovagal syncope
- Specialty
- Internal medicine · Cardiology
- Images
- ECG 3 · Clinical 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (4)
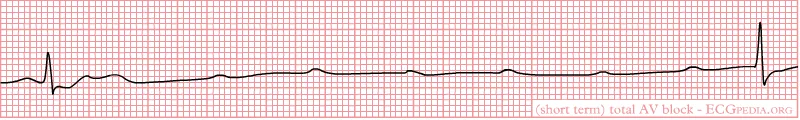 ECG
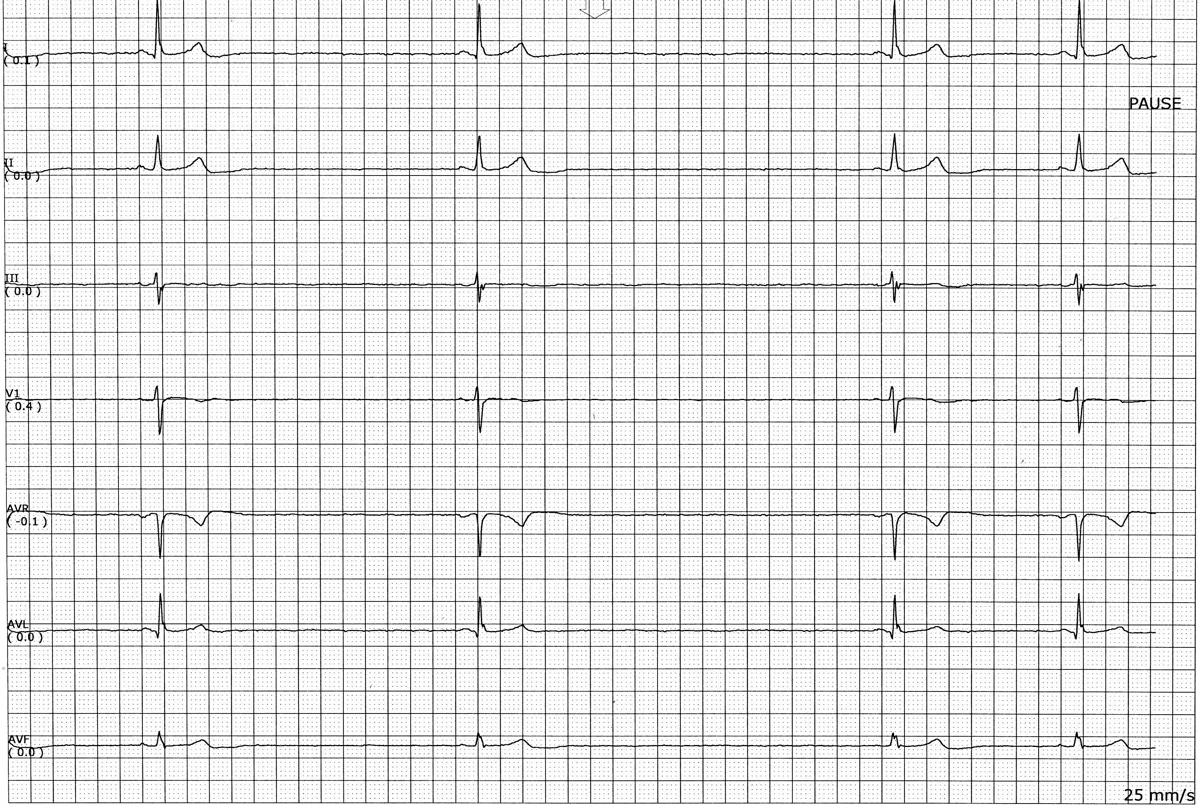 ECG
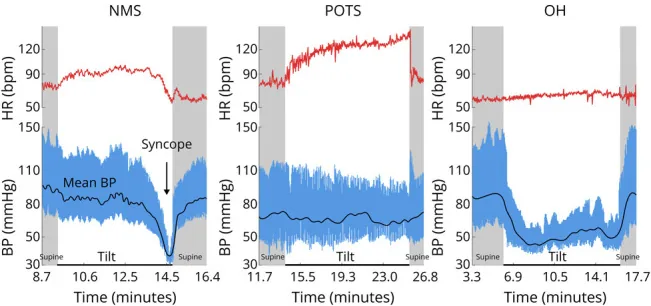
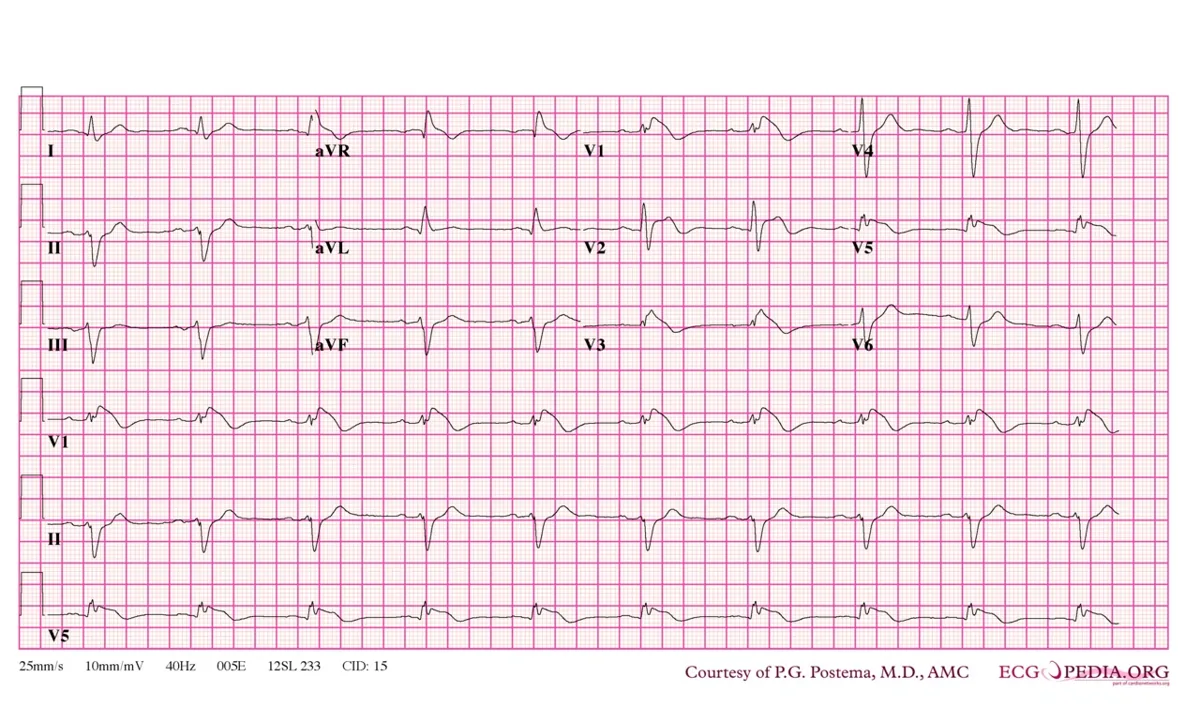 ECG
Definition
- Syncope: transient loss of consciousness from cerebral hypoperfusion with rapid onset, short duration, and spontaneous full recovery.
- Three main groups:
- Reflex syncope (neurally mediated): vasovagal, situational, carotid sinus syndrome.
- Orthostatic syncope: drug-induced, autonomic failure (Parkinson, MSA, diabetes), hypovolemia.
- Cardiac syncope: arrhythmia (brady/tachy), structural (AS, HOCM, PE, tamponade), ischemia — most dangerous group.
Aetiopathogenesis
- Reduced cerebral blood flow is the most common mechanism, usually due to reduced cardiac output: outflow obstruction (e.g. aortic stenosis, hypertrophic cardiomyopathy), systolic or diastolic dysfunction, arrhythmias or reduced venous return.
- Arrhythmias cause syncope when the rate is too fast for adequate ventricular filling (e.g. above 150–180/min) or too slow for adequate cardiac output (e.g. below 30–35/min).
- Vasovagal (neurocardiogenic) syncope: increased intrathoracic pressure, increased vagal tone or loss of sympathetic tone; common and benign.
- Orthostatic hypotension: failure of the normal compensatory mechanisms (sinus tachycardia, vasoconstriction) on standing; the most common cause in older people.
- Rare causes: basilar artery ischemia, pulmonary embolism, hypoglycemia (loss of consciousness rarely as abrupt as in syncope).
- Overall, the most common causes are vasovagal syncope and unexplained (idiopathic) cases; a smaller number have a serious, usually cardiac, cause.
Clinical features
Vasovagal syncope
- Classic triad: prodromes (nausea, sweating, pallor) → syncope → rapid recovery supine.
- Triggers: prolonged standing, warm rooms, pain, sight of blood, micturition, defecation, coughing.
Orthostatic syncope
- Classic orthostatic hypotension: sustained fall in systolic blood pressure of at least 20 mmHg or in diastolic pressure of at least 10 mmHg within 3 minutes of standing.
- Delayed orthostatic hypotension: sustained fall of the same magnitude that occurs only after more than 3 minutes of standing.
- Initial orthostatic hypotension: transient fall (systolic by more than 40 mmHg, diastolic by more than 20 mmHg) within 15 seconds of standing.
Clues to the cause
- Vasovagal: triggered by unpleasant physical or emotional stimuli (pain, fright), usually when upright, with warning symptoms such as nausea, weakness, yawning, blurred vision and sweating; recovery prompt but not immediate (usually 5–15 minutes).
- Cardiac: sudden onset and spontaneous termination without warning, immediate recovery; syncope on exertion suggests outflow obstruction or an exercise-induced arrhythmia, often with chest pain or palpitations; syncope while lying down suggests an arrhythmia.
- Red flags: syncope during exertion, several events within a short time, heart murmur or other signs of structural heart disease, older age, significant injury during syncope, sudden unexpected death in the family.
- Pointers to a seizure rather than syncope: jerking lasting more than a few seconds, incontinence, drooling, tongue biting, postictal confusion.
Diagnosis
- History and witness account: situation, posture and duration of standing before the event, warning symptoms, length of recovery, associated symptoms; past medical history, drugs taken, early sudden cardiac death in the family.
- Physical examination: heart rate and blood pressure supine and after 3 minutes of standing; pulse irregularity, heart murmurs and their change with the Valsalva maneuver, standing or squatting; signs of injury, neurological examination.
- ECG in all patients: arrhythmia, conduction abnormality, hypertrophy, pre-excitation, QT prolongation, Brugada pattern, pacemaker malfunction, ischemia or infarction.
- Pulse oximetry during or immediately after the event (hypoxemia suggesting pulmonary embolism).
- Rhythm recording: ambulatory ECG over at least 24 hours, event recorder or implantable loop recorder depending on the frequency of events.
- Echocardiography for unexplained or exercise-induced syncope, heart murmurs or suspected intracardiac tumors.
- Tilt table testing when an orthostatic or vasovagal cause is suspected.
- Targeted laboratory tests: pregnancy test in women of childbearing age, hematocrit if anemia is suspected, electrolytes, troponin if infarction is suspected.
Implantable loop recorder
- Subcutaneously implanted event recorder for infrequent events, such as syncope at intervals of more than 30 days; the battery lasts several years.
- A memory loop stores the ECG for seconds to minutes before and after activation; recording can be triggered, for example, with a small magnet.
Treatment principles
- Treatment depends on the cause, which is first classified by history, examination and ECG.
- In reflex syncope, education, avoidance of triggers and physical counter-pressure manoeuvres are the priorities; in orthostatic syncope, causative medications are reviewed and fluid intake and compression are optimised.
- Cardiac syncope requires treatment of the underlying disease, such as a pacemaker for bradycardia, catheter ablation or a defibrillator for arrhythmias, or valve intervention.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Takotsubo cardiomyopathy
- Ventricular tachycardia
- Atrial flutter
- Atrial septal defect and patent foramen ovale
- Wolff-Parkinson-White syndrome
- Acute pericarditis
- Aortic regurgitation
- Aortic valve stenosis
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.