Mixed connective tissue disease (Sharp syndrome)
Board exam relevance: in 1 of more than 100 exam reports · rank 181- Synonyms
- Sharp syndrome, MCTD, overlap syndrome, anti-U1 RNP
- Specialty
- Internal medicine · Rheumatology & immunology
- Images
- Clinical 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
Mixed connective tissue disease (MCTD, Sharp syndrome) is an uncommon, specifically defined syndrome with overlapping features of systemic lupus erythematosus, systemic sclerosis, and polymyositis. It is characterized by very high titers of antinuclear antibodies against U1 ribonucleoprotein (U1 RNP).
Occurrence & epidemiology
MCTD occurs worldwide and in all ethnic groups. Incidence peaks in adolescence; females are affected more often.
Aetiopathogenesis
It is an autoimmune disease within the spectrum of connective tissue diseases. Many patients initially have an undifferentiated connective tissue disease; the clinical pattern changes over time. A significant minority evolve into a well-defined disease such as systemic sclerosis, systemic lupus erythematosus, or an inflammatory myopathy a few years after diagnosis.
Clinical features
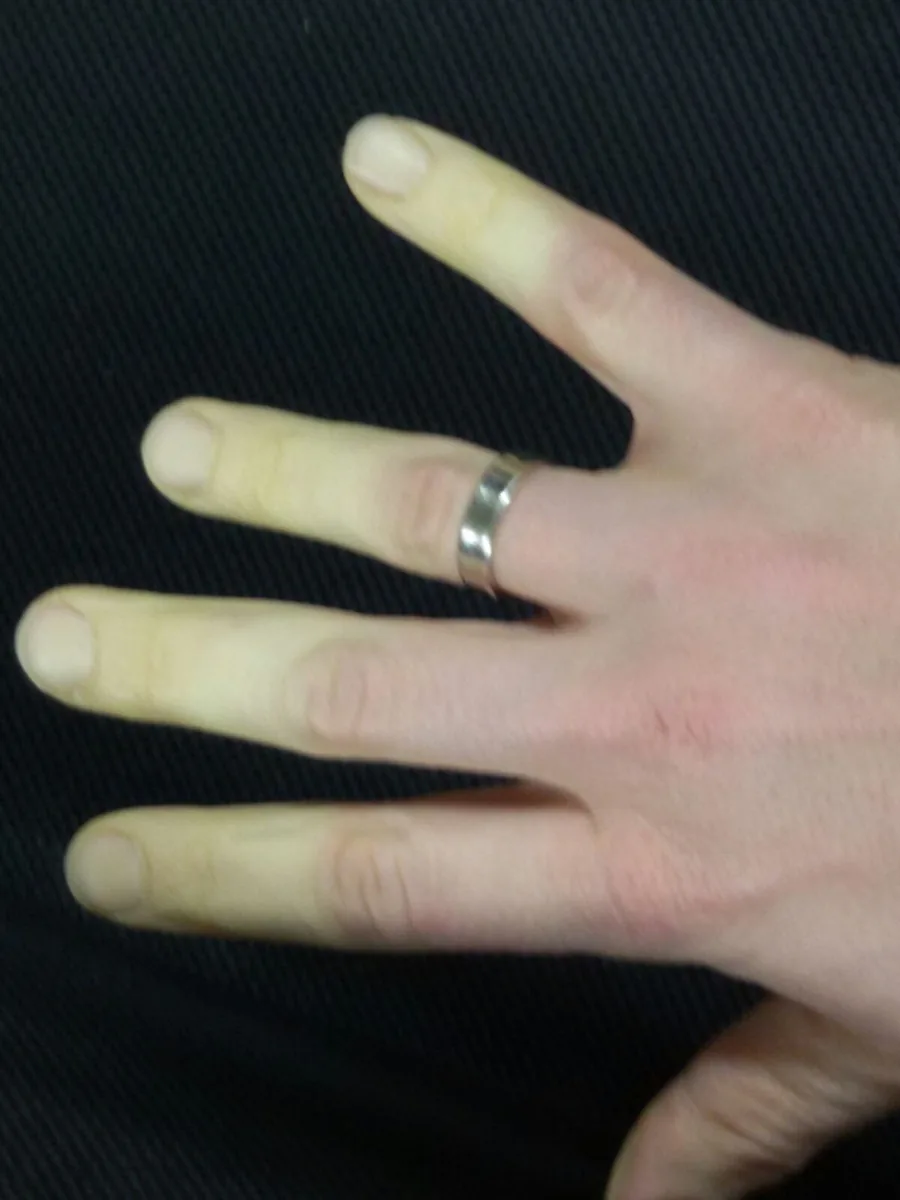
- Raynaud syndrome, often years before other symptoms
- Diffuse swelling of the hands typical at onset but not universal
- Skin: chilblains, discoid lesions, lupus-like malar rash; scleroderma-like skin changes, ischemic necrosis or ulceration of the fingertips
- Joints: polyarthralgias in almost all, arthritis in 75 %, usually nondeforming; erosive changes and deformities as in rheumatoid arthritis also possible
- Muscles: proximal muscle weakness with elevated muscle enzymes
- Gastrointestinal: dysmotility similar to systemic sclerosis
- Lungs: affected in up to 75 %, mainly pleural effusions and interstitial lung disease; pulmonary hypertension in up to 13 %
- Kidney: in about 25 %, usually mild (mostly membranous nephropathy)
- Heart: pericarditis common, myocarditis uncommon; secondary Sjögren syndrome possible
Diagnosis
- ANA on indirect immunofluorescence in almost all, high titer with a speckled pattern.
- Anti-U1 RNP antibodies, usually at very high titers; not sufficient alone, typical clinical findings are required.
- Anti-Sm and anti-dsDNA are measured to exclude SLE; anti-dsDNA is negative in MCTD by definition.
- Rheumatoid factor frequently positive, sometimes high titer; ESR and CRP often elevated.
- Organ assessment: pulmonary function tests and echocardiography to look for pulmonary hypertension; creatine kinase, MRI, electromyography, or muscle biopsy when myositis is suspected; further tests depending on renal or pulmonary involvement.
Treatment principles
- Treatment depends on the organs involved: joint and skin involvement is usually treated with antimalarials, low-dose glucocorticoids or immunosuppressants.
- Raynaud's phenomenon is managed with protection from cold and vasodilating calcium channel blockers.
- Because pulmonary hypertension largely determines prognosis, it is screened for regularly and treated specifically if present; care is led by rheumatology within a multidisciplinary team.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Rheumatology & immunology
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Rheumatoid arthritis · Systemic lupus erythematosus (SLE) · Granulomatosis with polyangiitis (GPA)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.