Adult-onset Still's disease
- Synonyms
- AOSD, Still disease, adult Still disease, systemic JIA
- Specialty
- Internal medicine · Rheumatology & immunology
- Images
- Clinical 2
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
Definition
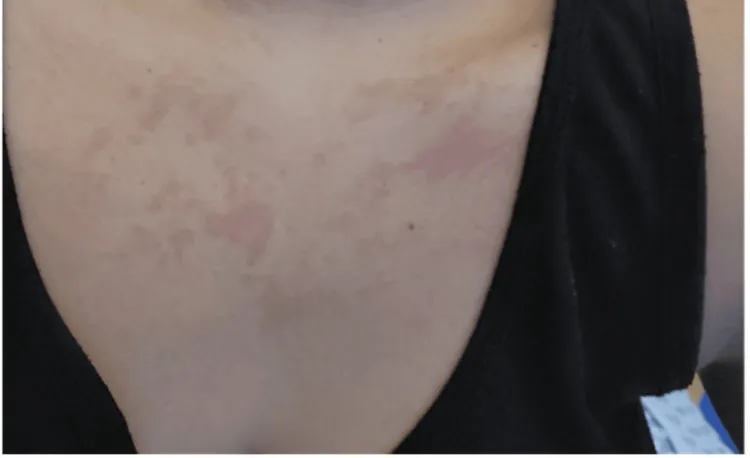
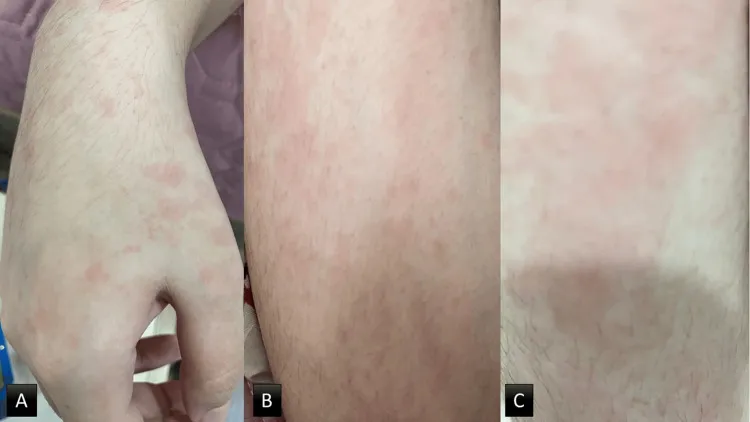
Adult-onset Still's disease (AOSD) is a rare autoinflammatory disease of unknown cause. It is characterized by the classic triad of arthralgia or arthritis, daily (quotidian) fever spikes, and an evanescent salmon-colored rash. Systemic juvenile idiopathic arthritis is considered the same disease with onset in childhood (Still's disease continuum).
Classification
Yamaguchi criteria (at least 5 criteria, including at least 2 major criteria, after exclusion of infections, malignancies, and other rheumatic diseases):
- Major criteria: fever ≥ 39 °C for at least 1 week; arthralgia for at least 2 weeks; typical rash; leukocytosis ≥ 10,000/µL with at least 80 % granulocytes
- Minor criteria: sore throat; lymphadenopathy and/or splenomegaly; liver dysfunction; negative rheumatoid factor and negative ANA
The Fautrel criteria additionally include the fraction of glycosylated ferritin.
Occurrence & epidemiology
The annual incidence is about 0.16 per 100,000. Young adults between 17 and 35 years are typically affected. Unlike the systemic juvenile form, women are affected more often (about 70 %).
Aetiopathogenesis
The cause is unknown. Central is an overactivation of the innate immune system with increased production of proinflammatory cytokines, mainly interleukin-1β, interleukin-18, and interleukin-6. Gene expression patterns and genetic profiles resemble those of systemic juvenile idiopathic arthritis.
Clinical features
- Fever with daily spikes above 39 °C.
- Rash: evanescent, salmon-colored, maculopapular.
- Arthralgia or arthritis; myalgia.
- Sore throat, frequently as a prodromal symptom.
- Lymphadenopathy, splenomegaly, liver involvement, serositis.
- Macrophage activation syndrome (MAS) as the most dangerous complication.
- Adult-onset Still's disease accounts for 15–20 % of all cases of fever of unknown origin.
Diagnosis
- There is no confirmatory test; the diagnosis is clinical and a diagnosis of exclusion versus infections (especially sepsis and infectious mononucleosis), malignancies (especially malignant lymphoma), and other rheumatic diseases.
- Laboratory tests: leukocytosis with neutrophilia, markedly elevated ferritin, elevated inflammatory markers and liver enzymes; rheumatoid factor and ANA negative. A simplified approach in fever of unknown origin combines arthralgia, sore throat, neutrophilia, and ferritin ≥ 5 times normal.
- Biomarkers such as interleukin-18 reflect disease activity; very high ferritin may indicate MAS.
Treatment principles
- Before treatment is started, infection and malignancy must be carefully excluded as differential diagnoses.
- According to current European recommendations, IL-1 or IL-6 inhibitors are started early, with glucocorticoids used only alongside and for a short period.
- The treatment target is clinically inactive disease or sustained remission; macrophage activation syndrome is an emergency and is treated promptly with high-dose glucocorticoids, IL-1 inhibitors and further immunosuppressants.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Rheumatology & immunology
- Rheumatoid arthritis
- Systemic lupus erythematosus (SLE)
- Granulomatosis with polyangiitis (GPA)
- Polymyalgia rheumatica
- Axial spondyloarthritis (ankylosing spondylitis)
- CPPD disease (pseudogout, chondrocalcinosis)
- Dermatomyositis and polymyositis
- Eosinophilic granulomatosis with polyangiitis (EGPA)
- Gout
- IgA vasculitis (Henoch-Schönlein purpura)
- Microscopic polyangiitis
- Mixed connective tissue disease (Sharp syndrome)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Rheumatoid arthritis · Systemic lupus erythematosus (SLE) · Granulomatosis with polyangiitis (GPA)
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.