Gout
Board exam relevance: in 3 of more than 100 exam reports · rank 111- Synonyms
- gouty arthritis, podagra, gout flare, hyperuricemia, uric acid, tophus
- Specialty
- Internal medicine · Rheumatology & immunology
- Images
- Clinical 2 · Histology 1 · X-ray 1 · Blood smear & cytology 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (5)
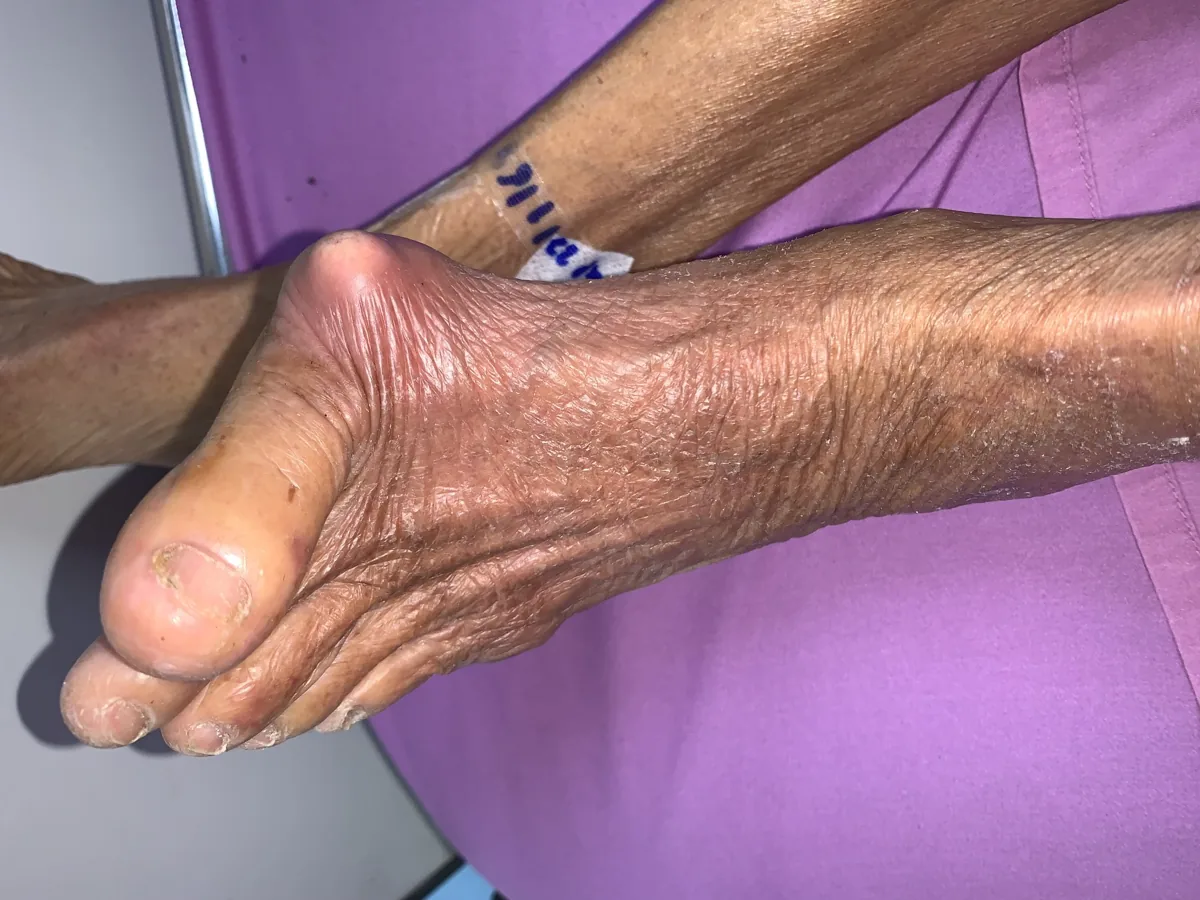
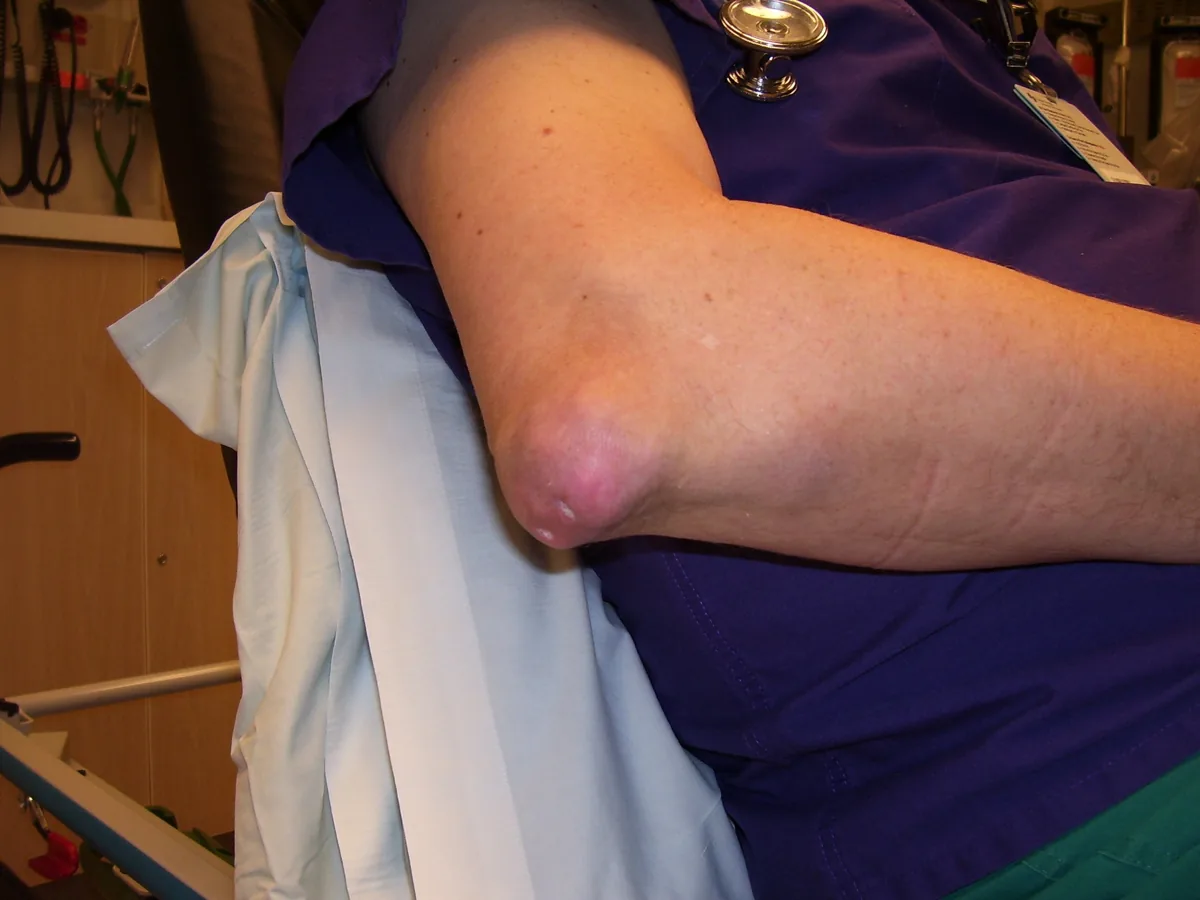
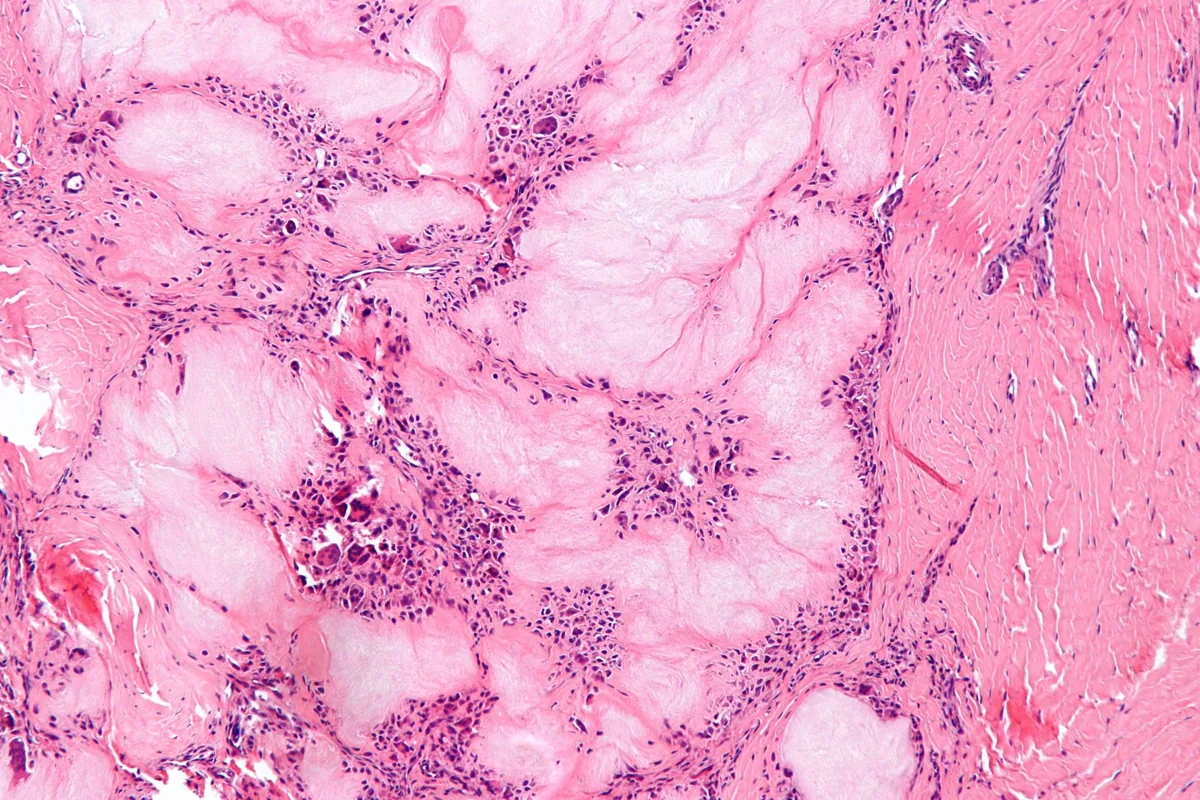 Histology
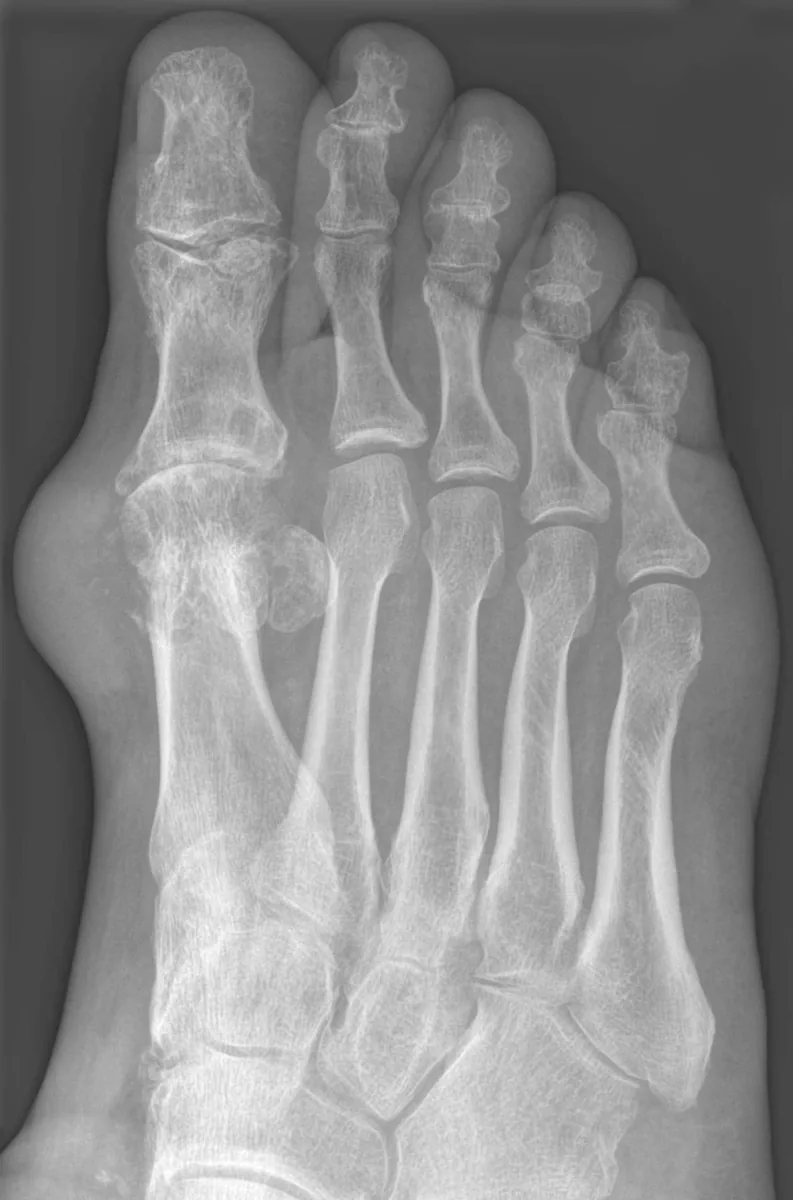 X-ray
 Blood smear & cytology
Definition
Gout is caused by precipitation of monosodium urate crystals in and around joints. It usually causes recurrent acute and later also chronic arthritis. Hyperuricemia (serum urate above 6.8 mg/dL or 0.4 mmol/L, the saturation limit) is almost always present. The first flare usually affects a single joint, often the first metatarsophalangeal joint (podagra).
Occurrence & epidemiology
Gout is more common in men than in women. It usually develops in middle age in men and after menopause in women, because estrogen has a partially protective effect. It is rare in young people but is often more severe when it begins before age 30. Hyperuricemia and gout have a strong hereditary component.
Aetiopathogenesis
- Decreased renal excretion (by far the most common cause): hereditary due to variants of urate transporters, with reduced glomerular filtration rate, and due to certain diuresis-promoting drugs; alcohol increases purine breakdown and blocks tubular urate secretion via lactate.
- Increased production (rare): increased cell turnover in lymphoma, leukemia, hemolytic anemia, psoriasis, and tumor lysis syndrome, obesity, and rare enzyme defects (HGPRT deficiency, complete form as Lesch-Nyhan syndrome).
- Purine-rich food, beer (including nonalcoholic beer), and high-fructose corn syrup usually contribute only slightly.
The needle-shaped crystals deposit in avascular tissues (cartilage, tendons, bursae) and at cooler distal sites (ears, finger pads). Tophi are crystal aggregates encased in granulomatous tissue. Flares are triggered by trauma, infections, alcohol, purine-rich meals, or rapid changes in the serum urate level, and also occur after surgery.
Clinical features
- Acute gout flare: sudden, often nocturnal pain becoming excruciating within a few hours, with swelling, warmth, redness, and exquisite tenderness; the skin is tense, shiny, red to purplish. Occasionally fever, tachycardia, chills.
- Location: most often the first metatarsophalangeal joint, also the instep, ankle, knee, wrist, and elbow; rarely the hip, shoulder, sacroiliac joint, or cervical spine.
- Course: the first flares usually resolve spontaneously within 7–10 days; later several joints are involved and symptom-free intervals become shorter.
- Chronic tophaceous gout: firm, yellowish-white nodules on the fingers, hands, feet, elbows, Achilles tendon, and ear; tophi may break through the skin and discharge chalky material; joint deformities and secondary osteoarthritis.
- Kidney: uric acid or calcium oxalate stones, tubulointerstitial damage.
- Common comorbidities: cardiovascular disease, obstructive sleep apnea, MASLD, and components of the metabolic syndrome; myocardial infarction risk is increased after flares.
Diagnosis
- Arthrocentesis with polarized light microscopy: demonstration of needle-shaped, strongly negatively birefringent urate crystals (yellow parallel, blue perpendicular to the compensator axis), free or phagocytosed; confirms the diagnosis. The fluid is inflammatory with usually 2,000–100,000 white cells/µL, more than 80 % neutrophils; septic arthritis is excluded by Gram stain and culture.
- Serum urate: supports the diagnosis but is neither sensitive nor specific; it is normal during a flare in at least 30 %.
- Radiographs: in chronic gout, punched-out subchondral lesions with overhanging margins, most often at the first metatarsophalangeal joint (visible from about 5 mm); joint space is preserved for a long time.
- Ultrasound: double-contour sign (urate deposition on the articular cartilage) and clinically inapparent tophi, sometimes even before the first flare.
- Dual-energy CT: shows urate deposits, helpful when synovial fluid cannot be obtained.
Treatment principles
- An acute gout attack is treated with anti-inflammatory therapy as early as possible, using non-steroidal anti-inflammatory drugs, systemic or intra-articular glucocorticoids or a specific anti-inflammatory gout drug; IL-1 blockade may be considered if these fail.
- In recurrent attacks, tophi or joint erosions, long-term urate-lowering therapy with xanthine oxidase inhibitors or uricosurics is started following a treat-to-target approach, initially with concomitant flare prophylaxis.
- Weight reduction, less alcohol and fructose-containing drinks and review of urate-raising medication are supportive.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Rheumatology & immunology
- Rheumatoid arthritis
- Systemic lupus erythematosus (SLE)
- Granulomatosis with polyangiitis (GPA)
- Polymyalgia rheumatica
- IgA vasculitis (Henoch-Schönlein purpura)
- Microscopic polyangiitis
- Mixed connective tissue disease (Sharp syndrome)
- Behçet's disease
- Polyarteritis nodosa
- Psoriatic arthritis
- Reactive arthritis
- Giant cell arteritis (temporal arteritis)
Keep learning: test yourself
One question from the InnereFuchs app on Gout – tap an answer.
Question 1 of 1
Diagnosis — Polarized Microscopy & Ultrasound: Uric acid determination during acute flare: _____.
Answer
Correct: often falsely normal → re-evaluate at 2–4 weeks. Uric acid determination during acute flare: often falsely normal → re-evaluate at 2–4 weeks.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.