Hypertrophic cardiomyopathy
Board exam relevance: in 3 of more than 100 exam reports · rank 111- Synonyms
- HCM, HOCM, hypertrophic obstructive cardiomyopathy, thickened heart muscle
- Specialty
- Internal medicine · Cardiology
- Images
- Echocardiography 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
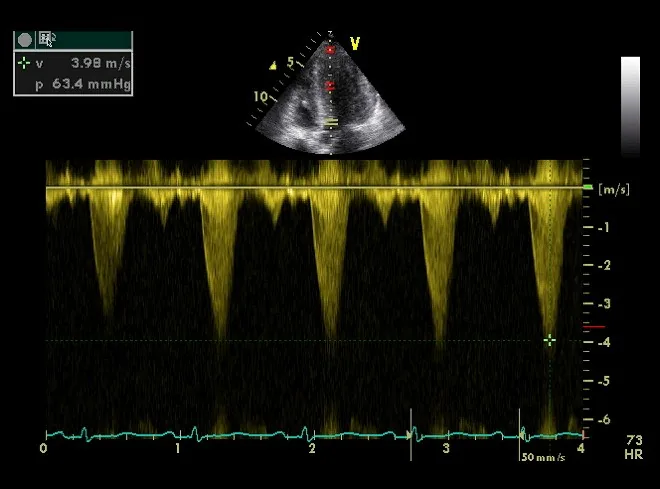 Echocardiography
Definition
Hypertrophic cardiomyopathy (HCM) is a mostly genetic myocardial disorder with left ventricular hypertrophy. In adults a maximal diastolic wall thickness of 15 mm or more (echocardiography or MRI) without an alternative cause is considered diagnostic; with a family history or a proven pathogenic sarcomeric variant a threshold of 13 mm or more is sufficient. This differs from hypertrophy due to pressure overload (e.g. aortic stenosis, hypertension).
Classification
- Obstructive HCM (HOCM): peak left ventricular outflow tract (LVOT) gradient of 30 mmHg or more at rest or with physiological provocation; gradients of 50 mmHg or more are generally considered sufficient to cause symptoms.
- Non-obstructive HCM.
- Morphology: most commonly asymmetric hypertrophy of the basal septum; also focal or symmetric forms, apical HCM (without outflow tract obstruction, more common in people of Asian descent) and midventricular obstruction, often with an apical aneurysm.
Occurrence & epidemiology
HCM is the most common monogenic cardiac disorder, with an estimated prevalence of 1:200 to 1:500 adults. About two-thirds of patients have dynamic outflow tract obstruction. Symptoms usually appear in early to mid-adulthood (30s to 50s).
Aetiopathogenesis
- Genetics: pathogenic variants in genes of the cardiac sarcomere, most frequently MYBPC3 and MYH7, are found in about 35 % of tested patients with clinical HCM; penetrance and expression vary markedly.
- Phenocopies: Fabry disease, Danon disease, Andersen disease and other glycogen storage diseases can mimic HCM.
- Pathophysiology: excessive actin-myosin cross-bridge formation and abnormal calcium handling cause hypercontractility and reduced compliance. The stiff chamber fills poorly, and end-diastolic and pulmonary venous pressures rise.
- Outflow tract obstruction: interplay of the thickened basal septum and systolic anterior motion (SAM) of the often elongated anterior mitral leaflet, with accompanying posteriorly directed mitral regurgitation.
- Ischemia despite normal epicardial coronary arteries due to microvascular dysfunction, capillary-myocyte mismatch and increased oxygen demand.
Clinical features
- Highly variable presentation; symptoms frequently on exertion: dyspnea, chest pain (usually resembling typical angina), palpitations, syncope.
- Exertional syncope results from outflow tract obstruction or arrhythmia and is an important warning sign of sudden cardiac death.
- Symptoms are aggravated by conditions that reduce preload or afterload and increase heart rate and contractility.
- Auscultation: dynamic late-peaking systolic murmur at the left sternal border in the 3rd or 4th intercostal space; louder with the Valsalva maneuver and on standing up from squatting, softer with handgrip, prolonged squatting or passive leg raising; possibly an additional mitral regurgitation murmur at the apex; often a fourth heart sound.
- Pulse: with obstruction a brisk upstroke, bifid peak and rapid downstroke; sustained apex beat; blood pressure and heart rate usually normal.
Histology
Classic findings are cardiomyocyte hypertrophy, disorganized arrangement of myocytes ("myocyte disarray"), interstitial fibrosis and thick-walled intramural coronary arteries.
Diagnosis
- History: syncope and other symptoms; three-generation family history (HCM, unexplained sudden cardiac death).
- Echocardiography: extent and distribution of hypertrophy, outflow tract gradient at rest and with provocation, systolic anterior motion of the mitral valve, mitral regurgitation; usually a small cavity with normal or hyperdynamic systolic function.
- Cardiac MRI: precise wall thickness measurement including segments difficult to visualise; apical aneurysms; late gadolinium enhancement reflecting fibrosis.
- ECG: frequently left ventricular hypertrophy with repolarisation abnormalities (deep T-wave inversion, ST depression), Q waves, signs of left atrial enlargement; sometimes bundle branch block or pre-excitation.
- Ambulatory ECG over 24–48 hours: atrial arrhythmias and ventricular tachycardia (a risk factor).
- Exercise testing: provocation of outflow tract obstruction, functional capacity.
- Chest X-ray: often normal, possibly an enlarged left atrium.
- Genetic testing and examination of relatives.
Treatment principles
- In symptomatic obstructive disease, beta blockers or non-dihydropyridine calcium channel blockers are first-line; vasodilators and hypovolaemia are avoided.
- For refractory symptoms, cardiac myosin inhibitors or septal reduction by myectomy or alcohol septal ablation are options.
- To prevent sudden cardiac death, risk is stratified individually and an ICD is implanted where indicated; genetic family screening is part of management.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Infective endocarditis
- Ventricular fibrillation and sudden cardiac death
- Cardiac amyloidosis
- Cardiogenic shock
- Constrictive pericarditis
- Long QT syndrome and torsades de pointes
- Mechanical complications of myocardial infarction
- Mitral regurgitation
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.