Hypertensive emergency and hypertensive crisis
Board exam relevance: in 6 of more than 100 exam reports · rank 59- Synonyms
- hypertensive crisis, hypertensive urgency, malignant hypertension, hypertensive encephalopathy, very high blood pressure
- Specialty
- Internal medicine · Cardiology
- Images
- Clinical 1 · MRI 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
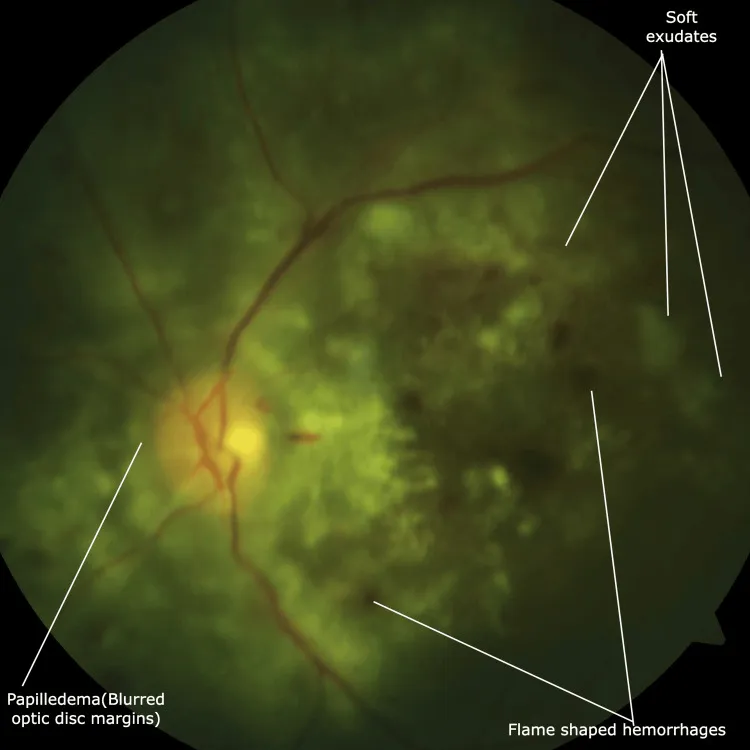
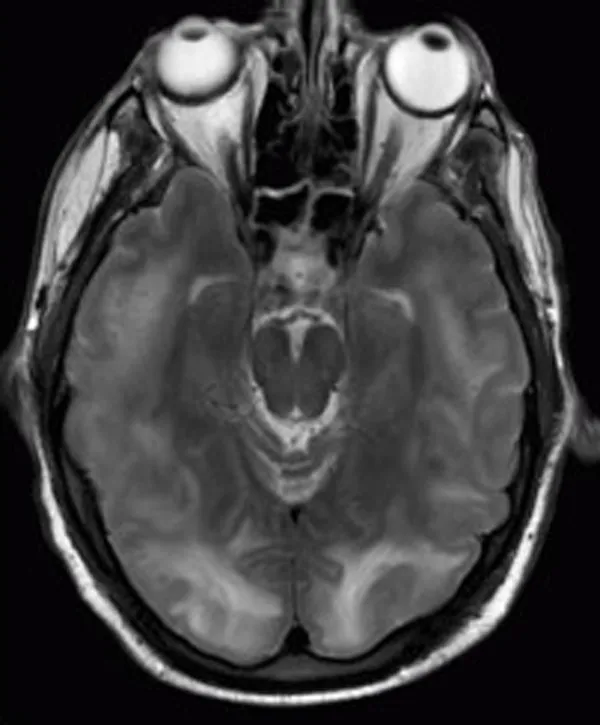 MRI
Definition
A hypertensive emergency is severe hypertension (according to the German NVL Hypertension above 180 mmHg systolic or above 110 mmHg diastolic, according to the US definition systolic 180 mmHg or higher and/or diastolic 120 mmHg or higher) with signs of acute damage to target organs, mainly the brain, cardiovascular system and kidneys. In hypertensive urgency (hypertensive crisis without organ damage), blood pressure is similarly elevated, but acute organ damage is absent (at most grade 1–2 retinopathy).
Classification
Types of organ damage
- hypertensive encephalopathy
- hypertensive retinopathy; the combination with stage III/IV retinopathy (cotton-wool spots, papilledema) is called malignant hypertension
- preeclampsia or eclampsia
- acute left ventricular failure with pulmonary edema
- myocardial ischemia
- acute aortic dissection
- renal failure
Aetiopathogenesis
In hypertensive encephalopathy, cerebral autoregulation fails: normally cerebral vessels constrict as pressure rises, but above a mean arterial pressure of about 160 mmHg (lower in previously normotensive people) they dilate. The high pressure is then transmitted directly to the capillary bed; plasma passes into the brain tissue, causing cerebral edema with papilledema.
The most common cause of hypertensive urgency is anxiety. Crises also occur in secondary forms of hypertension, such as pheochromocytoma. In stroke and intracranial hemorrhage, elevated blood pressure is often a consequence rather than a cause.
Clinical features
- Neurological: rapidly changing deficits such as confusion, transient cortical blindness, hemiparesis or hemisensory loss, seizures; global deficits (confusion, obtundation, coma) suggest encephalopathy, focal deficits with normal mental status suggest stroke
- Cardiovascular: chest pain and dyspnea; jugular venous distention, basal crackles and third heart sound in pulmonary edema; pulse asymmetry between the arms in aortic dissection
- Renal: often asymptomatic; lethargy or nausea in advanced renal failure
- Eyes: severe retinopathy (sclerosis, cotton-wool spots, arteriolar narrowing, hemorrhage, papilledema) almost always in encephalopathy, often in other emergencies
Diagnosis
The diagnosis is based on a systolic blood pressure above 180 mmHg and evidence of organ involvement. Physical examination focuses on the target organs with neurological examination, fundoscopy and cardiovascular examination.
Organ-specific evaluation
- Brain: with neurological findings, head CT to detect hemorrhage, edema or infarction
- Heart: ECG with acute ischemic changes; with chest pain or dyspnea additionally a chest X-ray
- Kidney: electrolytes and creatinine; urinalysis with red blood cells, red cell casts and proteinuria as signs of renal involvement
- Eye: funduscopy (sclerosis, cotton-wool spots, arteriolar narrowing, hemorrhages, papilledema)
- Aorta: pulse difference between the arms as a clue to aortic dissection
Treatment principles
- The crucial step is distinguishing a hypertensive emergency with acute organ damage from hypertensive urgency without organ damage.
- In an emergency, blood pressure is lowered in a controlled, titrated manner with intravenous antihypertensives under intensive care monitoring, avoiding abrupt falls; faster lowering is reserved for specific situations such as aortic dissection or acute pulmonary oedema.
- Urgency without organ damage is treated orally over hours to days, followed by adjustment of long-term therapy and a search for secondary causes.
Specific treatment regimens with drugs and doses are covered in the InnereFuchs app.
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Cardiology
- Acute coronary syndrome (heart attack, STEMI/NSTEMI)
- Heart failure
- Atrial fibrillation
- Arterial hypertension (high blood pressure)
- Hypertrophic cardiomyopathy
- Infective endocarditis
- Ventricular fibrillation and sudden cardiac death
- Cardiac amyloidosis
- Cardiogenic shock
- Constrictive pericarditis
- Long QT syndrome and torsades de pointes
- Mechanical complications of myocardial infarction
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the InnereFuchs app – free, in your browser or as an app.
Related pages: Acute coronary syndrome (heart attack, STEMI/NSTEMI) · Heart failure · Atrial fibrillation
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.