Thrombocytopenia in pregnancy
Exam relevance: in 3 of more than 150 board exam reports · rank 125
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Histology & cytology 1
- Exam relevance
- 3 of more than 150 reports · rank 125
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
 Histology & cytology
Definition
- Thrombocytopenia in pregnancy is defined as a platelet count below 150,000/µl; it occurs in 7–12% of pregnancies.
Classification
- It is mild at counts above 100,000/µl and moderate at 50,000–100,000/µl.
- By cause, obstetric forms such as gestational thrombocytopenia and pre-eclampsia are distinguished from systemic disorders such as immune thrombocytopenia (ITP) and thrombotic thrombocytopenic purpura.
Occurrence & epidemiology
Epidemiology
- It is the second most common haematological abnormality of pregnancy.
Aetiopathogenesis
Aetiology and pathogenesis
- Gestational thrombocytopenia accounts for 75–80% of all cases, making it the most common cause, and probably results from haemodilution and accelerated platelet clearance.
- In ITP, maternal IgG antiplatelet antibodies cross the placenta and can cause fetal and neonatal thrombocytopenia.
Clinical features
Clinical features and complications
- Gestational thrombocytopenia mostly occurs in the mid-to-late second or the third trimester and is not associated with neonatal thrombocytopenia.
- Typical features are mucosal bleeding such as epistaxis and gingival bleeding, as well as petechiae and ecchymoses; life-threatening bleeding is infrequent.
Diagnosis
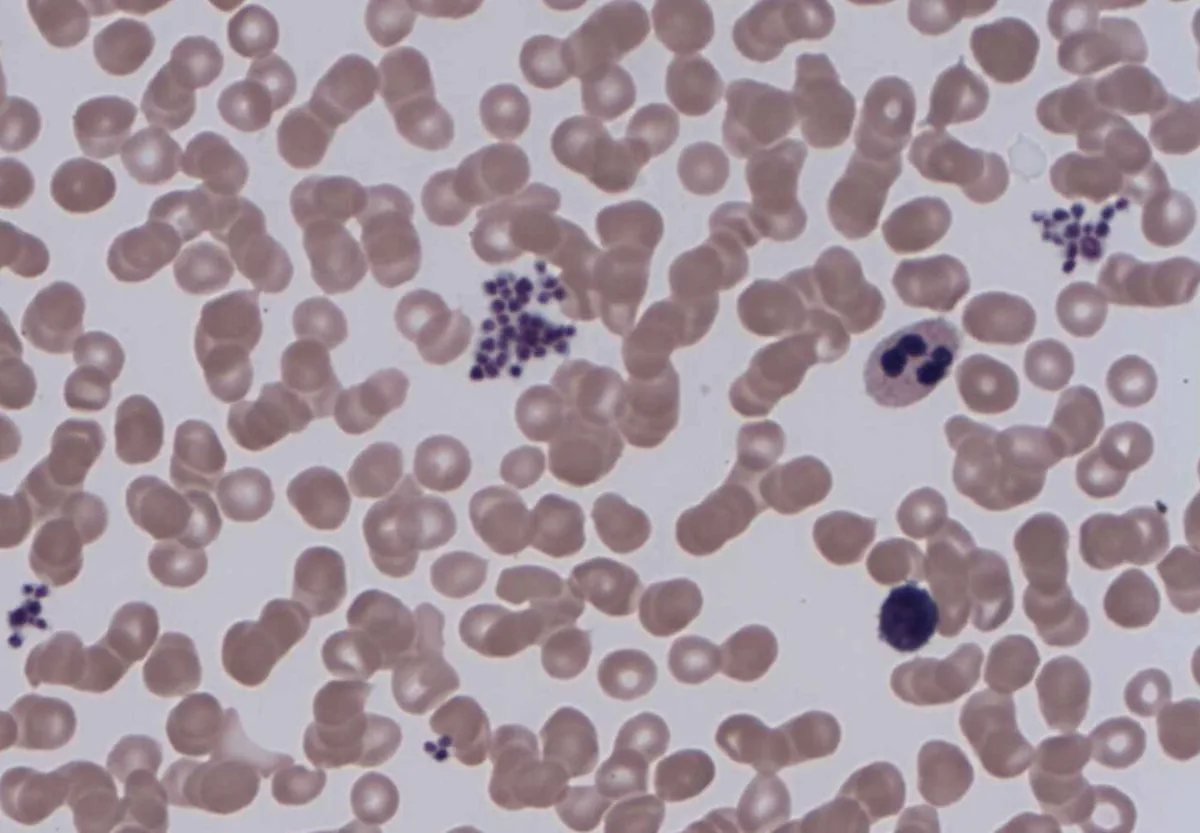
- Full blood count and blood smear serve to exclude pseudothrombocytopenia due to EDTA-induced platelet clumping.
- ITP typically presents before pregnancy or in the first trimester and is a diagnosis of exclusion.
- In thrombotic microangiopathy, schistocytes on the blood smear, raised bilirubin and LDH and decreased haptoglobin are found.
Treatment principles
- Treatment depends on the cause; the common gestational thrombocytopenia requires no treatment.
- In immune thrombocytopenia, glucocorticoids or immunoglobulins are used if there is a bleeding tendency or before delivery; thrombocytopenia in pre-eclampsia or HELLP syndrome is treated by delivery, and thrombotic microangiopathy by plasma exchange.
- The mode of delivery is based on obstetric criteria, the option of regional anaesthesia is agreed with the anaesthetist, and the newborn's platelets are checked if the mother has immune thrombocytopenia.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Toxoplasmosis in pregnancy · Triple I (intra-amniotic infection) · Varicella in pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.