Selective fetal growth restriction in twins (sFGR)
Exam relevance: in 1 of more than 150 board exam reports · rank 171
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Ultrasound 1
- Exam relevance
- 1 of more than 150 reports · rank 171
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
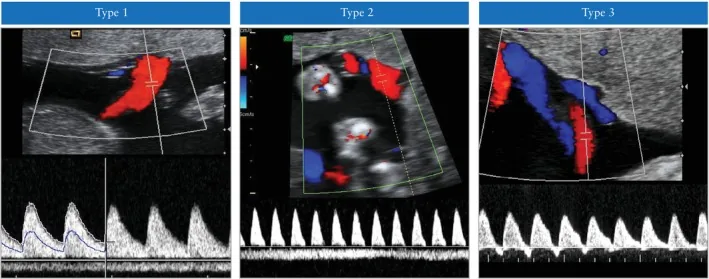 Ultrasound
Definition
- Selective fetal growth restriction is conventionally defined as an estimated fetal weight of one twin below the 10th centile with an intertwin weight discordance of at least 25%.
- By Delphi consensus, in monochorionic twins an estimated weight of one twin below the 3rd centile is sufficient; otherwise at least two of four criteria are required: estimated weight or abdominal circumference of one twin below the 10th centile, weight discordance of 25% or more, or umbilical artery pulsatility index of the smaller twin above the 95th centile.
Classification
Selective intrauterine growth restriction (sIUGR)
- Selective intrauterine growth restriction is present when one fetus is below the 10th centile or there is an estimated fetal weight discordance of approximately 25%.
- Type II is characterised by persistently absent or reversed end-diastolic flow and is associated with early deterioration.
- Type III shows intermittent absent or reversed flow due to a large network of anastomoses and carries the risk of sudden fetal death and neurological damage to the larger fetus.
- In monochorionic twins, 24 weeks of gestation separates early from late selective growth restriction.
- The Gratacós classification is based on end-diastolic flow in the umbilical artery of the smaller twin: type I positive, type II absent or reversed, type III cyclically or intermittently absent or reversed.
Aetiopathogenesis
Aetiology and pathogenesis
- The main cause is unequal sharing of placental mass and vasculature between the twins.
Clinical features
Clinical features and complications
- In type I, overall twin survival exceeds 90%.
- Type II carries a high risk of intrauterine death of the growth-restricted twin and of very preterm birth.
- In type III, there is an unpredictable 10–20% risk of sudden death of the growth-restricted fetus and neurological morbidity of up to 20% in the surviving larger twin.
Diagnosis
- The basis is ultrasound biometry of both fetuses with calculation of weight discordance and Doppler of the umbilical artery.
Treatment principles
- Care is provided in a specialist fetal medicine centre; management depends on the umbilical artery Doppler of the smaller twin and gestational age.
- With favourable Doppler findings, close expectant surveillance is used; with unfavourable findings, options such as early delivery, fetoscopic laser coagulation or selective reduction by cord occlusion are discussed.
- Because the intrauterine death of one twin also endangers the other, the decision is made together with the parents after detailed counselling.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Syphilis in gynaecology and pregnancy · TAPS and TRAP sequence · Post-term pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.