Puerperal mastitis
Exam relevance: in 3 of more than 150 board exam reports · rank 125
- Synonyms
- mastitis, breast infection, blocked duct
- Specialty
- Obstetrics · Birth & puerperium
- Images
- Clinical 1
- Exam relevance
- 3 of more than 150 reports · rank 125
- In the app
- 2 flashcards · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
- Puerperal (lactational) mastitis is an inflammation of the lactating breast that usually manifests within the first 6 weeks after birth.
Classification
- Lactational mastitis is distinguished from non-lactational chronic inflammatory forms such as periductal and idiopathic granulomatous mastitis; breast abscess is a complication of both.
Aetiopathogenesis
Aetiology and risk factors
- It typically arises from milk stasis and bacterial infection through damaged skin; staphylococci are the commonest causative organisms.
- In the review, nipple damage was the risk factor most consistently associated with mastitis.
Clinical features
Picture
- Puerperal mastitis usually appears in the second to fourth week after birth.
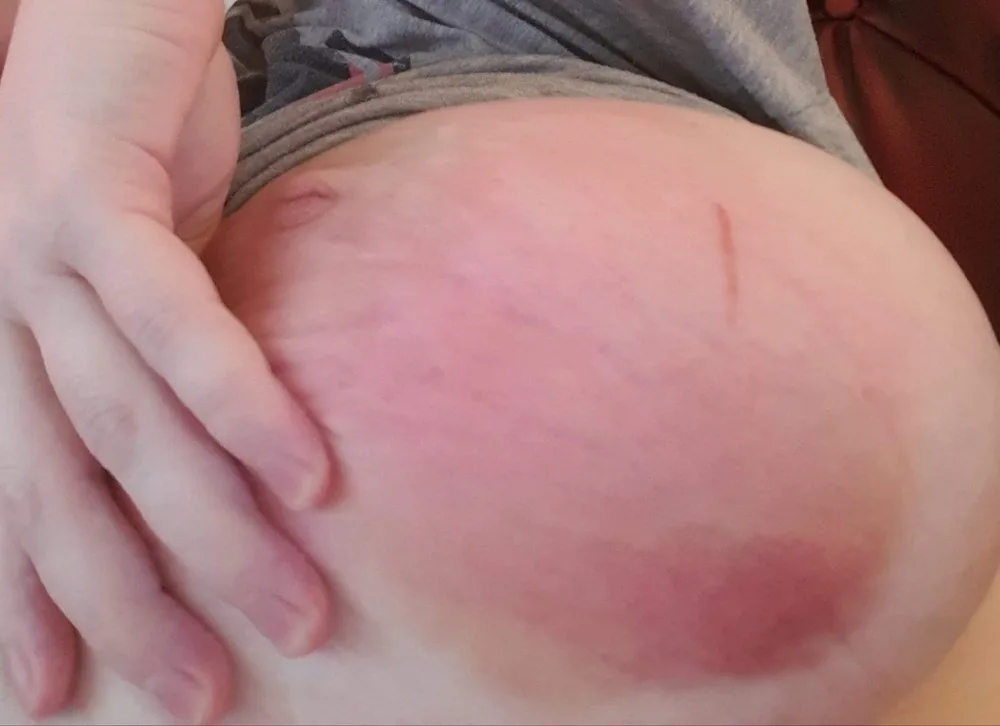
- Clinically there is usually one-sided, often wedge-shaped redness with warmth, pain, fever above 38.5 °C and feeling unwell.
- The commonest organism is Staphylococcus aureus; the portal of entry is cracks in the nipple.
- On ultrasound you look for a hypoechoic, possibly septated collection indicating an abscess.
Milk stasis
- Typical are a localised, tender lump with redness and at most a slight rise in temperature.
- The difference from mastitis lies in the degree of systemic symptoms and in the fever.
Clinical features and complications
- Breast abscesses are very rare, occasionally caused by MRSA, and more frequent in smokers and women with higher body weight.
Diagnosis
Typical imaging findings
- Clinical finding: A sharply outlined, wedge-shaped area of redness runs from the periphery towards the nipple; the overlying skin is tense and warm. There is no retraction, no peau d orange and no palpable fluctuation.
- In unclear or non-lactational mastitis, imaging, histology and bacterial culture are used for evaluation.
Treatment principles
- The mainstay is continued breastfeeding on demand without excessive pumping, so that milk production is not stimulated further.
- Cooling, anti-inflammatory analgesics, good breast support and rest are helpful additions; according to more recent recommendations, heat and vigorous massage are generally no longer advised.
- If there is no prompt improvement or marked systemic symptoms are present, antibiotics active against staphylococci and compatible with breastfeeding are given; weaning is rarely necessary and is then supported with a prolactin inhibitor.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning: test yourself
One question from the GynFuchs app on Puerperal mastitis – tap an answer.
Question 1 of 1
The Inflamed Breast: Puerperal mastitis characteristically presents with _____.
Answer
Correct: a wedge-shaped erythema, warmth, fever, and chills, most often caused by Staphylococcus aureus. Puerperal mastitis characteristically presents with a wedge-shaped erythema, warmth, fever, and chills, most often caused by Staphylococcus aureus.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.