Peripartum cardiomyopathy
- Specialty
- Obstetrics · Birth & puerperium
- Images
- Ultrasound 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
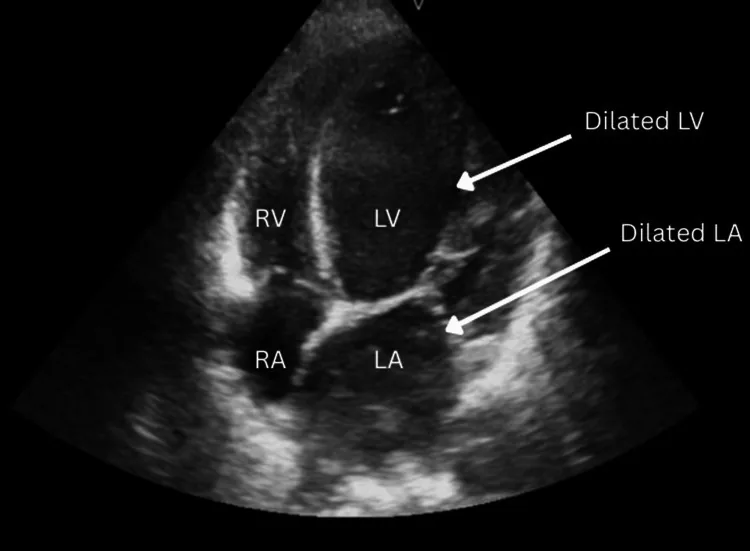
- According to the ESC working group, peripartum cardiomyopathy is heart failure towards the end of pregnancy or postpartum without another identifiable cause, with left ventricular systolic dysfunction and an ejection fraction below 45%; the left ventricle may or may not be dilated.
- The classic 2000 definition required onset in the last month of pregnancy or within 5 months after birth without pre-existing structural heart disease; it is a diagnosis of exclusion.
Occurrence & epidemiology
Epidemiology
- Most women develop symptoms in the first month after birth; onset is possible from the third trimester up to 6 months postpartum.
Aetiopathogenesis
Aetiology and risk factors
- Increased oxidative stress is considered central: via cathepsin D it causes cleavage of prolactin into an anti-angiogenic, pro-apoptotic 16-kDa fragment; in addition, familial clustering and variants in cardiomyopathy genes such as TTN occur.
Clinical features
Clinical features and complications
- Typical are congestive features such as exertional dyspnoea, orthopnoea, paroxysmal nocturnal dyspnoea, dry cough and pedal oedema, and non-specific complaints such as fatigue, palpitations and light-headedness, which resemble physiological changes of pregnancy.
- Thromboembolic complications, life-threatening arrhythmias, cardiogenic shock and sudden cardiac death may also occur.
Diagnosis
- The key investigations are ECG and echocardiography; a normal ECG does not exclude the condition.
- BNP and NT-proBNP correlate with outcome; cardiac MRI measures chamber volumes and ventricular function more precisely and is mostly used postpartum because of gadolinium.
Treatment principles
- Management is interdisciplinary with cardiology and follows the principles of heart failure treatment, with drug classes adapted to pregnancy or breastfeeding.
- Anticoagulation is considered when ventricular function is severely reduced, and prolactin suppression may be considered as an additional measure; severe cases require intensive care, up to mechanical circulatory support.
- The timing and mode of delivery depend on the maternal and fetal condition; cardiology counselling is important before any further pregnancy.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Birth & puerperium
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Retained placenta · Postpartum haemorrhage (uterine atony) · Postpartum depression and postpartum psychosis
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.