Retained placenta
Exam relevance: in 4 of more than 150 board exam reports · rank 111
- Specialty
- Obstetrics · Birth & puerperium
- Images
- Ultrasound 2
- Exam relevance
- 4 of more than 150 reports · rank 111
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
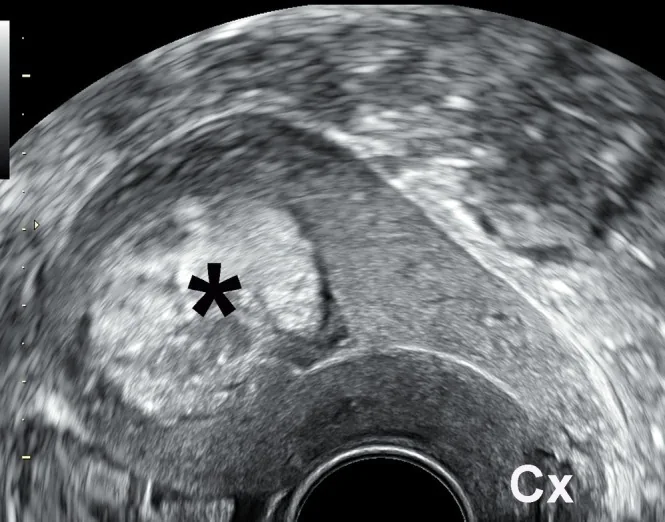 Ultrasound
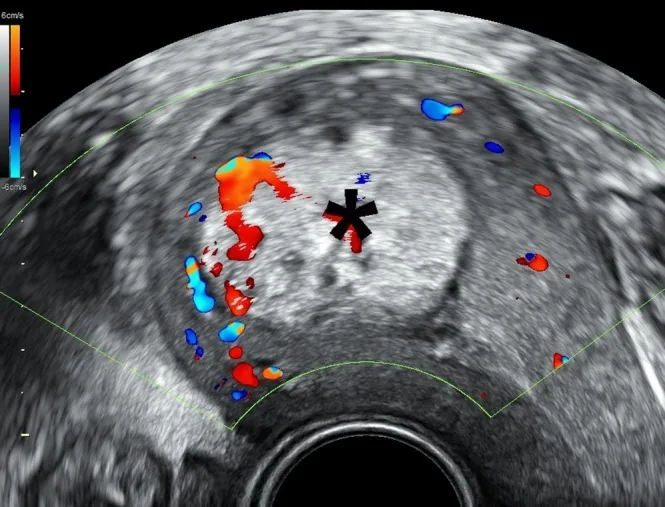 Ultrasound
Definition
- Retained placenta is present when the placenta has not been born more than 30 minutes after the birth of the baby; however, there is no internationally agreed definition.
- The third stage of labour is the period between the birth of the baby and the birth of the placenta.
Occurrence & epidemiology
Epidemiology
- Retained placenta affects about 0.5–3% of all vaginal births; in a systematic review reported rates ranged from 0.5% to 4.8%.
Aetiopathogenesis
Aetiology and risk factors
- An important cause is placenta accreta spectrum, in which the chorionic villi are not contained by decidua but attach to the myometrium (accreta), invade it (increta) or penetrate it to the serosa (percreta).
Clinical features
Signs of placental separation
- The Ahlfeld sign describes descent of the cord clamp by approx. 10 cm.
- The Schröder sign means a narrower fundus rising to the upper right.
Retained placenta
- Uterine inversion threatens with traction on an unseparated placenta.
Clinical features and complications
- Retained placenta is an important cause of primary and secondary postpartum haemorrhage and increases maternal morbidity and mortality.
- In placenta accreta, bleeding before separation may be minimal or absent; attempts at separation typically cause massive haemorrhage.
Diagnosis
- The diagnosis is clinical when the placenta has not been born 30 minutes after the baby; placenta accreta is suspected when no plane of separation can be created and traction on the placenta causes heavy bleeding.
- In women at risk, placenta accreta spectrum can be recognised antenatally on ultrasound at the uteroplacental interface, supplemented by MRI or Doppler if findings are inconclusive.
Treatment principles
- Conservative measures come first: uterotonics, emptying the bladder, putting the baby to the breast and controlled cord traction.
- Before any manipulation, signs of the placenta accreta spectrum are looked for.
- If the placenta does not separate or significant bleeding occurs, manual removal under anaesthesia is performed and completeness is checked; retained placental tissue is removed because it causes postpartum haemorrhage and infection.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Birth & puerperium
Keep learning: test yourself
One question from the GynFuchs app on Retained placenta – tap an answer.
Question 1 of 1
A 32-year-old secundigravida is in the delivery room 25 minutes after the birth of her child with an unseparated placenta. Is this statement true? “Schröder's sign is a fundus that rises upwards to the right and becomes narrower.”
Answer
Correct: True. Schröder's sign is one of the clinical signs of placental separation. It describes the contraction and ascent of the uterus after placental separation.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.