Intrahepatic cholestasis of pregnancy
Exam relevance: in 2 of more than 150 board exam reports · rank 144
- Synonyms
- obstetric cholestasis, ICP, itching in pregnancy
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Clinical 1
- Exam relevance
- 2 of more than 150 reports · rank 144
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
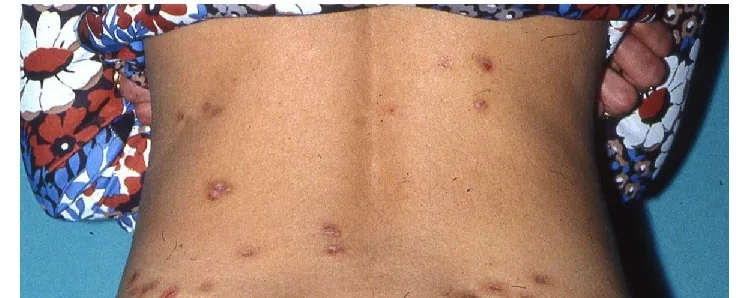
Definition
- Intrahepatic cholestasis of pregnancy is the commonest pregnancy-specific liver disease; it presents with new-onset pruritus and raised serum bile acids in the second or third trimester, usually after 30 weeks.
- The clinical signs resolve rapidly after birth.
Occurrence & epidemiology
Epidemiology
- Frequency varies greatly by ethnicity and region: in Europe, North America and Australia about 1–2% of pregnant women are affected, among Andean natives up to 25%; it is highest in Bolivia and Chile.
- It recurs in 45–90% of subsequent pregnancies, often in a more severe form.
Aetiopathogenesis
Aetiology and risk factors
- The aetiology is multifactorial: oestrogen and progesterone levels, which rise until the third trimester, exaggerate physiological bile stasis, and genetic factors such as mutations of hepatobiliary transport proteins (MDR3, BSEP) contribute.
Clinical features
Clinical features and complications
- The leading symptom is intense itching, mostly of the palms and soles and worse at night, but not confined to these areas; pain and systemic symptoms are absent, and mild jaundice follows in about 10–15%.
- Fetal and neonatal risks include stillbirth, preterm birth, asphyxia, respiratory distress syndrome and meconium-stained fluid; the maternal risk of pre-eclampsia is increased.
Diagnosis
- The most important and most sensitive laboratory marker is total serum bile acids; the cut-off is a concentration above 10 µmol/L, and bile acids may be the first or only abnormal laboratory finding.
- From 40 µmol/L the risk of fetal complications rises; in a large analysis the stillbirth rate at levels of 100 µmol/L or more was 3.44%.
- Transaminases are often raised as well.
Treatment principles
- Bile acid-modifying drug therapy can relieve pruritus somewhat but, according to large trials, does not reduce adverse perinatal outcomes; symptomatic skin care is a useful addition.
- Bile acids and liver function tests are monitored regularly, and fetal surveillance is intensified.
- The timing of delivery depends on bile acid levels and the overall situation, as the risk of stillbirth rises in severe disease; the condition resolves after birth, which is confirmed by repeat liver function tests.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Intrauterine fetal death (stillbirth) · Listeriosis in pregnancy · Multiple pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.