Antepartum haemorrhage
Exam relevance: in 2 of more than 150 board exam reports · rank 144
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Ultrasound 2
- Exam relevance
- 2 of more than 150 reports · rank 144
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
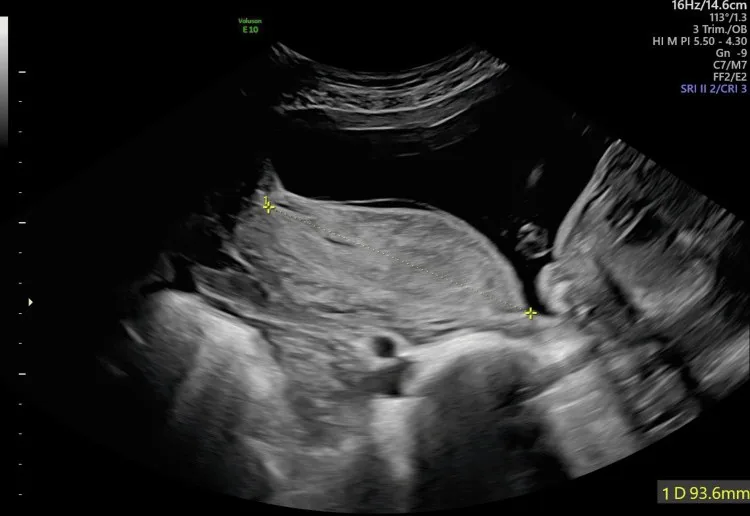 Ultrasound
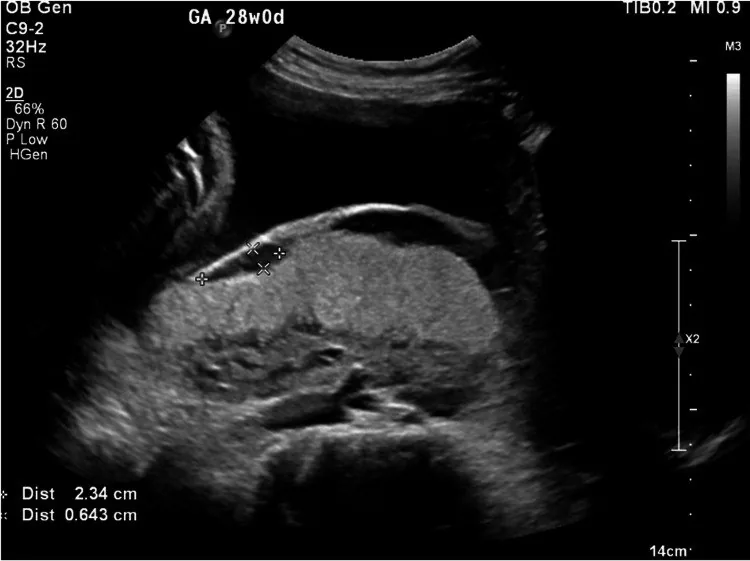 Ultrasound
Definition
- Antepartum haemorrhage is vaginal bleeding in late pregnancy from 20 weeks of gestation but before the birth of the baby.
Occurrence & epidemiology
Epidemiology
- It occurs in 3–4% of pregnancies; placental abruption, at about 30%, is the commonest life-threatening cause, and placenta praevia accounts for about 20%.
Aetiopathogenesis
Aetiology and risk factors
- The commonest cause is the bloody show at the onset of labour; more serious, less common causes are placental abruption, placenta praevia, vasa praevia and uterine rupture.
Clinical features
Clinical features and complications
- Placenta praevia typically bleeds suddenly and painlessly with bright red blood and little or no uterine tenderness.
- In abruption the uterus is painful, tender and often tense; the blood is dark, clotted or bright red, and signs of fetal compromise such as bradycardia, late decelerations or a sinusoidal pattern may occur.
- Because part of the bleeding may be concealed between placenta and uterine wall, visible bleeding does not reliably reflect blood loss; haemorrhagic shock and disseminated intravascular coagulation may occur.
- In vasa praevia the blood is fetal, so even a small blood loss can cause fetal death.
Diagnosis
- Every bleed in late pregnancy requires pelvic ultrasound; normal placental position and normal cord insertion exclude placenta praevia and vasa praevia.
- Placental abruption cannot be reliably shown on ultrasound and is diagnosed clinically.
Treatment principles
- Before any digital vaginal examination, placenta praevia is excluded by ultrasound, and the source of bleeding is further narrowed down by speculum examination.
- Management depends on the cause, severity of bleeding, maternal and fetal condition and gestational age; it includes inpatient monitoring, cross-matching, availability of blood products and rhesus prophylaxis in rhesus-negative women.
- Life-threatening bleeding or fetal compromise requires prompt delivery, usually by caesarean section.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Pregnancy disorders
- Rhesus incompatibility and fetal anaemia
- Rubella in pregnancy
- Thyroid disorders in pregnancy
- Selective fetal growth restriction in twins (sFGR)
- Syphilis in gynaecology and pregnancy
- TAPS and TRAP sequence
- Post-term pregnancy
- Thrombocytopenia in pregnancy
- Toxoplasmosis in pregnancy
- Triple I (intra-amniotic infection)
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Rhesus incompatibility and fetal anaemia · Rubella in pregnancy · Thyroid disorders in pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.