Thyroid disorders in pregnancy
Exam relevance: in 3 of more than 150 board exam reports · rank 125
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Ultrasound 1
- Exam relevance
- 3 of more than 150 reports · rank 125
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
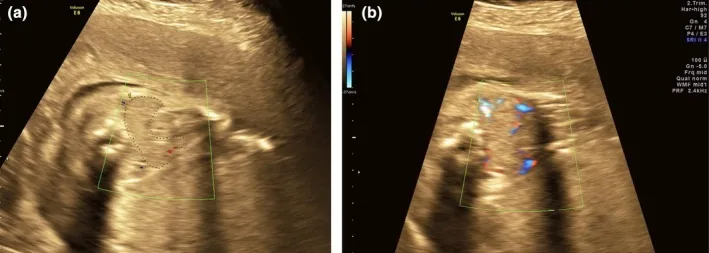 Ultrasound
Definition
- Thyroid disorders in pregnancy comprise hypothyroidism, hyperthyroidism and thyroid autoimmunity; after diabetes, they are the most common endocrine disorders of pregnancy.
Classification
- Transient gestational thyrotoxicosis results from direct hCG stimulation of the thyroid, usually in the first trimester, including in hyperemesis gravidarum or multiple pregnancy.
Aetiopathogenesis
Aetiology and pathogenesis
- hCG has weak TSH receptor-stimulating activity; with the hCG peak at 10–12 weeks of gestation, TSH may be reduced in the first trimester.
- By 6–8 weeks of gestation, thyroxine-binding globulin rises by about 50%, with a corresponding rise in total T4 and T3; iodine requirements increase.
- The commonest cause of hypothyroidism is chronic autoimmune (Hashimoto's) thyroiditis, and the commonest cause of overt hyperthyroidism, at 85%, is Graves' disease.
Clinical features
Clinical features and complications
- Overt hypothyroidism is associated with preterm birth, low birthweight, perinatal death, pre-eclampsia, placental abruption and anaemia.
- TSH receptor antibodies can cross the placenta and stimulate the fetal thyroid at high concentrations; fetal hyperthyroidism is rare, at 1 in 4,000–40,000 pregnancies.
Diagnosis
- Overt hypothyroidism is defined as TSH above the trimester-specific range with low fT4.
- TSH receptor antibodies have high sensitivity and specificity for Graves' disease.
- Ultrasound features suggestive of fetal thyroid dysfunction are goitre, growth restriction, hydrops, tachycardia or heart failure.
Treatment principles
- Overt hypothyroidism is treated with thyroid hormone replacement; as requirements rise during pregnancy, the dose is adjusted based on regular blood tests.
- Overt hyperthyroidism, usually due to Graves' disease, is treated with antithyroid drugs at the lowest effective dose, with the choice of agent depending on the trimester; radioiodine is contraindicated, and transient gestational hyperthyroidism usually needs no antithyroid treatment.
- In Graves' disease, the fetus is monitored because of antibodies crossing the placenta; after birth, postpartum thyroiditis should be considered.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Pregnancy disorders
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Selective fetal growth restriction in twins (sFGR) · Syphilis in gynaecology and pregnancy · TAPS and TRAP sequence
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.