Occult stress urinary incontinence
Exam relevance: in 6 of more than 150 board exam reports · rank 93
- Specialty
- Gynaecology · Pelvic floor & urogynaecology
- Images
- Clinical 1
- Exam relevance
- 6 of more than 150 reports · rank 93
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
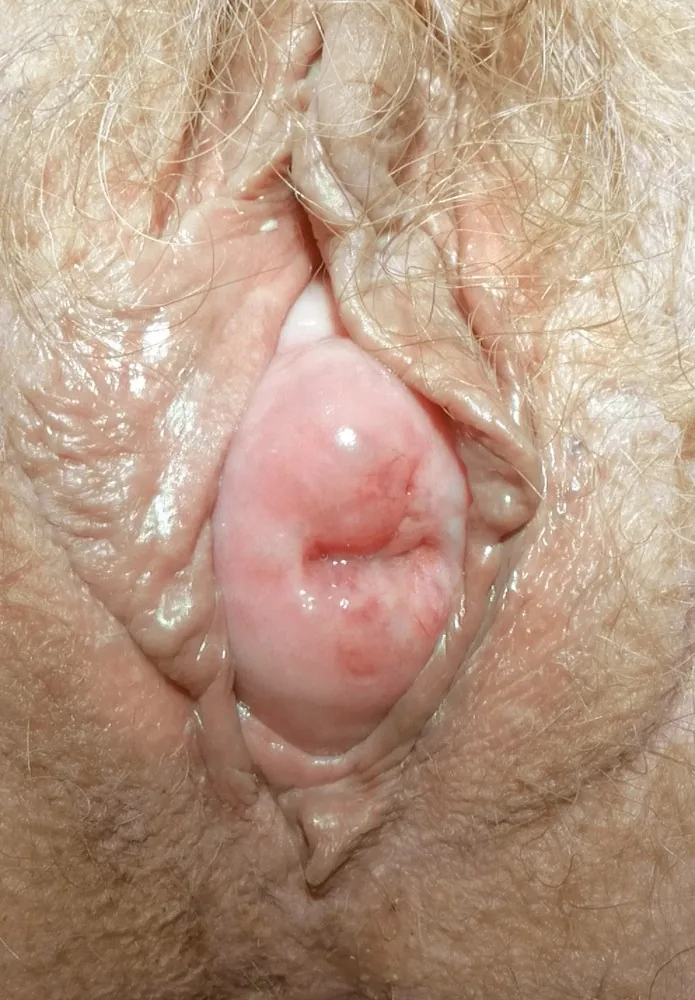
Definition
Definition and mechanism
- Definition: stress incontinence that only becomes apparent after the prolapse is corrected.
- The mechanism is called: the kinking or pinchcock phenomenon — the cystocele kinks and occludes the urethra.
- This is why some patients report: residual urine and difficulty voiding instead of urine loss.
- Stress incontinence that is concealed by prolapse and becomes apparent only after the prolapse is reduced (occult stress incontinence).
Occurrence & epidemiology
Epidemiology
- The reported incidence of occult stress incontinence ranges from 8% to 57%, reflecting the lack of standardised diagnostic criteria.
Aetiopathogenesis
Aetiology and pathogenesis
- Stress incontinence and prolapse frequently coexist because of shared pathophysiological mechanisms; the main risk factors for stress incontinence are pregnancy and advanced age.
- Traditionally, the descending bladder base is thought to kink or compress the urethra and thus mask the incontinence; this interpretation is now also being questioned.
- Stress incontinence is more common in mild to moderate prolapse, whereas voiding dysfunction predominates in moderate to severe prolapse.
Clinical features
- Prolapse symptoms predominate, such as pelvic pressure, a felt or visible vaginal bulge and difficulty with urination or defecation, while leakage on exertion may be absent.
Diagnosis
How to Unmask It Beforehand
- Elevation test: the prolapse is reduced and the patient is then checked for urine leakage upon coughing.
- In case of unclear findings: urodynamics with reduction of the prolapse.
- Occult incontinence is demonstrated by a cough stress test with the prolapse reduced, for example with a speculum, at a bladder volume of at least 200 ml.
- The maximum extent of prolapse, by contrast, is assessed with an empty bladder; a post-void residual above 100 ml is taken as a sign of voiding difficulty.
Treatment principles
- Before prolapse surgery, stress incontinence is specifically tested with the prolapse reduced.
- If occult incontinence is demonstrated, the decision whether to perform continence surgery at the same time or as a staged procedure after assessing the result of prolapse repair is made after counselling on benefits and risks.
- Pelvic floor training is a useful adjunct.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
- Is occult stress urinary incontinence truly "occult"?
- International Urogynecology consultation chapter 2 committee 3: the clinical evaluation of pelvic organ prolapse including investigations into associated morbidity/pelvic floor dysfunction
- StatPearls: Pelvic Organ Prolapse (NCBI Bookshelf)
- DocCheck Flexikon, Belastungsinkontinenz
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Rectocele and enterocele · Overflow incontinence · Urogenital fistulas (vesicovaginal fistula)
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.