Diabetic fetopathy and neonatal hypoglycaemia
Exam relevance: in 1 of more than 150 board exam reports · rank 171
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Ultrasound 1 · Histology & cytology 1
- Exam relevance
- 1 of more than 150 reports · rank 171
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (2)
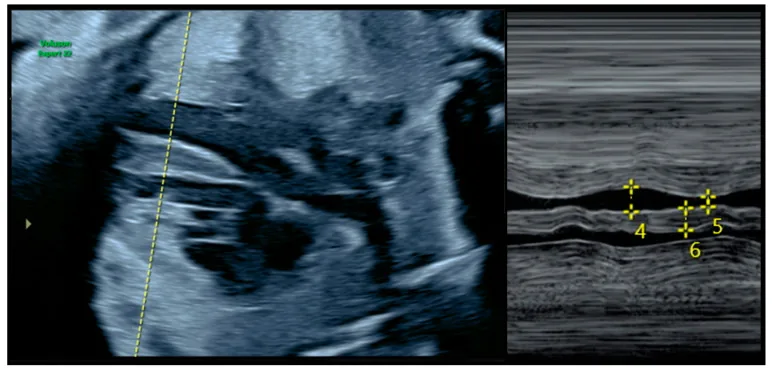 Ultrasound
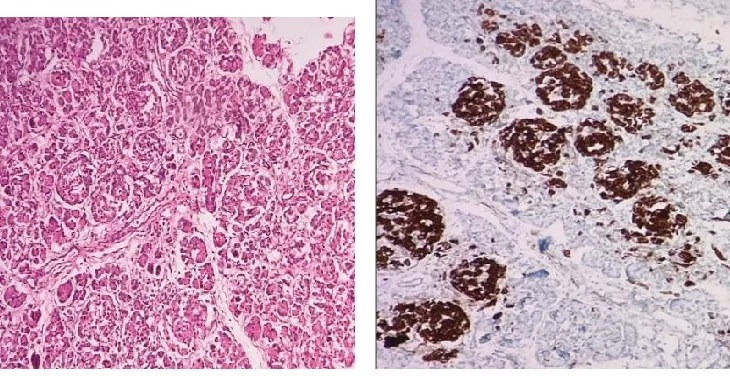 Histology & cytology
Definition
- Diabetic fetopathy denotes the changes in infants of diabetic mothers, the term diabetic mother covering both pre-existing type 1 or type 2 diabetes and gestational diabetes.
- Neonatal hypoglycaemia is the most common metabolic disturbance of the newborn period; the glucose level at which brain damage occurs is unknown.
Occurrence & epidemiology
Epidemiology
- Hypoglycaemia occurs in 5–27% of infants of diabetic mothers; further risk groups are preterm infants and infants small or large for gestational age.
Aetiopathogenesis
Aetiology and pathogenesis
- Increased fetal insulin secretion leads to hypertrophy and hyperplasia of the β cells and to growth of insulin-dependent organs such as liver, kidneys, skeletal muscle and heart (organomegaly).
- After cord clamping the glucose supply ends while insulin levels remain high; blood glucose reaches its lowest point between the first and third hour of life.
- Insulin antagonises cortisol, which stimulates surfactant synthesis; this results in an increased risk of respiratory distress syndrome.
Clinical features
Main problem: Postnatal hypoglycaemia
- The main problem for the newborn is postnatal hypoglycaemia, as fetal hyperinsulinism with absent glucose supply.
Other transitional problems and findings
- Respiratory distress syndrome can be caused by reduced surfactant formation.
- A typically reversible myocardial hypertrophy due to glycogen deposition is a typical cardiac finding.
- Other findings include polycythaemia with an elevated haematocrit and consecutive hyperbilirubinemia, as well as hypocalcaemia and hypomagnesaemia.
Clinical features and complications
- Macrosomic infants (birthweight above the 90th centile) have a chest circumference exceeding head circumference and organomegaly; they more often suffer brachial plexus injury, clavicular fracture and asphyxia.
- Hypoglycaemic newborns usually show tremors and hyperalertness, but also hypotonia, lethargy and weak sucking; however, hypoglycaemia is mostly asymptomatic and may persist for up to 72 hours.
Treatment principles
- Prevention through good maternal glycaemic control before and during pregnancy is crucial.
- In insulin-treated diabetes, delivery takes place in a perinatal centre with neonatology, taking macrosomia and the risk of shoulder dystocia into account.
- After birth, early blood glucose monitoring of the newborn is performed, with early feeding and, if necessary, intravenous glucose to treat hypoglycaemia.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Threatened preterm birth · Eclampsia · Epilepsy in pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.