Fetal macrosomia
Exam relevance: in 17 of more than 150 board exam reports · rank 39
- Synonyms
- big baby, LGA, macrosomia
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Clinical 1
- Exam relevance
- 17 of more than 150 reports · rank 39
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
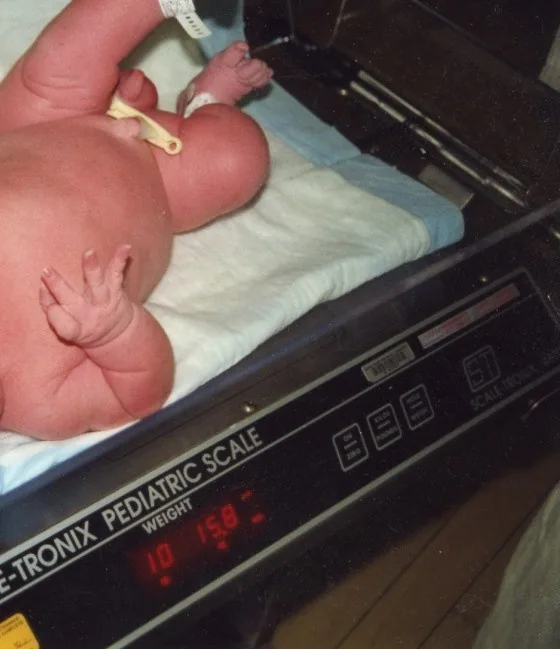
Definition
- Fetal macrosomia denotes excessive fetal growth, defined by an absolute birth weight irrespective of gestational age; thresholds of 4000 g or 4500 g are used, and there is no universal definition.
- It is distinguished from LGA (large for gestational age), a birth weight at or above the 90th centile for gestational age.
Classification
- Risks rise with weight: between 4000 and 4499 g complications increase moderately, above 4500 g steeply, and they are highest above 5000 g.
Occurrence & epidemiology
Epidemiology
- In a meta-analysis, 15.8% of obese mothers but only 9.3% of underweight or normal-weight mothers gave birth to a baby weighing at least 4000 g.
Aetiopathogenesis
Aetiology and risk factors
- Apart from genetically determined size, maternal diabetes is the most important cause: maternal hyperglycaemia leads to high fetal insulin levels, which have anabolic effects; the poorer the metabolic control, the larger the fetus.
- Maternal obesity also contributes; in the meta-analysis mentioned, the unadjusted odds ratio for a birth weight of 4000 g or more was 2.17.
- Rare causes are syndromes such as Beckwith-Wiedemann, Sotos, Marshall and Weaver syndromes.
Clinical features
Clinical features and complications
- Birth may be difficult; typical birth injuries are shoulder dystocia, fractures of the clavicle or limbs and perinatal asphyxia, and brachial plexus injury and stillbirth rise steeply above 4500 g.
- Neonates more often have respiratory distress, meconium aspiration, hypoglycaemia and polycythaemia; infants of diabetic mothers are additionally at risk of hypocalcaemia, hypomagnesaemia, hyperbilirubinaemia, respiratory distress syndrome and certain congenital anomalies.
- The neonates appear large and plethoric, and the 5-minute Apgar score may be low.
Diagnosis
- Antenatal prediction is difficult; birth weight is decisive.
- Sonographic weight estimation becomes less accurate as weight increases; for birth weights above 4500 g its sensitivity is only 33–44%.
- Abdominal palpation is also unreliable, and maternal obesity further hampers assessment.
Treatment principles
- In maternal diabetes, optimising glycaemic control is the priority.
- Birth planning takes into account the risk of shoulder dystocia and the limited accuracy of fetal weight estimation; induction may be considered, and with a very high estimated weight, particularly in diabetes, elective caesarean section is offered.
- During labour, the team must be prepared for shoulder dystocia.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Pregnancy disorders
- Fetal growth restriction (FGR)
- Twin-to-twin transfusion syndrome (TTTS)
- Gestational diabetes mellitus (GDM)
- Gestational hypertension
- Urinary tract infections in pregnancy
- HELLP syndrome
- Hepatitis B in pregnancy
- HIV in pregnancy
- Velamentous cord insertion and umbilical cord anomalies
- Intrahepatic cholestasis of pregnancy
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Fetal growth restriction (FGR) · Twin-to-twin transfusion syndrome (TTTS) · Gestational diabetes mellitus (GDM)
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.