Gestational hypertension
Exam relevance: in 8 of more than 150 board exam reports · rank 82
- Synonyms
- pregnancy-induced hypertension, PIH
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Histology & cytology 1
- Exam relevance
- 8 of more than 150 reports · rank 82
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
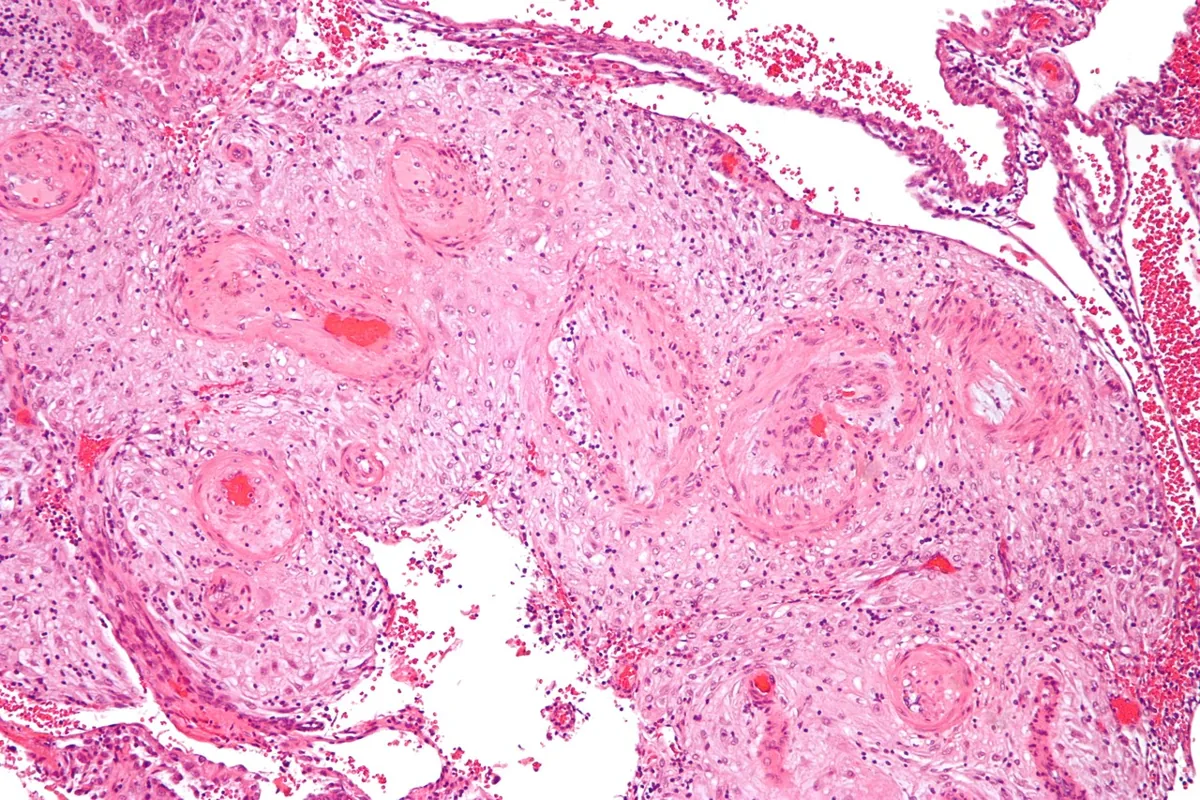 Histology & cytology
Definition
Chronic vs. gestational hypertension
- Chronic hypertension is either known to be pre-existing or is first diagnosed before 20+0 weeks and persists after the pregnancy.
- Gestational hypertension (formerly pregnancy-induced hypertension or PIH) newly occurs from 20+0 weeks onwards and is characterised by the absence of proteinuria and end-organ damage.
- Gestational hypertension typically resolves within 12 weeks postpartum.
- Gestational hypertension is new-onset hypertension after 20 weeks (at least 140 mmHg systolic and/or 90 mmHg diastolic on at least two measurements at least 4 hours apart) without criteria of pre-eclampsia; it resolves by 6 weeks after birth.
Classification
- It is distinguished from chronic hypertension, which is present before pregnancy or before 20 weeks.
- Pre-eclampsia is present when hypertension after 20 weeks is accompanied by new unexplained proteinuria and/or signs of end-organ damage.
Occurrence & epidemiology
Epidemiology
- Gestational hypertension occurs in about 5–10% of pregnancies, more often in multiple pregnancy, and usually only after 37 weeks.
Aetiopathogenesis
Aetiology and pathogenesis
- Gestational hypertension increases the risk of pre-eclampsia and eclampsia and of other severe complications such as HELLP syndrome, hypertensive encephalopathy and stroke.
- Risk factors for pre-eclampsia include previous pre-eclampsia, multiple pregnancy, renal and autoimmune disease, diabetes mellitus, chronic hypertension, first pregnancy, age 35 years or older and a pre-pregnancy BMI above 30.
Clinical features
Clinical features and complications
- Signs of severe pre-eclampsia include severe headache, visual disturbances, confusion, right upper quadrant or epigastric pain, nausea, dyspnoea and oliguria; oedema of the face and hands is more specific than dependent oedema.
- Reduced uteroplacental blood flow increases the risk of fetal growth restriction, hypoxia and placental abruption.
Diagnosis
- Blood pressure is measured at every antenatal visit; values of 160 mmHg systolic and/or 110 mmHg diastolic or more are regarded as severe.
- Pre-eclampsia is distinguished by detection of proteinuria (for example a protein/creatinine ratio of 0.3 or more) and by platelets, transaminases and creatinine.
Treatment principles
- Gestational hypertension without proteinuria, symptoms or fetal abnormalities can be managed as an outpatient with monitoring of blood pressure, urine and growth, provided adherence is good.
- Severe hypertension is treated with antihypertensives compatible with pregnancy and, like symptoms, fetal growth restriction or abnormal Doppler findings, is an indication for admission.
- Because of possible progression to pre-eclampsia, the timing of delivery is determined by maternal and fetal condition.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
- Hypertensive Disorders in Pregnancy (HDP): Diagnostics and Therapy. Guideline of the DGGG, OEGGG and SGGG (S2k-Level, AWMF Registry No. 015/018, June 2024)
- MSD Manual Professional Edition: Hypertension in Pregnancy
- MSD Manual Professional Edition: Preeclampsia and Eclampsia
- DocCheck Flexikon, Schwangerschaftsinduzierte Hypertonie
Cross-references
More topics: Pregnancy disorders
Keep learning: test yourself
One question from the GynFuchs app on Gestational hypertension – tap an answer.
Question 1 of 1
Chronic vs. gestational hypertension: Gestational hypertension typically resolves _____.
Answer
Correct: within 12 weeks postpartum. Gestational hypertension typically resolves within 12 weeks postpartum.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.