Threatened preterm birth
Exam relevance: in 45 of more than 150 board exam reports · rank 7
- Synonyms
- preterm birth, premature birth, preterm labour
- Specialty
- Obstetrics · Pregnancy disorders
- Images
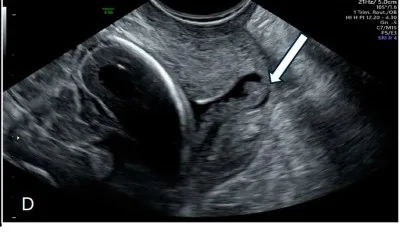
- Ultrasound 1
- Exam relevance
- 45 of more than 150 reports · rank 7
- In the app
- 2 flashcards · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
- Preterm birth is any birth before completion of 37+0 weeks.
- Very preterm means before 32+0 weeks, extremely preterm before 28+0 weeks.
- In Germany the preterm birth rate is about 8–9% of all pregnancies.
- Preterm birth is main cause of neonatal morbidity/mortality.
Aetiopathogenesis
Risk factors
- The strongest factor in the history is history of preterm birth or late miscarriage.
- Further factors are multiples, uterine anomalies, smoking.
Clinical features
More facts from the study questions
- Strict bed rest increases the risk of thrombosis in pregnancy.
- Urinary tract infections are a risk factor for preterm birth.
- The strongest anamnestic factor for preterm birth is a history of preterm birth or late miscarriage.
- Preterm birth is the most important cause of morbidity and mortality in neonates without malformations.
- The preterm birth rate in Germany is approximately 8 to 9 percent.
- Poor dental health with periodontitis is an often overlooked risk factor for preterm birth.
- The PROM test (Actim) detects IGFBP-1 (insulin-like growth factor-binding protein-1).
- The Partosure test (and AmniSure) detects PAMG-1.
- Partosure is a test for the detection of placental alpha-microglobulin-1 (PAMG-1).
- PAMG-1 is found in high concentrations in amniotic fluid.
Diagnosis
Three tests
- The fetal fibronectin (fFN) test detects fetal fibronectin in cervicovaginal fluid.
- PartoSure measures placental alpha microglobulin-1 (PAMG-1).
- The Actim PROM test rests on IGF-binding protein-1 (IGFBP-1).
Treatment principles
- In threatened preterm labour, short-term tocolysis aims to gain time for antenatal corticosteroids and transfer to a perinatal centre of the appropriate level.
- Depending on the situation, fetal neuroprotection, antibiotics after preterm prelabour rupture of membranes and, for prevention, vaginal progestogens or cerclage in cervical shortening are added; symptomatic bacterial vaginosis is treated.
- In multiple pregnancies, the benefit of such preventive measures is not adequately established; close monitoring and education about signs of preterm labour are the priorities.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning: test yourself
One question from the GynFuchs app on Threatened preterm birth – tap an answer.
Question 1 of 1
A 32-year-old G3 P1 presents at 26+3 weeks' gestation with preterm contractions and cervical shortening. Is this statement true? “The strongest anamnestic risk factor is a previous preterm birth.”
Answer
Correct: True. The strongest anamnestic factor for preterm birth is a history of preterm birth or late miscarriage. This requires closer monitoring, e.g. with cervical length measurements.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.