Gestational diabetes mellitus (GDM)
Exam relevance: in 38 of more than 150 board exam reports · rank 15
- Synonyms
- gestational diabetes, GDM, pregnancy diabetes
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Histology & cytology 1
- Exam relevance
- 38 of more than 150 reports · rank 15
- In the app
- 3 flashcards · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
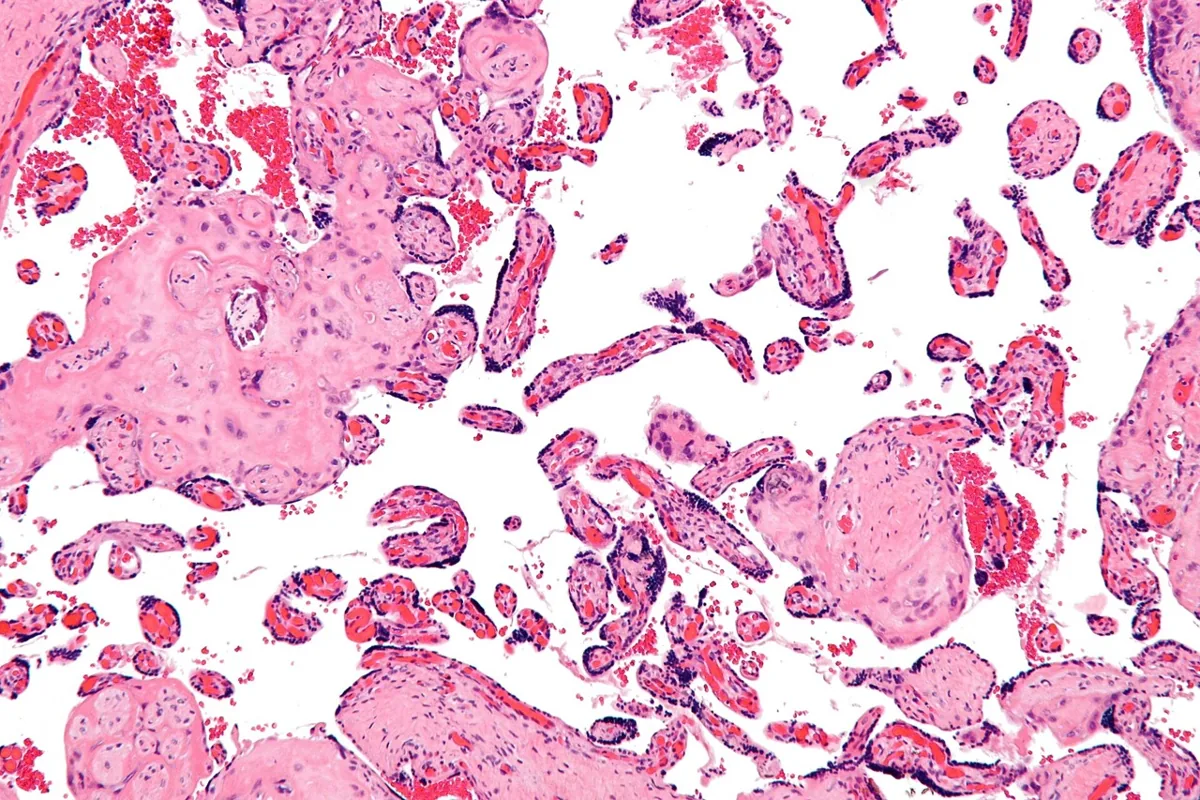 Histology & cytology
Aetiopathogenesis
Physiological basis and development
- During pregnancy, insulin resistance physiologically increases, driven by hPL, progesterone, oestrogens, cortisol, prolactin.
- This resistance begins to increase from around 20 weeks and reaches its peak at around 32 weeks of gestation.
- Gestational diabetes develops when maternal insulin secretion can no longer compensate for this resistance, which first manifests postprandial hyperglycaemia.
Pedersen hypothesis and foetal consequences
- According to the Pedersen hypothesis, glucose crosses the placenta but maternal insulin does not, leading to foetal hyperglycaemia and, reactively, to hyperinsulinism.
- In the foetus, insulin acts as a growth factor, causing a typically disproportionate macrosomia with truncal adiposity.
- Characteristically, the trunk, abdomen and shoulder girdle grow more than the head, which increases the risk of shoulder dystocia.
Obesity risk complex
- Even before pregnancy, obesity increases the risk of infertility and miscarriages.
- During pregnancy, obesity increases the risk of pre-eclampsia, intrauterine foetal death and foetal macrosomia.
Clinical features
Further foetopathic complications
- Polyhydramnios can be caused by osmotically induced foetal polyuria.
- Other consequences of hyperinsulinism include myocardial hypertrophy, delayed surfactant production and polycythaemia with hyperbilirubinaemia.
- The risk of intrauterine foetal death increases due to heightened foetal oxygen consumption with relative hypoxia, acidosis and electrolyte shifts with arrhythmias.
Clinical signs during the course of pregnancy
- A clinical sign of undiagnosed gestational diabetes can be polyhydramnios.
- During the external examination, an important measurement is the symphysis-fundal height (SFH), especially if it increases rapidly.
- On ultrasound, a foetal abdominal circumference > 90th percentile is a clear warning sign.
More facts from the study questions
- Insulin resistance physiologically increases during pregnancy.
- It begins to rise from around 20 weeks' gestation and peaks around 32 weeks' gestation.
- Foetal hyperinsulinism acts as a growth factor and leads to disproportionate macrosomia.
- Growth of the trunk, abdomen and shoulder girdle is characteristically greater than that of the head.
- Foetal hyperglycaemia leads to osmotic diuresis.
- The resulting foetal polyuria is a typical cause of polyhydramnios.
- The increase in insulin resistance is driven by various placental and maternal hormones.
- These include human placental lactogen (hPL), progesterone, oestrogens, cortisol and prolactin.
- Severe malformations (embryopathy) are caused by hyperglycaemia during early organogenesis.
- This is typical of poorly controlled diabetes existing before conception.
Diagnosis
Preparation and procedure
- The test is performed in the morning on a fasting patient, after at least an eight-hour fast and after three days of a normal high-carbohydrate diet.
- The blood glucose measurement is taken from fluoride-inhibited venous plasma.
Cut-offs and diagnosis
- For a diagnosis of gestational diabetes, it is sufficient if a single value is met or exceeded.
- Pre-analytics play a crucial role: without glycolysis inhibition or immediate centrifugation, the values will be falsely low.
Treatment principles
- The basis is dietary change with physical activity and blood glucose self-monitoring; if targets are not achieved, drug therapy is started, primarily insulin therapy.
- Care is interdisciplinary, with closer monitoring of growth, blood pressure and urine when insulin is required, because of the increased risk of pre-eclampsia.
- In medication-treated gestational diabetes, birth is planned in a hospital with neonatology and around term without going past the due date, as the newborn is at risk of hypoglycaemia; a glucose tolerance test is recommended 6 to 12 weeks after delivery.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Pregnancy disorders
Keep learning: test yourself
Two questions from the GynFuchs app on Gestational diabetes mellitus (GDM) – tap an answer.
Question 1 of 2
A 32-year-old G3 presents at 33 weeks' gestation with suspected gestational diabetes and macrosomia. Is this statement true? “Foetal hyperinsulinism leads to proportional macrosomia of the foetus.”
Answer
Correct: False. Foetal hyperinsulinism acts as a growth factor and leads to disproportionate macrosomia. Growth of the trunk, abdomen and shoulder girdle is characteristically greater than that of the head.
Question 2 of 2
A 32-year-old pregnant woman presents at 26 weeks of gestation for a 75-g oGTT. Is this statement true? “The threshold for blood glucose after two hours is a value of ≥ 180 mg/dl (10.0 mmol/l).”
Answer
Correct: False. The threshold after two hours is ≥ 153 mg/dl (8.5 mmol/l). The value of ≥ 180 mg/dl (10.0 mmol/l) is the threshold for the one-hour measurement.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.