Trisomy 18 and 13
Exam relevance: in 6 of more than 150 board exam reports · rank 93
- Specialty
- Obstetrics · Fetus & prenatal medicine
- Images
- Clinical 1
- Exam relevance
- 6 of more than 150 reports · rank 93
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
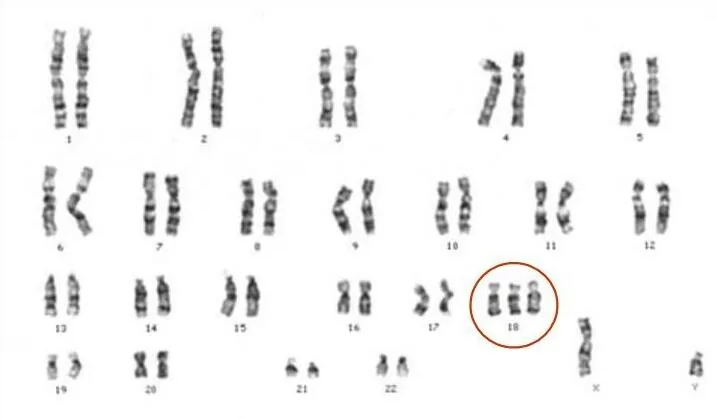
Definition
- Trisomy 18 (Edwards syndrome) and trisomy 13 (Patau syndrome) are aneuploidies with an extra copy of chromosome 18 or 13 and multiple malformations.
Occurrence & epidemiology
Epidemiology
- Trisomy 18 occurs in about 4.1 per 10,000 pregnancies and trisomy 13 in about 1.7 per 10,000 (each including terminations and stillbirths).
- In trisomy 13 the live birth prevalence is about 1 in 10,000 to 20,000 and antenatal mortality exceeds 95%; in trisomy 18 fewer than 10% survive the first year, and girls are affected three times as often as boys.
Aetiopathogenesis
Aetiology
- In trisomy 18 more than 95% have full trisomy; the extra chromosome is almost always maternal, risk increases with maternal age, and translocations are rare.
- In trisomy 13 full trisomy is the most common form at about 80%; partial forms mostly result from a Robertsonian translocation t(13;14), mosaicism accounts for about 5%, and about 91% are due to maternal meiotic non-disjunction.
Clinical features
- Prenatally, trisomy 18 typically shows polyhydramnios, a small placenta, a single umbilical artery and growth restriction; after birth, clenched fists with the index finger overlapping the third and fourth fingers, microcephaly, severe heart defects (especially patent ductus arteriosus and ventricular septal defect) and anomalies of the diaphragm, abdominal wall and kidneys.
- In trisomy 13 midline defects are typical, such as holoprosencephaly, cleft lip and palate, microphthalmia and iris colobomas; 57–80% have severe heart defects, and polydactyly and genital anomalies are also common.
Diagnosis
- Prenatal suspicion arises from ultrasound findings such as growth restriction, from serum markers or from analysis of cell-free fetal DNA in maternal blood, the latter being a screening test.
- The diagnosis is confirmed by karyotyping and/or chromosomal microarray analysis of material obtained by chorionic villus sampling or amniocentesis.
Treatment principles
- There is no causal treatment; after the diagnosis is confirmed, parents receive non-directive interdisciplinary counselling and are offered psychosocial support.
- If the parents decide to continue the pregnancy, birth is planned together with neonatology and palliative care, including which interventions during labour and for the newborn are appropriate.
- Burdensome interventions are limited to what is necessary, in agreement with the parents.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning: test yourself
One question from the GynFuchs app on Trisomy 18 and 13 – tap an answer.
Question 1 of 1
The result: Rapid test and karyogram: Typical ultrasound signs of trisomy 18, in addition to an omphalocele, include growth restriction, cardiac defects, and _____.
Answer
Correct: a typical hand position with overlapping fingers. Typical ultrasound signs of trisomy 18, in addition to an omphalocele, include growth restriction, cardiac defects, and a typical hand position with overlapping fingers.
More questions like these – with explanations and spaced repetition – in the app.
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.