Pre-existing diabetes in pregnancy
Exam relevance: in 2 of more than 150 board exam reports · rank 144
- Specialty
- Obstetrics · Pregnancy disorders
- Images
- Ultrasound 1
- Exam relevance
- 2 of more than 150 reports · rank 144
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
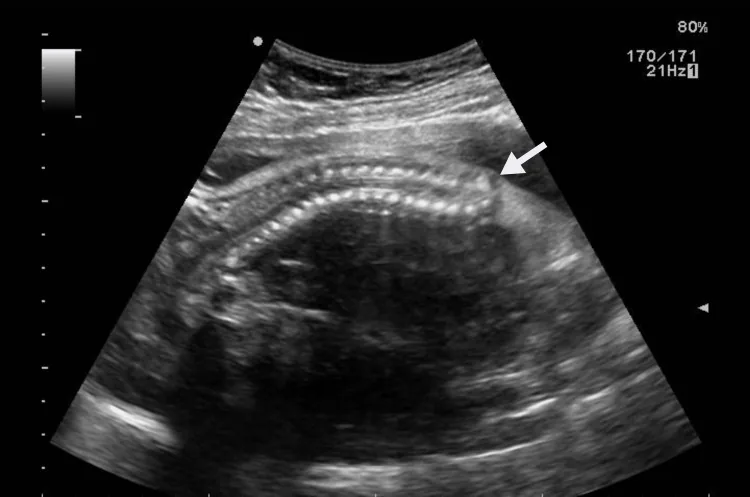 Ultrasound
Definition
- This denotes diabetes mellitus type 1 or type 2 present before pregnancy; it is the commonest cause of diabetic embryopathy.
- Diabetic embryopathy is the collective term for congenital malformations and secondary complications caused by maternal diabetes; poorly controlled gestational diabetes can also contribute if hyperglycaemia is present early in pregnancy.
Occurrence & epidemiology
Epidemiology
- The malformation rate is markedly higher than in the general population; in large meta-analyses it did not differ between type 1 and type 2 diabetes and was about 5–6% in each.
Aetiopathogenesis
Risks and pathophysiology
- Diabetic embryopathy develops during organogenesis (up to 8th week) and includes malformations such as neural tube defects, heart defects and caudal regression syndrome.
- In type 1 diabetes, there is an additional risk of ketoacidosis, which can occur even with moderately high glucose levels.
Aetiology and risk factors
- Maternal hyperglycaemia is teratogenic, especially during organogenesis up to about 10 weeks; proposed mechanisms include oxidative and hypoxic stress in the embryo.
- Higher glucose or HbA1c levels are associated with a higher risk of malformation.
- Genetic predisposition, obesity, hypertension and dyslipidaemia can compound the teratogenic effect.
Clinical features
Clinical features and complications
- Typical malformations are neural tube defects, heart defects (particularly outflow tract anomalies), craniofacial anomalies, limb deficiencies and caudal regression syndrome; poor control during organogenesis also raises the risk of miscarriage.
- Poor control later in pregnancy increases the risk of macrosomia, pre-eclampsia, shoulder dystocia and stillbirth; neonates are at risk of respiratory distress, hypoglycaemia, hypocalcaemia, hyperbilirubinaemia and polycythaemia.
- In the mother, diabetic retinopathy can progress during pregnancy; pregnancy is considered an independent risk factor. Contributing factors are pre-existing retinopathy, poor glycaemic control, long duration of diabetes, rapid normalisation of HbA1c in early pregnancy, hypertension and pre-eclampsia.
Diagnosis
- Prenatally, first-trimester ultrasound and fetal echocardiography allow early detection of malformations.
- Caudal regression syndrome with agenesis of the lower spine is regarded as particularly characteristic of maternal diabetes.
Treatment principles
- Preconception counselling with optimisation of glucose control and review of other medication is crucial, because poor control in early pregnancy increases the risk of malformations.
- During pregnancy, intensified insulin therapy with close metabolic monitoring is used; the retina and kidneys are checked, and the fetus is monitored with detailed ultrasound and growth scans.
- Delivery is planned in a perinatal centre with neonatology because the newborn is at risk of hypoglycaemia.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Pregnancy disorders
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Antepartum haemorrhage · Rhesus incompatibility and fetal anaemia · Rubella in pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.