Uterine rupture
Exam relevance: in 10 of more than 150 board exam reports · rank 66
- Specialty
- Obstetrics · Birth & puerperium
- Images
- Clinical 1
- Exam relevance
- 10 of more than 150 reports · rank 66
- In the app
- 2 flashcards · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
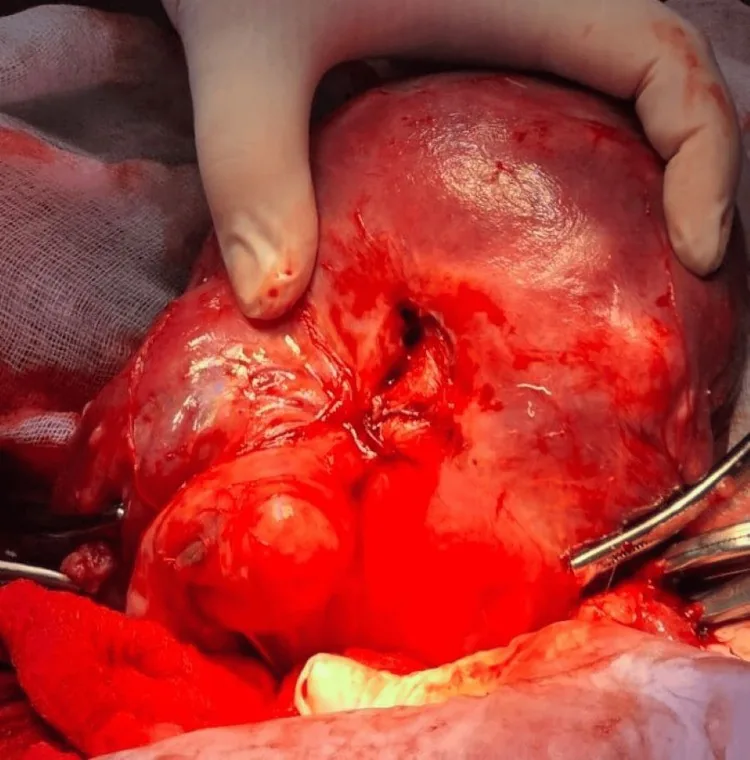
Definition
- Uterine rupture is complete division of all three layers of the uterine wall (endometrium, myometrium, perimetrium); it occurs in late pregnancy before or during labour.
- In dehiscence the wall is only incompletely divided, sometimes with a window through which the fetus can be seen; it is often an occult finding without symptoms.
Classification
Special forms
- Dehiscence of an old scar differs from complete rupture in that serosa intact, fetus in uterine cavity.
Occurrence & epidemiology
Epidemiology
- Uterine rupture is rare and occurs most often along a healed scar after previous caesarean section; it can, however, also occur in an unscarred uterus.
Aetiopathogenesis
Risk situation
- The rupture risk after one caesarean is approx. 0.5–1%.
- An epidural is allowed, but can mask the typical pain.
Risk constellations
- Remember: rupture is not confined to labour and can present as an acute abdomen outside contractions.
Aetiology and risk factors
- Further causes are uterine overdistension (multiple pregnancy, polyhydramnios, fetal anomalies), external or internal version, iatrogenic perforation, excessive use of uterotonics and unrecognised dystocia with strong contractions against a lower-segment restriction ring.
Clinical features
Signs
- The Bandl ring is a groove between corpus & lower segment.
- Often the CTG is the first sign — typically variable decelerations, prolonged bradycardia.
- Another sign is the ascent of the presenting part.
Signs
- Sudden severe pain and restlessness, a rising Bandl ring, cessation of contractions, vaginal bleeding, pathological CTG, circulatory instability.
- The Bandl ring is a visible and palpable constriction between the corpus and the overstretched lower segment.
- Another sign: the presenting part rises again as the baby passes into the abdominal cavity.
Clinical features and complications
- Signs are fetal bradycardia, variable decelerations, signs of hypovolaemia, loss of fetal station and severe or constant abdominal pain; the uterus may be atonic or abnormally shaped and tender.
- Vaginal bleeding may be slight despite major intra-abdominal haemorrhage; complications are maternal haemorrhage and bladder injury, and if the fetus lies in the peritoneal cavity, maternal and fetal morbidity and mortality rise considerably.
Diagnosis
- The working diagnosis is clinical, based on risk factors and examination findings; ultrasound cannot reliably distinguish rupture from placental abruption.
- Uterine rupture is confirmed at laparotomy.
Treatment principles
- Uterine rupture requires immediate emergency caesarean section or laparotomy; tocolysis is no substitute for surgery.
- In parallel, large-bore access, fluids, cross-matched blood and blood products are provided, and the anaesthetic and theatre teams are alerted.
- Intraoperatively, the extent and site of the rupture determine whether repair or hysterectomy is performed, and the bladder and ureters are assessed; hysterectomy is indicated for uncontrollable bleeding or a rupture that cannot be repaired.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Birth & puerperium
- Wound complications and niche after caesarean section
- Breech presentation
- Malposition and malpresentation of the fetal head
- Endomyometritis and puerperal fever
- Amniotic fluid embolism
- Labour arrest and prolonged labour
- Obstetric perineal injury
- Cephalopelvic disproportion
- Puerperal mastitis
- Meconium-stained amniotic fluid
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Wound complications and niche after caesarean section · Breech presentation · Malposition and malpresentation of the fetal head
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.