Hyperemesis gravidarum
Exam relevance: in 2 of more than 150 board exam reports · rank 144
- Synonyms
- severe morning sickness
- Specialty
- Obstetrics · Early pregnancy
- Images
- Mammography/MRI 1
- Exam relevance
- 2 of more than 150 reports · rank 144
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
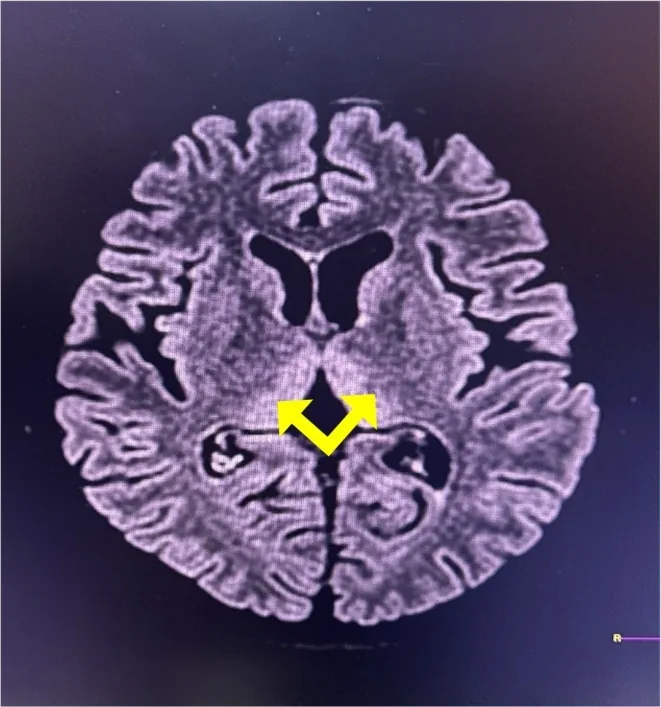
Definition
- Hyperemesis gravidarum is the severe end of the spectrum of nausea and vomiting of pregnancy and is characterised by persistent vomiting, significant weight loss (typically at least 5% of pre-pregnancy weight), dehydration and metabolic disturbances.
- The common, milder nausea of pregnancy, by contrast, peaks between 8 and 12 weeks of gestation and improves in the second trimester.
Occurrence & epidemiology
Epidemiology
- Nausea and vomiting affect the majority of pregnant women, on average about 70% according to one meta-analysis; reported frequencies of hyperemesis range from 0.3% to 10.8%.
- Nausea and vomiting usually begin at 6 to 8 weeks of gestation and resolve by 16 to 20 weeks; hyperemesis commonly recurs in subsequent pregnancies.
Aetiopathogenesis
Aetiology and risk factors
- The cause is not fully understood and is probably multifactorial; meta-analyses show an inconsistent association with hCG concentration.
- GDF15, produced in the early trophoblast and binding to receptors in the area postrema, is now regarded as a key factor; genome-wide studies identified risk loci containing GDF15 and IGFBP7.
- Risk factors include hyperemesis in a previous pregnancy, a positive family history, young maternal age, a female fetus, multiple and molar pregnancy, thyroid and parathyroid dysfunction, type 1 diabetes and Helicobacter pylori infection.
Clinical features
Clinical features and complications
- Affected women cannot eat and drink sufficiently, leading to weight loss and dehydration and severely impairing daily life.
- Complications include Wernicke encephalopathy due to vitamin B1 deficiency, coagulopathy due to vitamin K deficiency, acute liver and kidney failure, cardiac arrhythmias resulting from electrolyte disturbances and oesophageal rupture.
- In one prospective study, 57.4% of affected women met the criteria for depression or anxiety.
Diagnosis
- The diagnosis is clinical after exclusion of other causes and is supported by ketonuria, orthostatic hypotension and electrolyte disturbances.
- According to the international Windsor definition (2021), severe nausea or vomiting, inability to eat or drink normally, a strong impact on daily living and onset before 16 weeks are decisive; ketonuria is not required for the diagnosis.
- Ultrasound identifies multiple and molar pregnancy; some affected women develop self-limiting gestational transient thyrotoxicosis caused by hCG stimulation of the thyroid.
- Severity can be assessed with the PUQE score (up to 6 mild, 7 to 12 moderate, 13 or more severe).
Treatment principles
- Treatment is stepwise: dietary adjustment with small meals, then antiemetics; dehydration and ketonuria lead to inpatient intravenous fluid and electrolyte replacement.
- Before glucose infusions, vitamin deficiency is corrected to prevent Wernicke encephalopathy; thromboprophylaxis is considered during inpatient treatment.
- Other causes such as hyperthyroidism, multiple pregnancy or molar pregnancy are excluded, and psychosocial support is part of care.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Interstitial (cornual) pregnancy · Missed miscarriage · Ovarian pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.