Recurrent pregnancy loss
Exam relevance: in 4 of more than 150 board exam reports · rank 111
- Specialty
- Obstetrics · Early pregnancy
- Images
- Ultrasound 1
- Exam relevance
- 4 of more than 150 reports · rank 111
- In the app
- 1 flashcard · GynFuchs
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
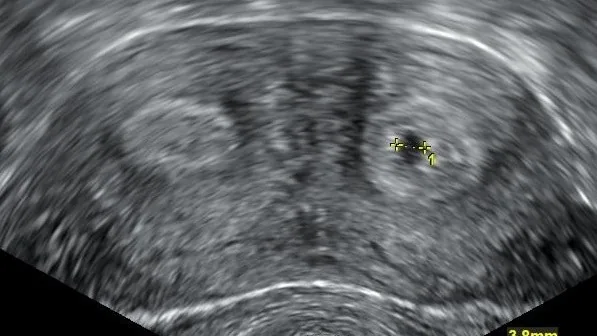
Definition
Definition and causes
- Common groups of causes include chromosomal, uterine, endocrine, immunological and thrombophilic and male factors.
- In about half of all couples, the cause remains without clear explanation despite a comprehensive work-up.
- In the United States, recurrent pregnancy loss is defined as two or more consecutive pregnancy losses documented by ultrasound or histology, in the United Kingdom as three or more consecutive early losses.
- Primary recurrent pregnancy loss affects women without a previous live birth, secondary recurrent pregnancy loss women with at least one earlier live birth.
Occurrence & epidemiology
Epidemiology
- Only about 2% of pregnant women have two consecutive pregnancy losses.
- In up to 50% of affected women no clearly defined cause is found.
Aetiopathogenesis
Aetiology and risk factors
- Genetic: fetal chromosomal abnormalities account for a large share of miscarriages; one parent may carry a balanced translocation.
- Anatomical: uterine or cervical abnormalities such as uterine malformations (for example a septate uterus), polyps, fibroids, intrauterine adhesions or cervical insufficiency may be involved.
- Medical: poorly controlled chronic disorders such as hypo- or hyperthyroidism, diabetes mellitus, hypertension or chronic kidney disease are possible causes.
- Thrombophilic: antiphospholipid syndrome (lupus anticoagulant, anticardiolipin or anti-beta2 glycoprotein I antibodies) is associated with recurrent losses after 10 weeks of gestation; the link with hereditary thrombophilias is less clear.
- The risk of pregnancy loss is lowest between 20 and 35 years of age and rises rapidly after 40.
Clinical features
Clinical features and complications
- Recurrent pregnancy loss is psychologically distressing; anxiety and apprehension are common, especially when the cause remains unclear.
- Stress is associated with recurrent pregnancy loss, but there is no evidence that it is a direct cause.
Diagnosis
History and basic diagnostics
- The basic endocrine work-up includes the measurement of TSH and TPO antibodies.
Further diagnostics
- To investigate uterine anomalies such as a septum or submucosal fibroids, ultrasound, 3D sonography of the cavity and hysteroscopy are suitable.
- The diagnosis is clinical and based on a history of two or more previous miscarriages.
- The search for a cause includes karyotyping of both partners, antiphospholipid antibodies (anticardiolipin, anti-beta2 glycoprotein I antibodies, lupus anticoagulant), TSH and testing for diabetes.
- Genetic analysis of miscarriage tissue can complement the work-up.
Treatment principles
- Treatment depends on the cause identified: in antiphospholipid syndrome, a combination of platelet inhibition and low-molecular-weight heparin is given from early pregnancy, overt thyroid dysfunction is treated, and hysteroscopic resection of a uterine septum is decided individually, as its benefit has not been shown in randomised trials.
- In selected situations, luteal phase support with progestogens may be useful; with an abnormal karyotype, genetic counselling is offered.
- Supportive care is important, including the reassurance that the chance of a live birth remains good even after several miscarriages.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Heterotopic pregnancy · Hyperemesis gravidarum · Interstitial (cornual) pregnancy
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.