Mayer-Rokitansky-Küster-Hauser syndrome
Exam relevance: in 1 of more than 150 board exam reports · rank 171
- Specialty
- Gynaecology · Endocrinology & cycle
- Images
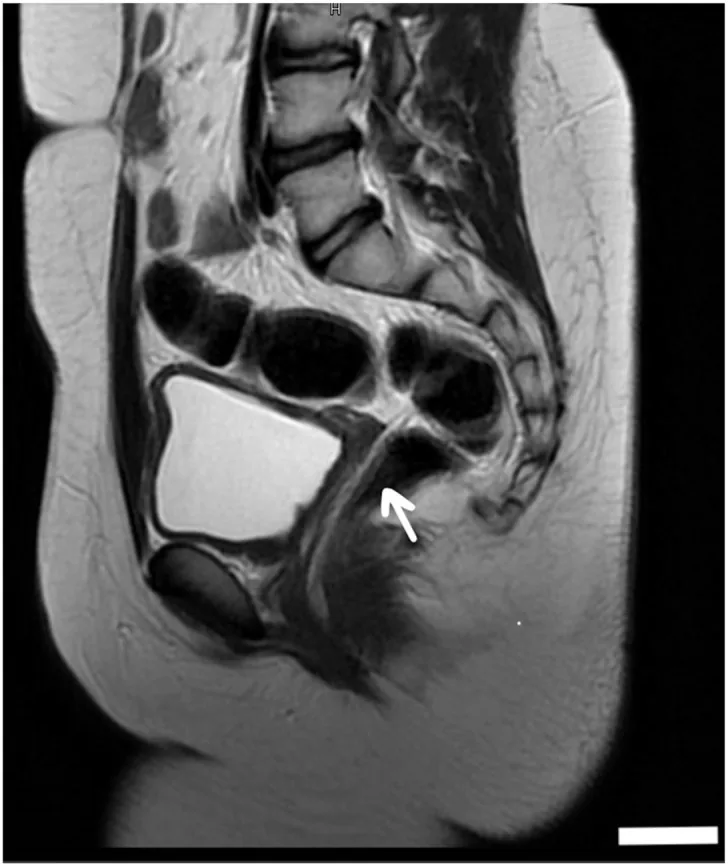
- Mammography/MRI 1
- Exam relevance
- 1 of more than 150 reports · rank 171
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
Definition
- Mayer-Rokitansky-Küster-Hauser syndrome is a congenital absence or underdevelopment of the uterus and upper vagina with a 46,XX karyotype, normal external genitalia and functioning ovaries.
Classification
- Type 1 affects only the reproductive organs; type 2 additionally involves anomalies such as unilateral renal agenesis or abnormal kidney position, vertebral anomalies, hearing loss or heart defects.
- Type 1 accounts for about 56–72% and type 2 for about 28–44% of cases.
Occurrence & epidemiology
Epidemiology
- About 1 in 4,500 to 5,000 female newborns are affected; the syndrome is found in about 16% of patients with primary amenorrhoea and is considered the second most common cause after ovarian insufficiency.
Aetiopathogenesis
Aetiology and pathogenesis
- The underlying defect is incomplete development of the Müllerian ducts, which give rise to the uterus, fallopian tubes, cervix and upper vagina; why this occurs is unknown.
- It usually occurs sporadically; some families show autosomal dominant inheritance, and genetic and environmental factors probably act together.
Clinical features
- The first sign is often primary amenorrhoea with normal breast and pubic hair development.
- A pregnancy cannot be carried.
Diagnosis
- Examination reveals a shortened, blind-ending vagina.
- On ultrasound the uterus is absent while the ovaries are present; MRI of the internal genitalia is considered the gold standard, and the karyotype is 46,XX.
Treatment principles
- Care is provided in a specialist centre and includes psychological support and renal assessment from the outset.
- Non-surgical vaginal dilation is the first-line method for creating a functional neovagina; surgical procedures are considered if this is insufficient.
- Counselling covers the options for having children, including uterus transplantation, which is offered at only a few centres.
Specific treatment regimens with drugs and doses are covered in the GynFuchs app.
Keep learning in the app
Further reading (selection)
Cross-references
More topics: Endocrinology & cycle
Keep learning
Keep learning with flashcards, exam questions and spot diagnoses in the GynFuchs app – free, in your browser or as an app.
Related pages: Ovarian hyperstimulation syndrome (OHSS) · Polycystic ovary syndrome (PCOS) · Postmenopausal osteoporosis
Note: Learning content from the GynFuchs app (flashcards, exam questions, image cases) for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.